Related Experiment Video
Updated: Sep 3, 2025


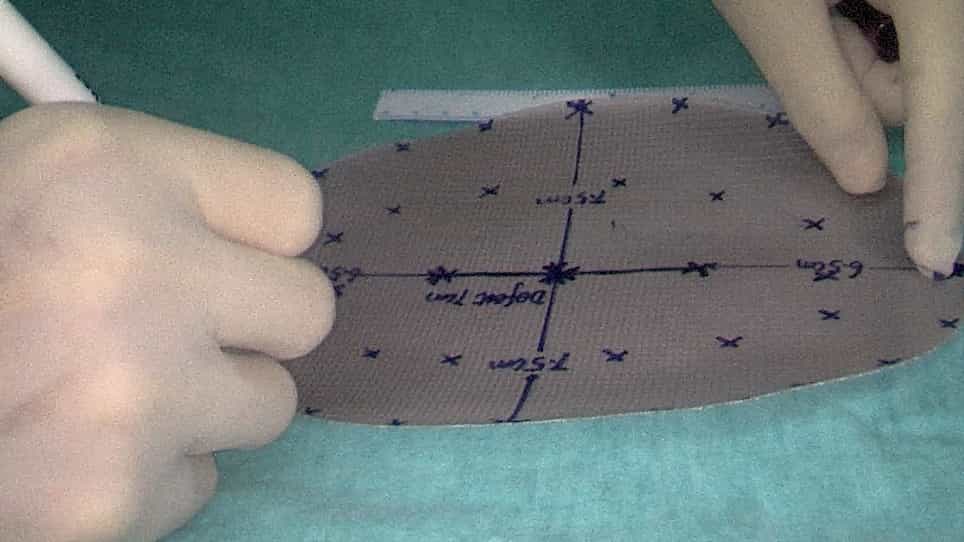
Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Novel "starburst" mesh configuration for paraesophageal and recurrent hiatal hernia repair: comparison with keyhole
Emily Grimsley1, Ana Capati2, Adham R Saad2
1Department of Surgery, University of South Florida Morsani College of Medicine, 12901 Bruce B Downs Blvd, MDC 3129, Tampa, FL, 33612, USA. grimsley@usf.edu.

Background:
Controversy exists over the use of mesh, its type and configuration in repair of hiatal hernia. We have used biological mesh for large or recurrent hiatal hernias. We have developed a mesh configuration to better enhance the tensile strength of the hiatus by folding the mesh over the edge of the hiatus-entitled the "starburst" configuration. We report our experience with the starburst configuration, comparing it to our results with the keyhole configuration.
Methods:
Medical records of all patients undergoing either the keyhole or starburst mesh configuration hiatal hernia repair were reviewed between 2017 and 2021. Data gathered included age, sex, type of hernia (sliding, paraesophageal, or recurrent), fundoplication type (none, Nissen, Toupet, Dor, Collis-Nissen, Collis-Toupet, or magnetic sphincter augmentation [MSA]), 30-day complications, and long-term outcomes (hiatal hernia recurrence, reflux-symptom recurrence, dysphagia, dilations, reoperations).
Results:
From 7/2017 to 8/2019, 51 cases using the keyhole mesh were completed. Sliding hiatal hernia comprised 4%, paraesophageal hernia (PEH) 64% and recurrent hiatal hernia (RHH) 34% of cases. Distribution of fundoplication type: 2% none, 41% Nissen, 41% Toupet, 8% Dor, 2% Collis-Nissen, and 6% Collis-Toupet. 30-day complication rate 31%. Long-term outcomes: recurrent hiatal hernia 16%, dysphagia 12%, dysphagia requiring dilation(s) 10%, recurrent GERD symptoms 4%, and reoperation 14%. From 10/2020 to 8/2021, 58 cases using the starburst configuration were completed. PEH comprised 60% and RHH 40%. Distribution of fundoplication type: 10% none, 40% Nissen, 43% Toupet, 5% MSA, 2% Collis-Toupet. 30-day complication rate 16%. Long-term outcomes: recurrent hiatal hernia 19%, dysphagia 14%, dilations 5%, recurrent GERD symptoms 9%, and reoperations 3%.
Conclusion:
The starburst mesh configuration compares favorably with the keyhole configuration with respect to postoperative dysphagia, need for esophageal dilation, and GERD symptom recurrence, with similar recurrence rates. We are continuing to further refine this technique and study the long-term outcomes.