Seromucinous Cystadenoma Presenting as Endometriosis Complications in a 57-Year-Old Female: A Case Report
Related Experiment Video
Updated: Sep 2, 2025
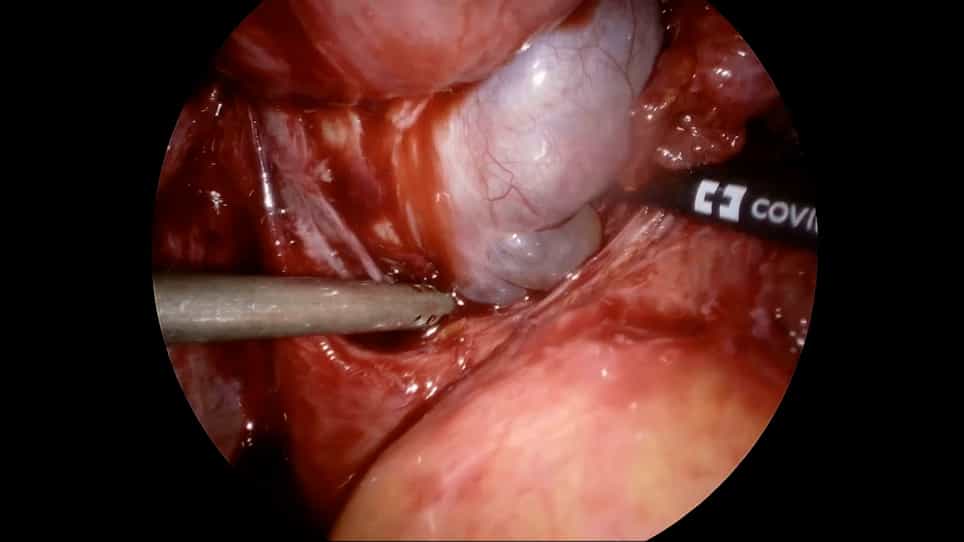
Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
Benjamin Ilyaev1, Maria Levada2, Matthew Sison3
1Medicine, Hofstra University, Hempstead, USA.

Abstract:
Endometriosis should be considered when a female patient reports symptoms of severe pain/tenderness in the pelvic area associated with a frequent need for urination, bloating, vomiting, or nausea. Clinical suspicion is increased if the patient has a history of endometriosis. However, many patients with endometriosis can be asymptomatic, which is why physicians and providers must keep an open mind and have a broad differential. Examinations that aid in the diagnosis of endometriosis include but are not limited to a pelvic examination, an ultrasound, magnetic resonance imaging (MRI), and an exploratory laparoscopy. In this case study, we present a 57-year-old postmenopausal female patient who presented to her obstetrics and gynecology (OBGYN) physician with hot flashes and an abnormal ultrasound revealing an ovarian cyst. Seventeen years prior, at the age of 40, the patient was found to have endometriosis and endometrial polyps and underwent a left oophorectomy. Due to the patient's history, symptoms, and current scans, it was assumed that the present cyst was a complication of endometriosis. Ultimately, the cyst, right ovarian cyst wall, right fallopian tube, and uterine fibroids were surgically removed and sent to pathology. Upon further review of the patient's pathology reports, it was found that the cyst removed was a seromucinous cyst with focal borderline features.