Related Experiment Video
Updated: Sep 2, 2025


Electrocardiogram Recordings in Anesthetized Mice using Lead II
Published on: June 20, 2020
Paradoxical prolongation of QT interval during exercise in patients with hypertrophic cardiomyopathy: cellular
Raffaele Coppini1, Matteo Beltrami2, Ruben Doste3
1Department NeuroFarBa, University of Florence, Viale G. Pieraccini 6, 50139 Florence, Italy.

Insights
Hypertrophic cardiomyopathy (HCM) patients experience exercise intolerance due to abnormal heart cell electrical activity. This study reveals exercise-induced electrical changes worsen diastolic function in non-obstructive HCM.
Area of Science:
- Cardiology
- Electrophysiology
- Heart Failure
Background:
- Hypertrophic cardiomyopathy (HCM) is characterized by ventricular cardiomyocyte dysfunction.
- Patients often report exercise intolerance, particularly those without obstructive disease.
- Abnormalities in action potential duration (APD) and calcium handling are noted in HCM.
Purpose of the Study:
- To investigate exercise-induced repolarization changes in non-obstructive HCM.
- To determine if electrical abnormalities correlate with diastolic dysfunction and exercise intolerance.
- To explore the role of beta-adrenergic stimulation on cardiomyocyte electrical behavior in HCM.
Main Methods:
- Exercise testing with echocardiography in 178 non-obstructive HCM patients and 81 controls.
- Isolation and electrophysiological study of ventricular myocytes from HCM and control hearts.
- Analysis of QT interval changes during exercise and correlation with diastolic function.
Main Results:
- HCM myocytes showed prolonged APDs with beta-adrenergic stimulation, unlike controls.
- HCM patients exhibited less QT interval shortening during peak exercise (QTc: +27 ms vs. -4 ms).
- Significant QTc prolongation (>30 ms) in HCM was linked to limited heart rate increase and worsened diastolic function.
Conclusions:
- Abnormal ion channel balance in HCM cardiomyocytes leads to insufficient APD and calcium transient shortening during exercise.
- Exercise-induced QTc prolongation in HCM is associated with impaired diastolic reserve, contributing to reduced exercise tolerance.
- Severe electrical cardiomyocyte abnormalities likely underlie exercise intolerance in a subset of non-obstructive HCM patients.
Aims:
Ventricular cardiomyocytes from hypertrophic cardiomyopathy (HCM) patient hearts show prolonged action potential duration (APD), impaired intracellular Ca2+ homeostasis and abnormal electrical response to beta -adrenergic stimulation. We sought to determine whether this behaviour is associated with abnormal changes of repolarization during exercise and worsening of diastolic function, ultimately explaining the intolerance to exercise experienced by some patients without obstruction.
Methods And Results:
Non-obstructive HCM patients (178) and control subjects (81) underwent standard exercise testing, including exercise echocardiography. Ventricular myocytes were isolated from myocardial samples of 23 HCM and eight non-failing non-hypertrophic surgical patients. The APD shortening in response to high frequencies was maintained in HCM myocytes, while β-adrenergic stimulation unexpectedly prolonged APDs, ultimately leading to a lesser shortening of APDs in response to exercise. In HCM vs. control subjects, we observed a lesser shortening of QT interval at peak exercise (QTc: +27 ± 52 ms in HCM, -4 ± 50 ms in controls, P < 0.0001). In patients showing a marked QTc prolongation (>30 ms), the excessive shortening of the electrical diastolic period was linked with a limited increase of heart-rate and deterioration of diastolic function at peak effort.
Conclusions:
Abnormal balance of Ca2+- and K+-currents in HCM cardiomyocytes determines insufficient APD and Ca2+-transient shortening with exercise. In HCM patients, exercise-induced QTc prolongation was associated with impaired diastolic reserve, contributing to the reduced exercise tolerance. Our results support the idea that severe electrical cardiomyocyte abnormalities underlie exercise intolerance in a subgroup of HCM patients without obstruction.
More Related Videos
 09:36
Dual-Dye Optical Mapping of Hearts from RyR2R2474S Knock-In Mice of Catecholaminergic Polymorphic Ventricular Tachycardia
Published on: December 22, 2023
 14:39
Isolation and Functional Characterization of Human Ventricular Cardiomyocytes from Fresh Surgical Samples
Published on: April 21, 2014
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Heart Failure II: Pathophysiology
 01:29
Cardiomyopathy V: Interprofessional Care
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:30
Cardiac Action Potential
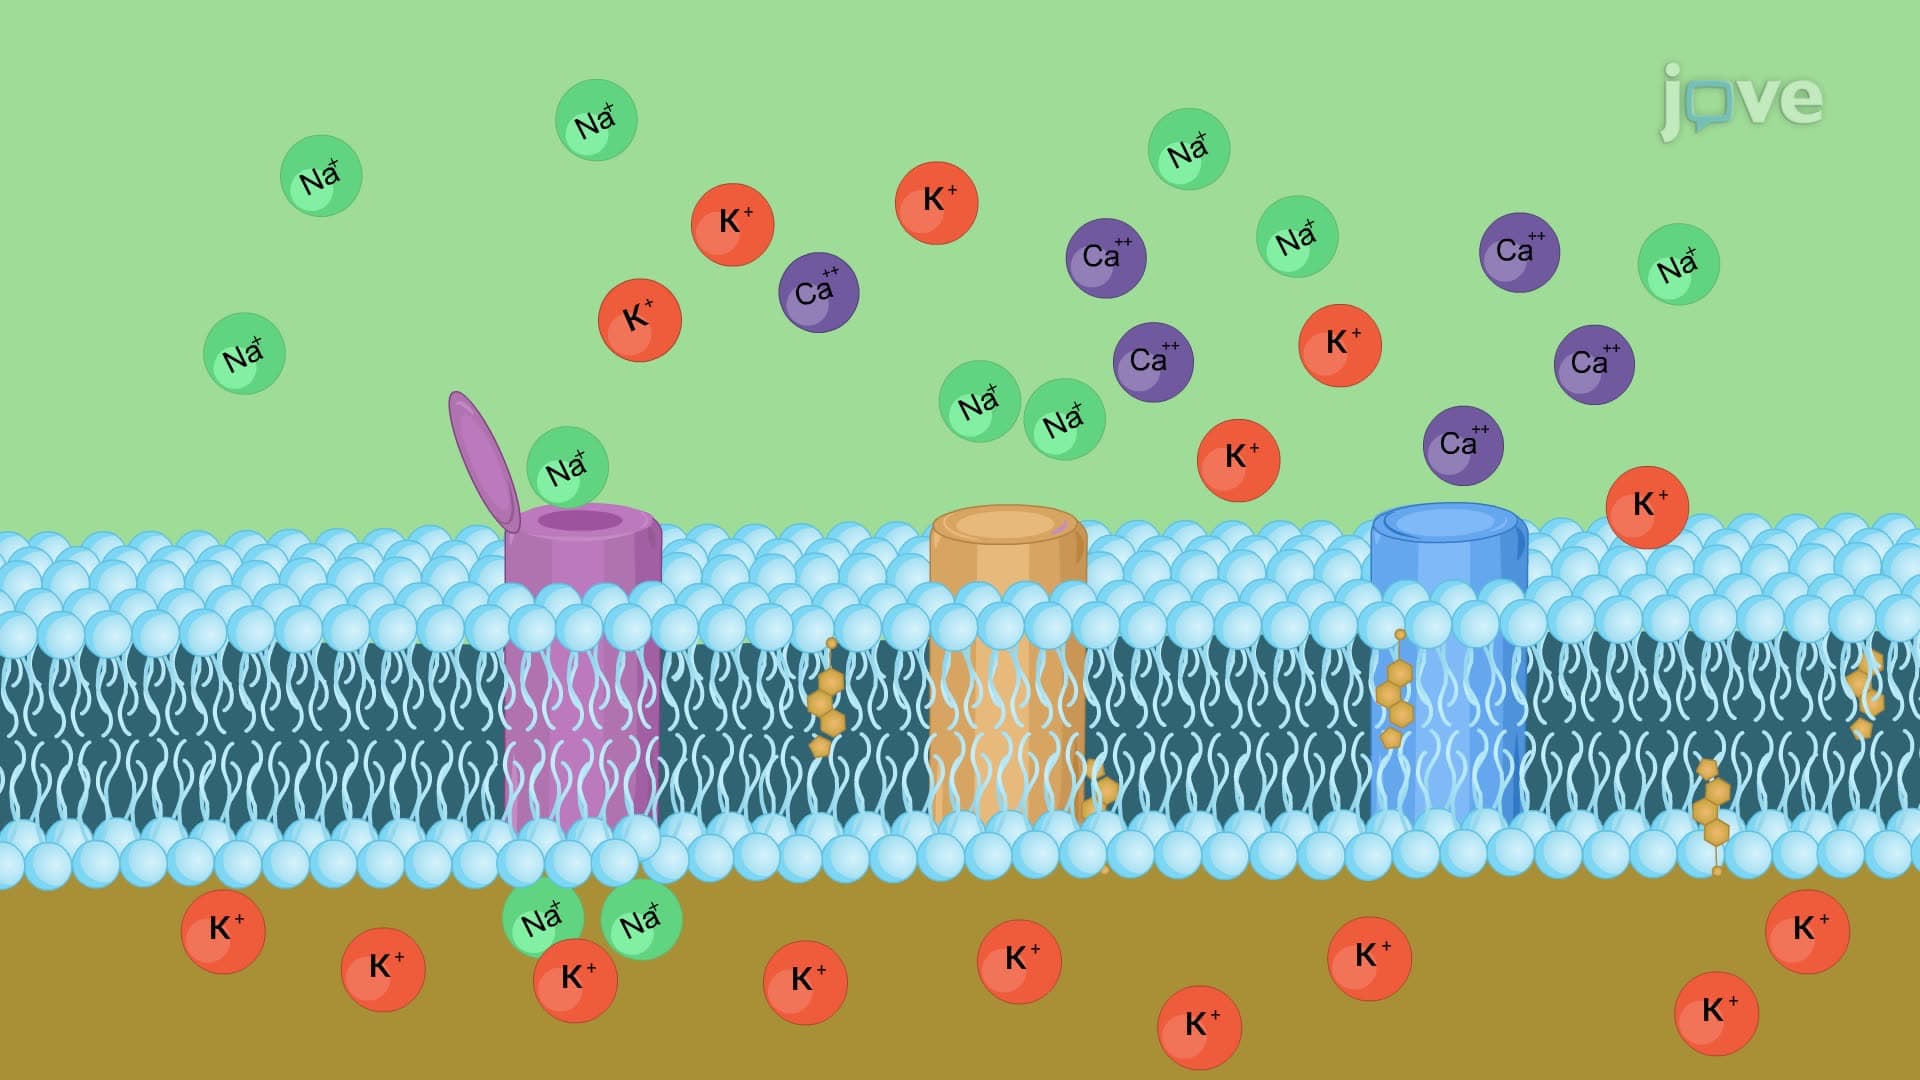
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials