Related Experiment Video
Updated: Sep 2, 2025

Effects of a Novel Neuromuscular Training Intervention on Jump, Sprint, and Change of Direction in Adult Female Soccer Players
Published on: June 10, 2025
Enhanced Bone Size, Microarchitecture, and Strength in Female Runners with a History of Playing Multidirectional
Stuart J Warden, Austin M Sventeckis1, Rachel K Surowiec
1Department of Physical Therapy, School of Health and Human Sciences, Indiana University, Indianapolis, IN.

Purpose:
Female runners have high rates of bone stress injuries (BSIs), including stress reactions and fractures. The current study explored multidirectional sports (MDS) played when younger as a potential means of building stronger bones to reduce BSI risk in these athletes.
Methods:
Female collegiate-level cross-country runners were recruited into groups: 1) RUN, history of training and/or competing in cross-country, recreational running/jogging, swimming, and/or cycling only, and 2) RUN + MDS, additional history of training and/or competing in soccer or basketball. High-resolution peripheral quantitative computed tomography was used to assess the distal tibia, common BSI sites (diaphysis of the tibia, fibula, and second metatarsal), and high-risk BSI sites (base of the second metatarsal, navicular, and proximal diaphysis of the fifth metatarsal). Scans of the radius were used as control sites.
Results:
At the distal tibia, RUN + MDS ( n = 18) had enhanced cortical area (+17.1%) and thickness (+15.8%), and greater trabecular bone volume fraction (+14.6%) and thickness (+8.3%) compared with RUN ( n = 14; all P < 0.005). Failure load was 19.5% higher in RUN + MDS ( P < 0.001). The fibula diaphysis in RUN + MDS had an 11.6% greater total area and a 11.1% greater failure load (all P ≤ 0.03). At the second metatarsal diaphysis, total area in RUN + MDS was 10.4% larger with greater cortical area and thickness and 18.6% greater failure load (all P < 0.05). RUN + MDS had greater trabecular thickness at the base of the second metatarsal and navicular and greater cortical area and thickness at the proximal diaphysis of the fifth metatarsal (all P ≤ 0.02). No differences were observed at the tibial diaphysis or radius.
Conclusions:
These findings support recommendations that athletes delay specialization in running and play MDS when younger to build a more robust skeleton and potentially prevent BSIs.


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:16
Bones of the Lower Limb: Femur and Patella
 01:27
Growth of Cartilage and Bone Tissue
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:27
Compact Bone
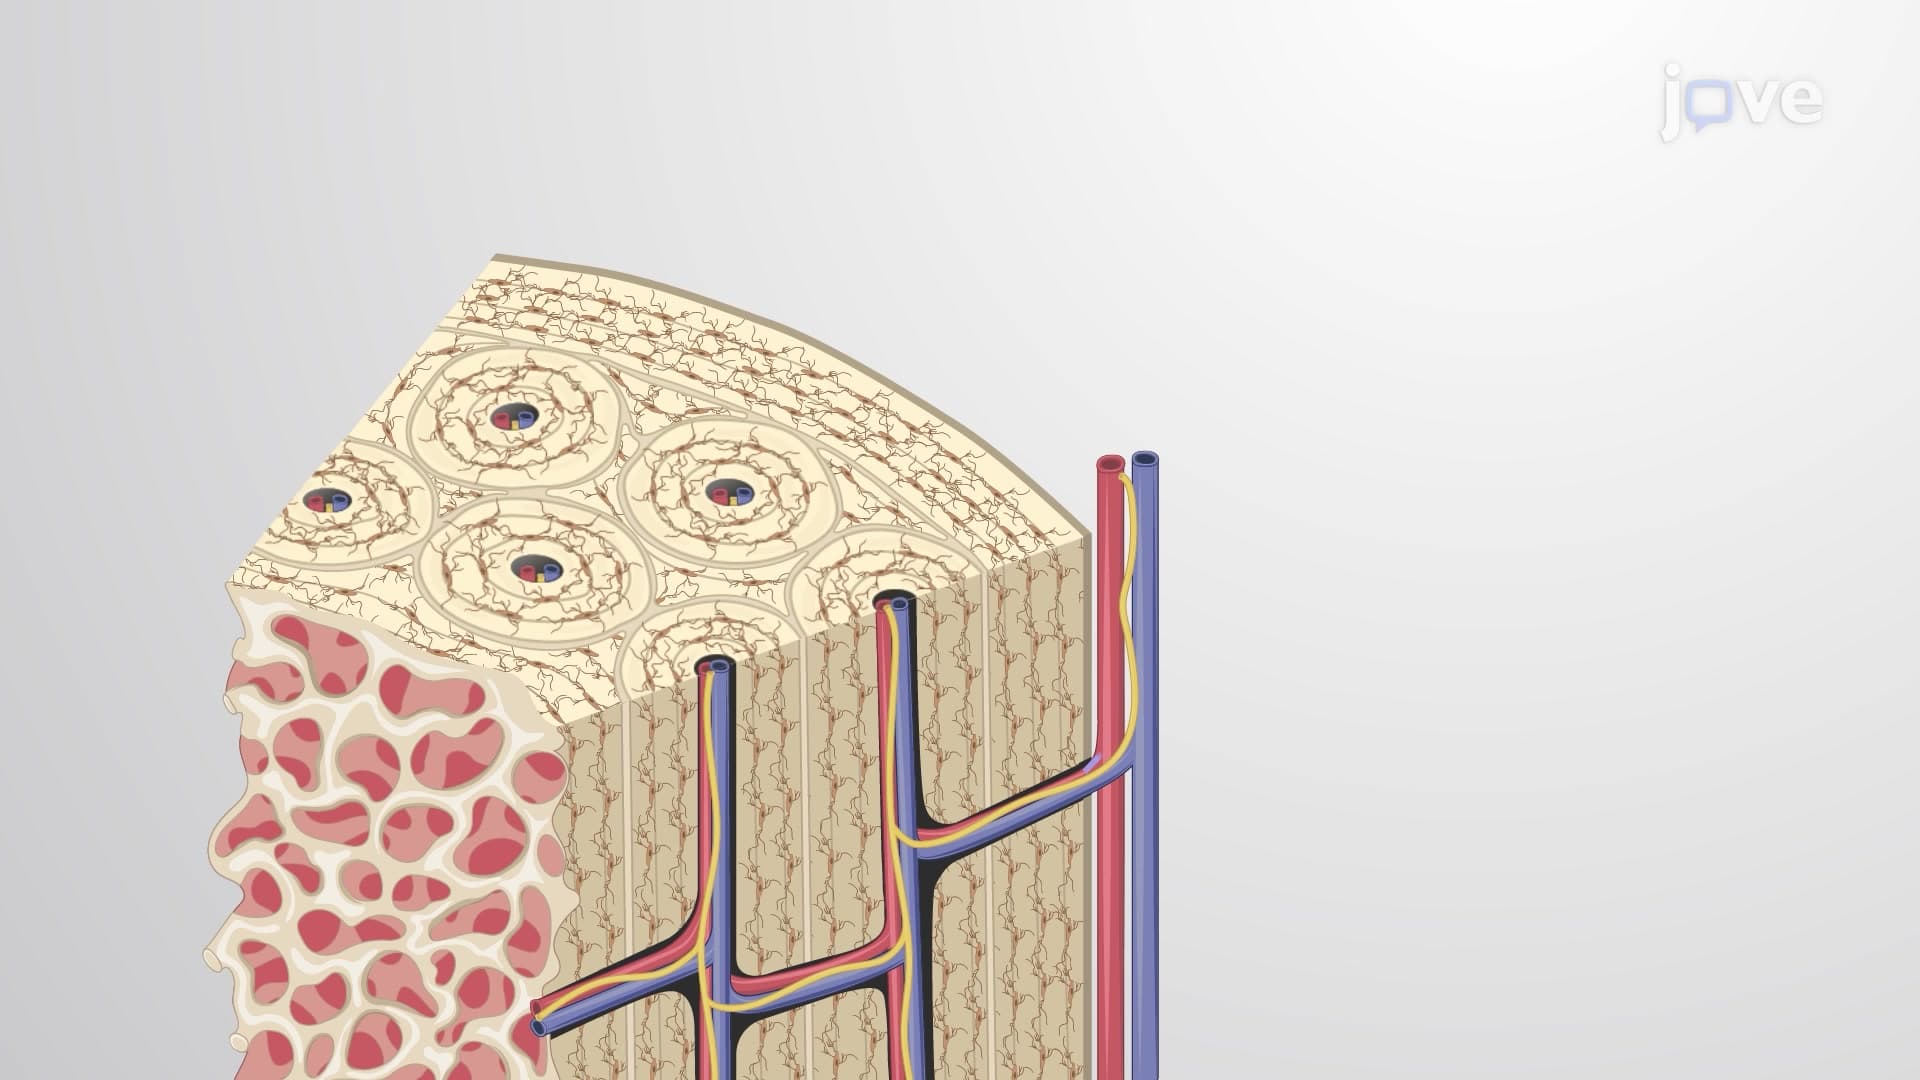
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...