Related Experiment Video
Updated: Jun 15, 2026
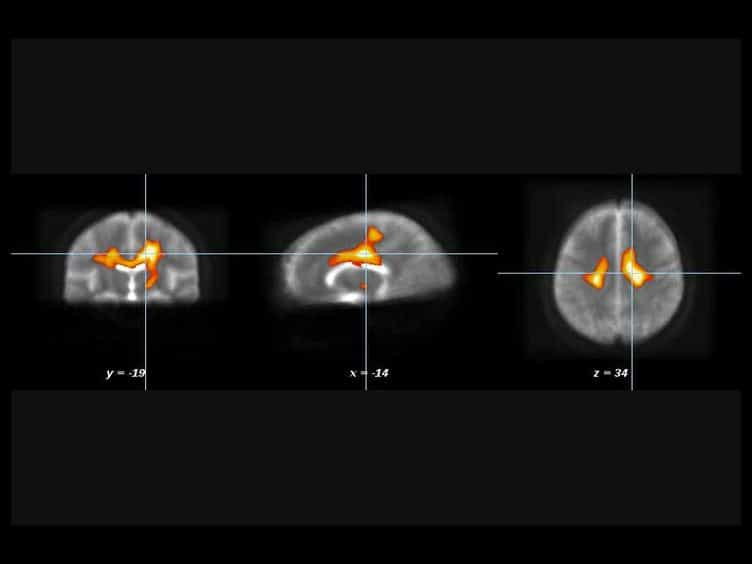

Diffusion Tensor Magnetic Resonance Imaging in the Analysis of Neurodegenerative Diseases
Published on: July 28, 2013
Frequency and Longitudinal Course of Motor Signs in Genetic Frontotemporal Dementia
Sonja Schönecker1, Francisco J Martinez-Murcia1, Boris-Stephan Rauchmann1
1From the Department of Neurology (S. Schönecker, C.P., E.W., S.V.L., A.D., J.L.), Ludwig-Maximilians-Universität München, Germany; Department of Signal Theory Networking and Communications (F.J.M.-M., J.-M.G.S.), Andalusian Research Institute in Data Science and Computational Intelligence (DaSCI), University of Granada, Spain; Institute for Clinical Radiology (B.-S.R.), Institute for Stroke and Dementia Research (N.F.), and Institute of Neuroradiology (K.B.), Ludwig-Maximilians-Universität München, Germany; Département des Sciences Neurologiques (R.L.), Clinique Interdisciplinaire de Mémoire (CIME); McConnell Brain Imaging Centre (S.D.), Montreal Neurological Institute, McGill University; Department of Psychiatry (S.D.), McGill University Health Centre, McGill University, Montreal, Quebec; Tanz Centre for Research in Neurodegenerative Diseases (M.C.T.), University of Toronto; Department of Clinical Neurological Sciences (E.F.), University of Western Ontario, London, Canada; Department of Neurology and Laboratory of Neurosciences (A.M.), Faculty of Medicine, University of Lisbon; Center for Neuroscience and Cell Biology (I.S.), Faculty of Medicine, Centro Hospitalar e Universitário de Coimbra; Center for Neuroscience and Cell Biology (I.S.), Faculty of Medicine, University of Coimbra, Portugal; Alzheimer's Disease and Other Cognitive Disorders Unit (R.S.-V.), Neurology Service, Hospital Clinic, Institut d'Investigacions Biomediques August Pi I Sunyer; Institut d'Investigació Biomèdica August Pi I Sunyer (R.S.-V.), Barcelona; Department of Neurology (F.M.), Donostio University Hospital, San Sebastian; Neuroscience Area (F.M.), Biodonostia Health Research Institute, San Sebastian, Gipuzkoa, Spain; Department of Neuroscience, Psychology, Drug Research and Child Health (S. Sorbi), University of Florence; IRCCS Fondazione Don Carlo Gnocchi (S. Sorbi), Florence; Fondazione Istituto di Ricovero e Cura a Carattere Scientifico Istituto Neurologica Carlo Besta (F.T.), Milano; Centre for Neurodegenerative Disorders (B.B.), Neurology Unit, Department of Clinical and Experimental Sciences, University of Brescia, Italy; Department of Neurology (M.O.), University Hospital Ulm; Department of Neurology (M.O.), Martin-Luther-University Halle-Wittenberg, Germany Department of Neurodegenerative Diseases (M.S.), Hertie-Institute for Clinical Brain Research and Center of Neurology, University of Tübingen; Center for Neurodegenerative Diseases (M.S.), Tübingen, Germany; Fondazione IRCCS Ospediale Policlinico (D.G.), Milan; Centro Dino Ferrari (D.G.), University of Milan, Italy; Leuven Brain Institute (LBI) (R.V.), KU Leuven; Laboratory for Cognitive Neurology (R.V.), Department of Neurosciences, KU Leuven; Neurology Department (R.V.), UZ Leuven, Belgium; Department of Neurology (J.S.), Erasmus Medical Centre, Rotterdam, the Netherlands; Nuffield Department of Clinical Neurosciences (C.B.), Medical Sciences Division, University of Oxford; Department of Brain Sciences (C.B.), Imperial College London; Wolfson Molecular Imaging Centre (A.G.), Faculty of Medicine, Biology and Health, University of Manchester, United Kingdom; Departments of Geriatric Medicine and Nuclear Medicine (A.G.), Essen University Hospital, Germany; Swedish FTD Initiative (C.G.), Stockholm; Division of Neurogeriatrics (C.G.), Centre for Alzheimer Research, Department of Neurobiology, Care Sciences and Society, Karolinska Institutet Solna; Unit for Hereditary Dementias (C.G.), Theme Aging, Karolinska University Hospital, Stockholm, Sweden; Dementia Research Centre (J.D.R.), University College London, United Kingdom; Hurvitz Brain Sciences Program (M.M.), Sunnybrook Research Institute, University of Toronto; Division of Neurology (M.M.), Department of Medicine, University of Toronto; Cognitive and Movement Disorders Clinic (M.M.), Sunnybrook Health Sciences Centre, Toronto, Ontario, Canada; Cognition and Brain Sciences Unit (J.R.), Medical Research Council; Department of Clinical Neurosciences (J.R.), University of Cambridge; Cambridge University Hospitals NHS Trust (J.R.), United Kingdom; German Center for Neurodegenerative Diseases (DZNE) (J.L.); Munich Cluster for Systems Neurology (SyNergy) (J.L.); and European Reference Network for Rare Neurological Diseases (ERN-RND) (J.L.), Munich, Germany.

Background And Objectives:
Frontotemporal dementia (FTD) is a highly heritable disorder. The majority of genetic cases are caused by autosomal dominant pathogenic variants in the chromosome 9 open reading frame 72 (c9orf72), progranulin (GRN), and microtubule-associated protein tau (MAPT) gene. As motor disorders are increasingly recognized as part of the clinical spectrum, the current study aimed to describe motor phenotypes caused by genetic FTD, quantify their temporal association, and investigate their regional association with brain atrophy.
Methods:
We analyzed baseline visit data of known carriers of a pathogenic variant in the c9orf72, GRN, or MAPT gene from the Genetic Frontotemporal Dementia Initiative cohort study. Principal component analysis with varimax rotation was performed to identify motor sign clusters that were compared with respect to frequency and severity between groups. Associations with cross-sectional atrophy patterns were determined using voxel-wise regression. We applied linear mixed effects models to assess whether groups differed in the association between motor signs and estimated time to symptom onset.
Results:
A total of 322 pathogenic variant carriers were included in the analysis: 122 c9orf72 (79 presymptomatic), 143 GRN (112 presymptomatic), and 57 MAPT (43 presymptomatic) pathogenic variant carriers. Principal component analysis revealed 5 motor clusters, which we call progressive supranuclear palsy (PSP)-like, bulbar amyotrophic lateral sclerosis (ALS)-like, mixed/ALS-like, Parkinson disease (PD) like, and corticobasal syndrome-like motor phenotypes. There was no significant group difference in the frequency of signs of different motor phenotypes. However, mixed/ALS-like motor signs were most frequent, followed by PD-like motor signs. Although the PSP-like phenotype was associated with mesencephalic atrophy, the mixed/ALS-like phenotype was associated with motor cortex and corticospinal tract atrophy. The PD-like phenotype was associated with widespread cortical and subcortical atrophy. Estimated time to onset, genetic group and their interaction influenced motor signs. In c9orf72 pathogenic variant carriers, motor signs could be detected up to 25 years before expected symptom onset.
Discussion:
These results indicate the presence of multiple natural clusters of motor signs in genetic FTD, each correlated with specific atrophy patterns. Their motor severity depends on time and the affected gene. These clinicogenetic associations can guide diagnostic evaluations and the design of clinical trials for new disease-modifying and preventive treatments.

Related Concept Videos
 01:29
Alzheimer Disease l: Introduction
 01:23
Alzheimer Disease ll: Pathophysiology
 01:24
Parkinson Disease l: Introduction
 01:24
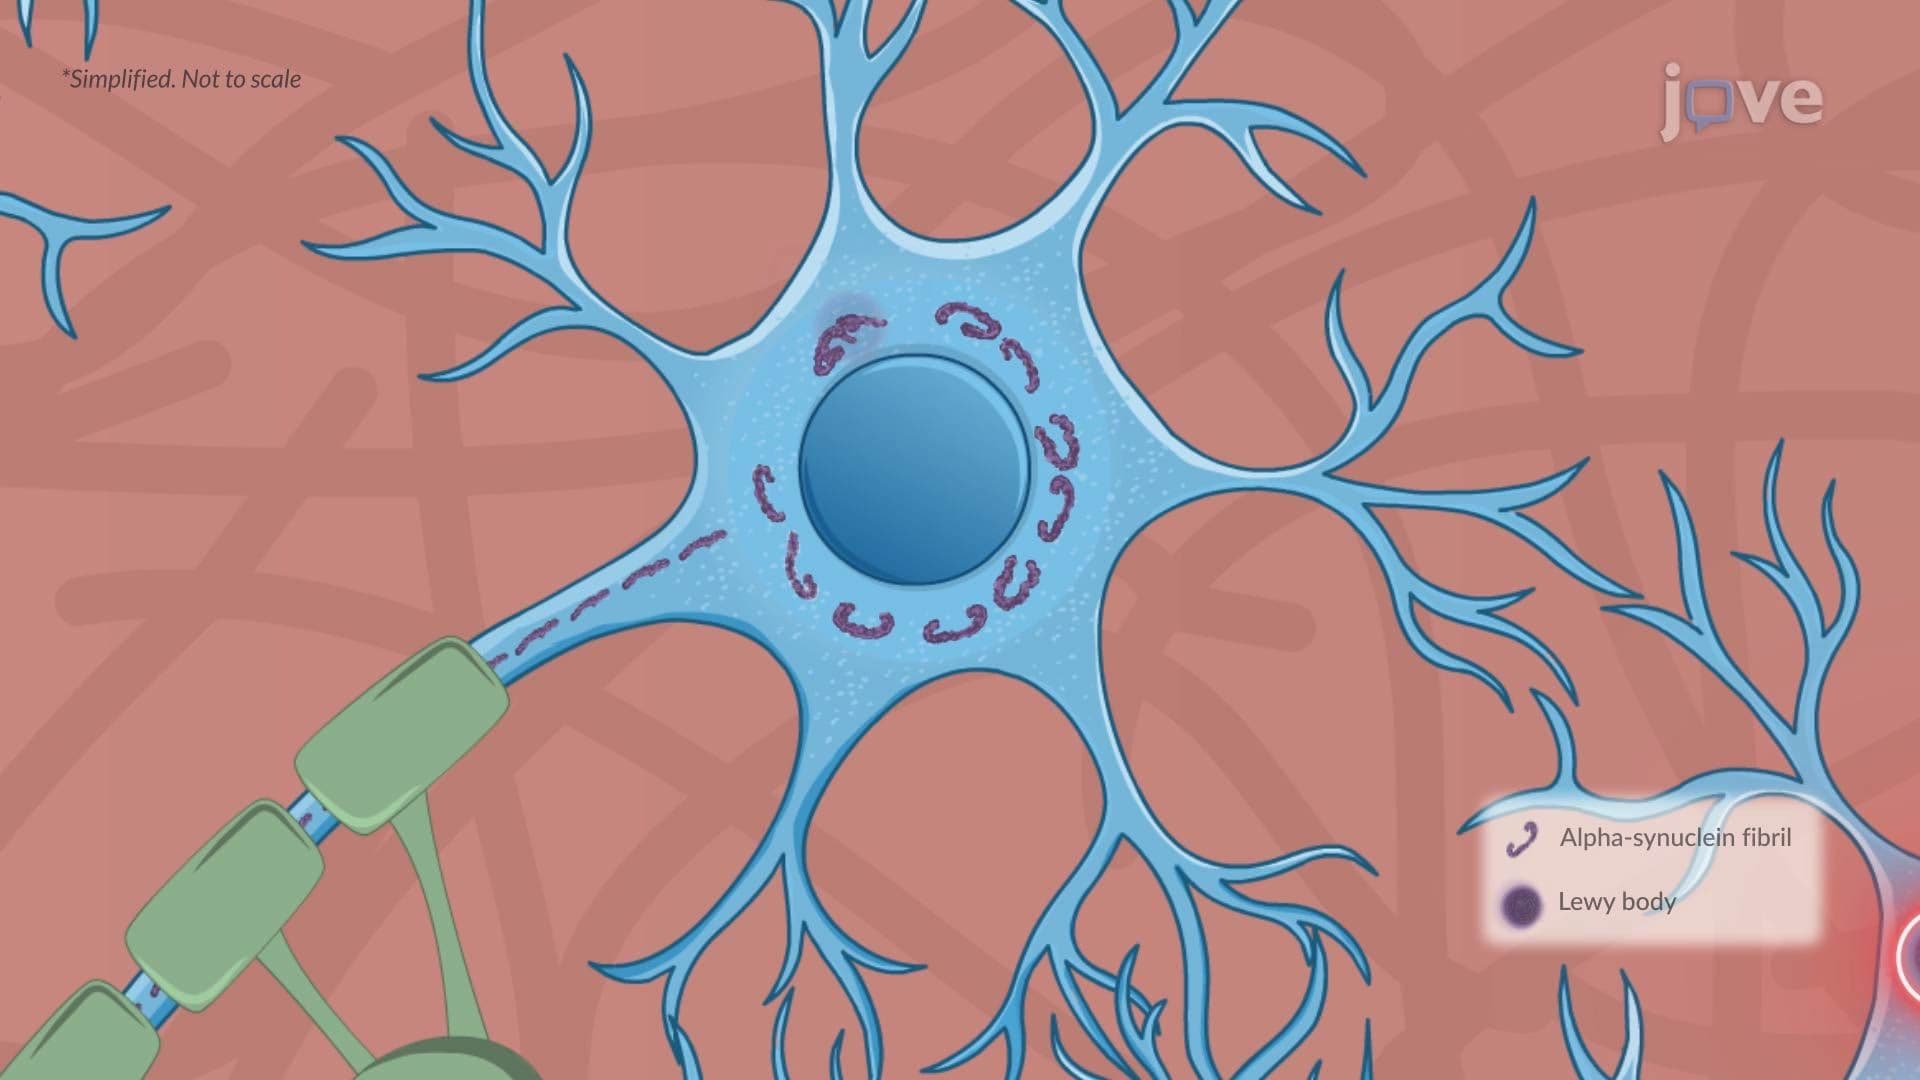
Parkinson Disease ll: Pathophysiology
 01:21
Huntington Disease l: Introduction