Related Experiment Video
Updated: Sep 1, 2025

The Role of Indocyanine Green Fluorescence in Complex Laparoscopic Cholecystectomy Navigation
Published on: January 31, 2025
Value of 3D printing technology combined with indocyanine green fluorescent navigation in complex laparoscopic
Jian Cheng1, Zhifei Wang1, Jie Liu1
1General Surgery, Cancer Center, Department of Hepatobiliary & Pancreatic Surgery and Minimally Invasive Surgery, Zhejiang Provincial People's Hospital (Affiliated People's Hospital, Hangzhou Medical College), Hangzhou, Zhejiang, China.

Background:
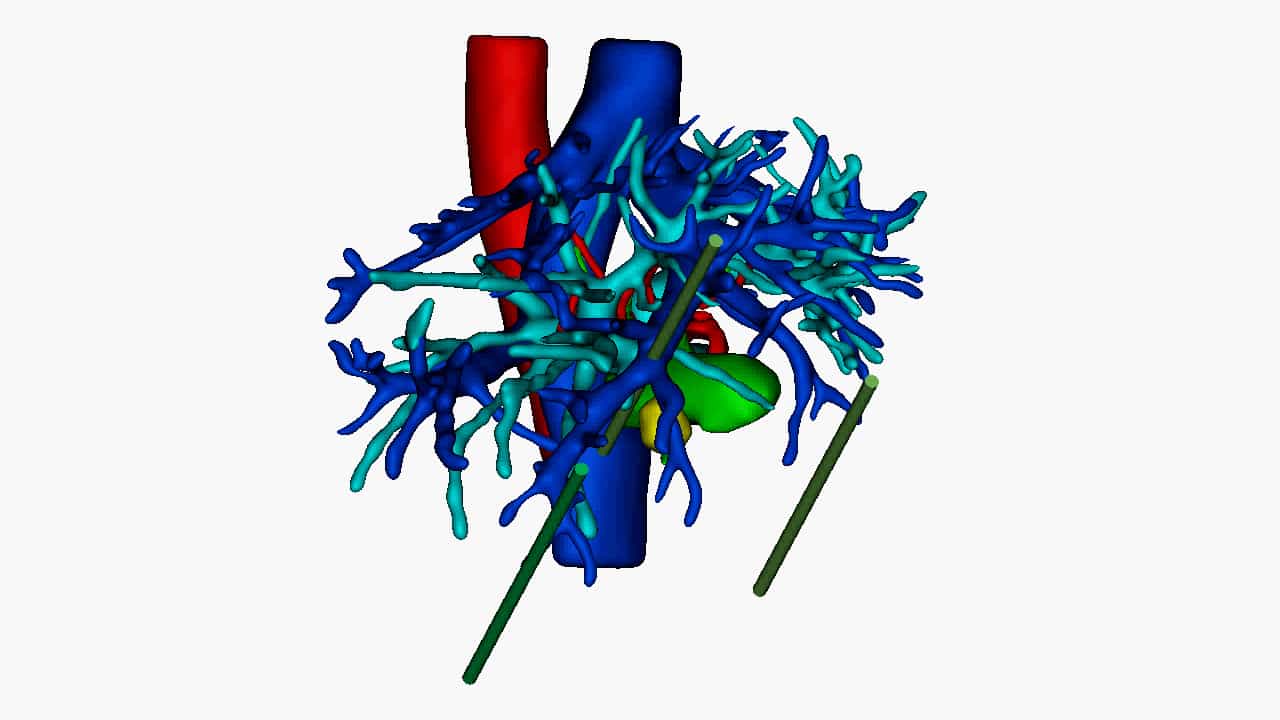
Laparoscopic hepatectomy (LH) has achieved rapid progress over the last decade. However, it is still challenging to apply laparoscopy to lesions located in segments I, VII, VIII, and IVa and the hepatic hilar region due to difficulty operating around complex anatomical structures. In this study, we applied three-dimensional printing (3DP) and indocyanine green (ICG) fluorescence imaging technology to complex laparoscopic hepatectomy (CLH) to explore the effects and value of the modified procedure.
Materials And Methods:
From January 2019 to January 2021, 54 patients with complex hepatobiliary diseases underwent LH at our center. Clinical data were collected from these patients and retrospectively analyzed.
Results:
A total of 30 patients underwent CLH using the conventional approach, whereas 24 cases received CLH with 3DP technology and ICG fluorescent navigation. Preoperative data were compared between the two groups. In the 3DP group, we modified the surgical strategy of four patients (4/24, 16.7%) due to real-time intraoperative navigation with 3DP and ICG fluorescent imaging technology. We did not modify the surgical strategy for any patient in the non-3DP group (P = 0.02). There were no significant differences between the non-3DP and 3DP groups regarding operating time (297.7±104.1 min vs. 328.8±110.9 min, P = 0.15), estimated blood loss (400±263.8 ml vs. 345.8±356.1 ml, P = 0.52), rate of conversion to laparotomy (3/30 vs. 2/24, P = 0.79), or pathological outcomes including the incidence of microscopical R0 margins (28/30 vs. 24/24, P = 0.57). Additionally, there were no significant differences in postoperative complications or recovery conditions between the two groups. No instances of 30- or 90-day mortality were observed.
Conclusion:
The optimal surgical strategy for CLH can be chosen with the help of 3DP technology and ICG fluorescent navigation. This modified procedure is both safe and effective, but without improvement of intraoperative and short-term outcomes.