Related Experiment Video
Updated: Sep 1, 2025


Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
Ventilatory efficiency is superior to peak oxygen uptake for prediction of lung resection cardiovascular
Andrej Mazur1,2,3, Kristian Brat2,3,4, Pavel Homolka2,3,5
1Department of Anesthesiology and Intensive Care, St. Anne's University Hospital Brno, Brno, Czech Republic.

Introduction:
Ventilatory efficiency (VE/VCO2 slope) has been shown superior to peak oxygen consumption (VO2) for prediction of post-operative pulmonary complications in patients undergoing thoracotomy. VE/VCO2 slope is determined by ventilatory drive and ventilation/perfusion mismatch whereas VO2 is related to cardiac output and arteriovenous oxygen difference. We hypothesized pre-operative VO2 predicts post-operative cardiovascular complications in patients undergoing lung resection.
Methods:
Lung resection candidates from a published study were evaluated by post-hoc analysis. All of the patients underwent preoperative cardiopulmonary exercise testing. Post-operative cardiovascular complications were assessed during the first 30 post-operative days or hospital stay. One-way analysis of variance or the Kruskal-Wallis test, and multivariate logistic regression were used for statistical analysis and data summarized as median (IQR).
Results:
Of 353 subjects, 30 (9%) developed pulmonary complications only (excluded from further analysis), while 78 subjects (22%) developed cardiovascular complications and were divided into two groups for analysis: cardiovascular only (n = 49) and cardiovascular with pulmonary complications (n = 29). Compared to patients without complications (n = 245), peak VO2 was significantly lower in the cardiovascular with pulmonary complications group [19.9 ml/kg/min (16.5-25) vs. 16.3 ml/kg/min (15-20.3); P<0.01] but not in the cardiovascular only complications group [19.9 ml/kg/min (16.5-25) vs 19.0 ml/kg/min (16-23.1); P = 0.18]. In contrast, VE/VCO2 slope was significantly higher in both cardiovascular only [29 (25-33) vs. 31 (27-37); P = 0.05] and cardiovascular with pulmonary complication groups [29 (25-33) vs. 37 (34-42); P<0.01)]. Logistic regression analysis showed VE/VCO2 slope [OR = 1.06; 95%CI (1.01-1.11); P = 0.01; AUC = 0.74], but not peak VO2 to be independently associated with post-operative cardiovascular complications.
Conclusion:
VE/VCO2 slope is superior to peak VO2 for prediction of post-operative cardiovascular complications in lung resection candidates.
More Related Videos
 05:56
Author Spotlight: Enhancing Diagnostic Strategies and Biomarker Development for Comprehensive Lung Function Analysis
Published on: August 9, 2024
 09:31
Normothermic Negative Pressure Ventilation Ex Situ Lung Perfusion: Evaluation of Lung Function and Metabolism
Published on: February 14, 2022
Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:15
Respiratory Volumes
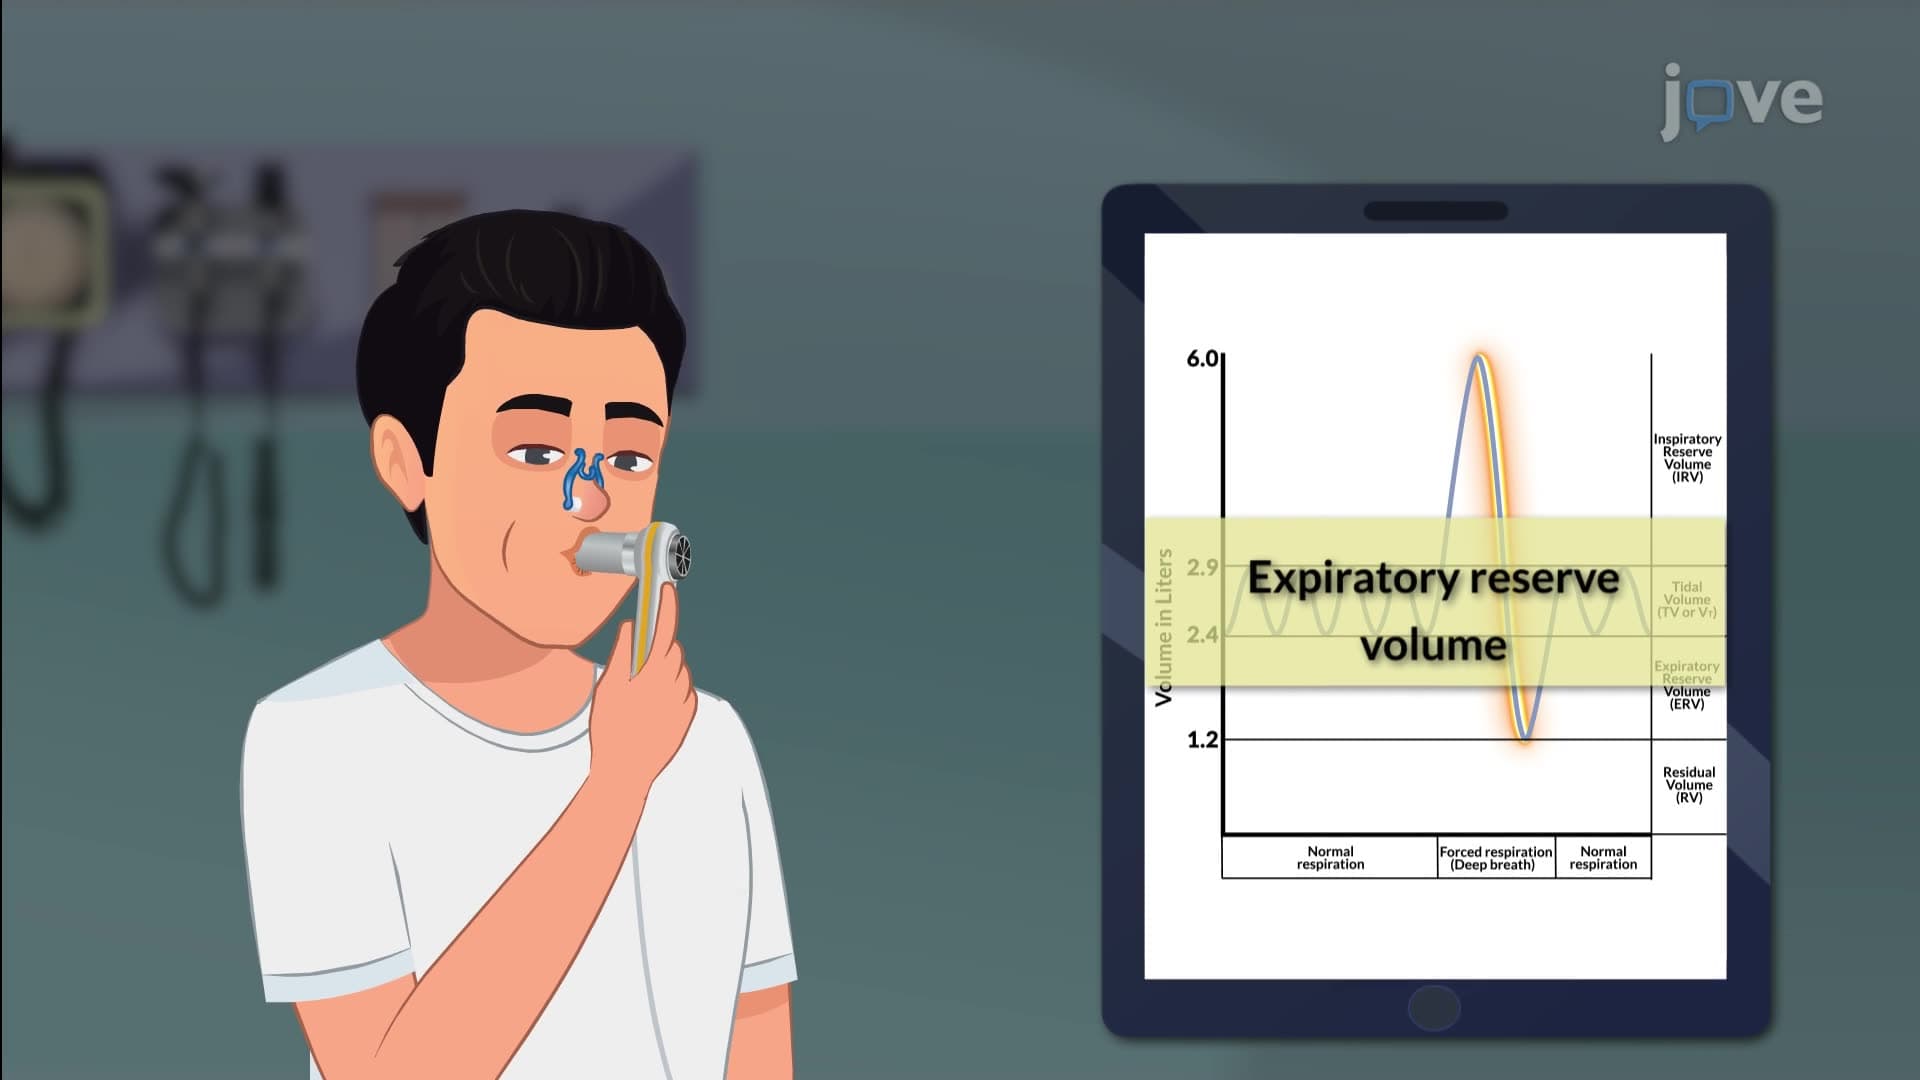
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:22
Respiratory Volumes and Capacities
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:26
Respiratory Volumes and Capacities I