Related Experiment Video
Updated: Aug 8, 2026


Lateral Chronic Cranial Window Preparation Enables In Vivo Observation Following Distal Middle Cerebral Artery Occlusion in Mice
Published on: December 29, 2016
Long-term outcome of cerebral amyloid angiopathy-related hemorrhage
Ruiwen Che1,2, Mengke Zhang1, Hailiang Sun3
1Department of Neurology, Xuanwu Hospital, Capital Medical University, Beijing, China.

Insights
Nearly half of cerebral amyloid angiopathy-related hemorrhage (CAAH) patients achieve good long-term outcomes. Glasgow Coma Scale score, recurrent intracerebral hemorrhage, white matter lesion grade, and cerebral atrophy predict outcomes.
Area of Science:
- Neurology
- Neurosurgery
- Geriatric Medicine
Background:
- Cerebral amyloid angiopathy-related hemorrhage (CAAH) is a significant cause of spontaneous intracerebral hemorrhage, particularly in the elderly.
- Long-term functional outcomes and prognostic factors for CAAH patients remain incompletely understood.
- Understanding these factors is crucial for patient management and prognosis prediction.
Purpose of the Study:
- To assess the long-term functional outcomes of patients with cerebral amyloid angiopathy-related hemorrhage (CAAH).
- To identify independent prognostic factors associated with unfavorable long-term outcomes in CAAH patients.
Main Methods:
- An observational study including consecutive CAAH patients from 2014 to 2020.
- Collection of baseline characteristics and clinical outcomes.
- Multivariable logistic regression analysis to identify prognostic factors for long-term outcomes.
Main Results:
- Out of 141 CAAH patients, 50.4% achieved favorable long-term outcomes, with a 23.4% mortality rate at a median follow-up of 19 months.
- Independent predictors for unfavorable long-term outcomes included lower Glasgow Coma Scale (GCS) on admission, recurrence of intracerebral hemorrhage (ICH), high white matter lesion (WML) grade (3-4), and severe central cerebral atrophy.
- Statistical significance was observed for GCS (p=0.008), ICH recurrence (p=0.011), WML grade (p=0.047), and cerebral atrophy (p=0.008).
Conclusions:
- Approximately 50% of CAAH patients experience favorable long-term functional outcomes.
- Glasgow Coma Scale score, intracerebral hemorrhage recurrence, white matter lesion grade, and cerebral atrophy are significant independent prognostic factors for long-term outcomes in CAAH patients.
- These identified factors can aid in predicting prognosis and guiding clinical management strategies for CAAH.
Object:
The long-term functional outcome of cerebral amyloid angiopathy-related hemorrhage (CAAH) patients is unclear. We sought to assess the long-term functional outcome of CAAH and determine the prognostic factors associated with unfavorable outcomes.
Methods:
We enrolled consecutive CAAH patients from 2014 to 2020 in this observational study. Baseline characteristics and clinical outcomes were presented. Multivariable logistic regression analysis was performed to identify the prognostic factors associated with long-term outcome.
Results:
Among the 141 CAAH patients, 76 (53.9%) achieved favorable outcomes and 28 (19.9%) of them died at 1-year follow-up. For the longer-term follow-up with a median observation time of 19.0 (interquartile range, 12.0-26.5) months, 71 (50.4%) patients obtained favorable outcomes while 33 (23.4%) died. GCS on admission (OR, 0.109; 95% CI, 0.021-0.556; p = 0.008), recurrence of ICH (OR, 2923.687; 95% CI, 6.282-1360730.14; p = 0.011), WML grade 3-4 (OR, 31.007; 95% CI, 1.041-923.573; p = 0.047), severe central atrophy (OR, 4220.303; 95% CI, 9.135-1949674.84; p = 0.008) assessed by CT was identified as independent predictors for long-term outcome.
Interpretation:
Nearly 50% of CAAH patients achieved favorable outcomes at long-term follow-up. GCS, recurrence of ICH, WML grade and cerebral atrophy were identified as independent prognostic factors of long-term outcome.
More Related Videos


Related Concept Videos
 01:15
Ischemic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology
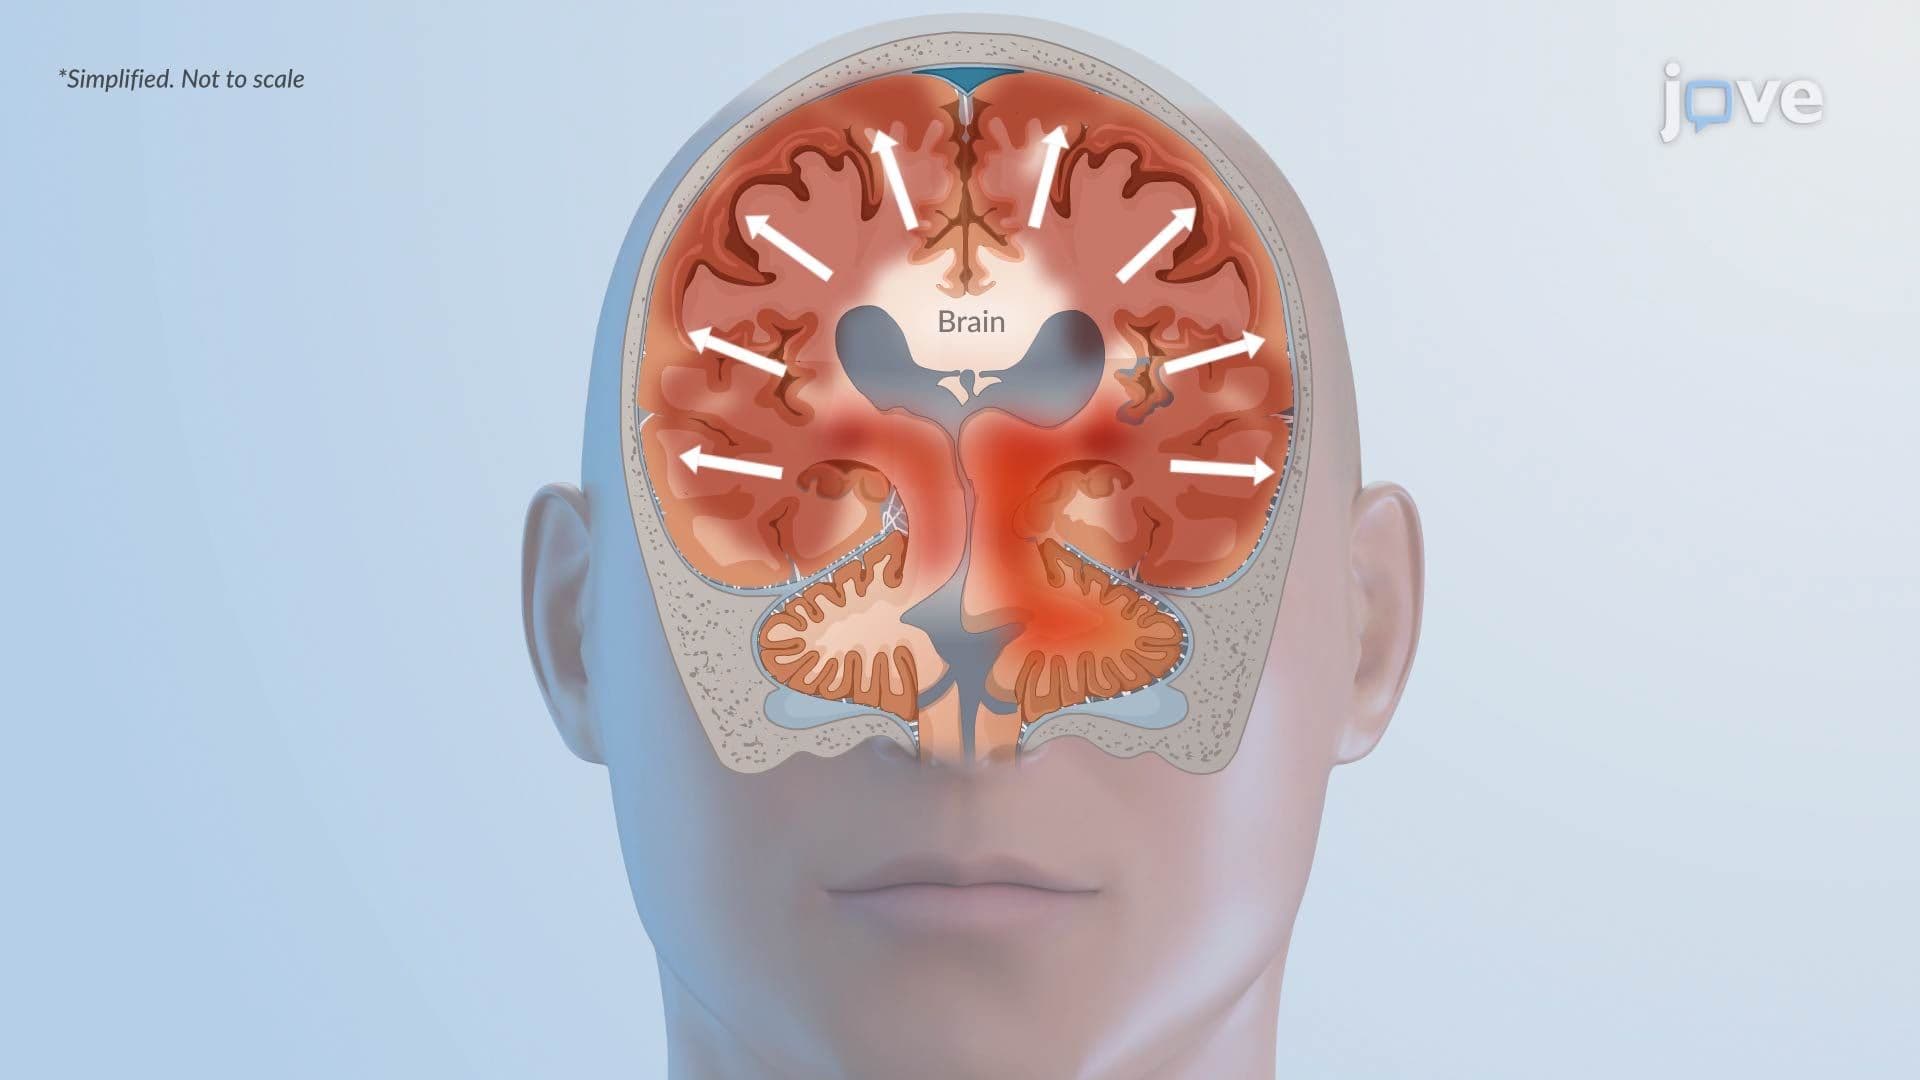 01:21
Cytotoxic Edema: Pathophysiology
 01:29
Hepatic Encephalopathy