Related Experiment Video
Updated: Sep 1, 2025
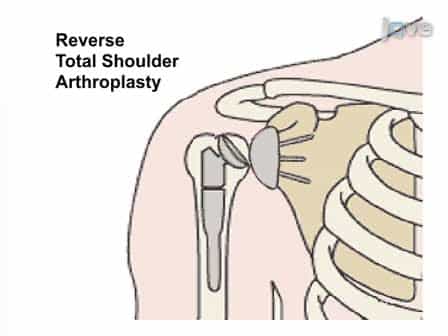

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Medicaid payer status is associated with increased 90-day morbidity and resource utilization following primary
Alexander M Dawes1, Kevin X Farley1, William S Godfrey1
1Emory Orthopaedics and Spine Center, Atlanta, GA, USA.

Background:
Medicaid payer status has been shown to affect risk-adjusted patient outcomes and health care utilization across multiple medical specialties and orthopedic procedures. However, there is a paucity of data regarding the impact of Medicaid payer status on 90-day morbidity and resource utilization following primary shoulder arthroplasty (reverse total shoulder arthroplasty [rTSA], anatomic total shoulder arthroplasty [aTSA], and hemiarthroplasty [HA]). The purpose of this study was to examine 90-day readmission and reoperation rates, hospital length of stay (LOS), and direct cost following primary shoulder arthroplasty in the Medicaid population.
Methods:
The National Readmission Database was queried for all patients undergoing primary aTSA, rTSA, and HA from 2011 to 2016. Medicaid or non-Medicaid payer status was determined. Patient demographic characteristics and comorbidities, along with 90-day readmission, 90-day reoperation, LOS, and inflation-adjusted cost, were queried. Propensity score matching was used to control for baseline differences in cohorts that could be acting as confounders in the exposure-outcome relationship. This was achieved with 1-to-1 propensity score matching between Medicaid and non-Medicaid patients. Odds ratios (ORs) and 95% confidence intervals (CIs) for 90-day readmission and reoperation rates were calculated, and a comparison of LOS and cost was performed between the propensity score-matched cohorts.
Results:
A total of 4667 Medicaid and 161,147 non-Medicaid patients were identified from the 2011-2016 National Readmission Databases. Propensity score analysis was performed, and 4637 Medicaid patients were matched to 4637 non-Medicaid patients; each group comprised 1504 rTSAs (32.4%), 1934 aTSAs (41.7%), and 1199 HAs (25.9%). Patients with Medicaid payer status yielded significant increases in the 90-day all-cause readmission rate of 11.6% vs. 9.3% (P < .001; OR, 1.28 [95% CI, 1.12-1.46]), 90-day shoulder-related readmission rate of 3.3% vs. 2.3% (P = .004; OR, 1.44 [95% CI, 1.12-1.85]), and 90-day reoperation rate of 2.0% vs. 1.3% (P = .008; OR, 1.54 [95% CI, 1.12-1.94]). Furthermore, there was an increased risk of an extended LOS (ie, LOS > 2 days) (28.4% vs. 25.7%; P = .004; OR, 1.14 [95% CI, 1.04-1.25]) along with increased direct cost (median, $17,612 vs. $16,775; P < .001).
Discussion:
This study demonstrates that Medicaid payer status is independently associated with increased 90-day readmission and reoperation rates, LOS, and direct cost following primary shoulder arthroplasty. Providers may have a disincentive to treat patient populations who require increased resource utilization following surgery. Risk adjustment models accounting for Medicaid payer status will be necessary to ensure good access to care for this patient population by avoiding penalties for physicians and hospital systems.
Insights
Medicaid patients undergoing shoulder arthroplasty experienced higher 90-day readmission and reoperation rates, longer hospital stays, and increased costs compared to non-Medicaid patients. This highlights disparities in care and resource utilization.
Area of Science:
- Orthopedic Surgery
- Health Services Research
- Health Economics
Background:
- Medicaid payer status impacts patient outcomes and healthcare utilization across various specialties.
- Limited data exists on Medicaid's effect on 90-day morbidity and resource use after primary shoulder arthroplasty (total shoulder arthroplasty, reverse total shoulder arthroplasty, hemiarthroplasty).
Purpose of the Study:
- To investigate the association between Medicaid payer status and 90-day readmission, reoperation rates, hospital length of stay (LOS), and direct costs following primary shoulder arthroplasty.
Main Methods:
- Utilized the National Readmission Database (2011-2016) for primary shoulder arthroplasty cases.
- Employed 1-to-1 propensity score matching to compare Medicaid and non-Medicaid patient cohorts.
- Analyzed demographic characteristics, comorbidities, 90-day readmissions, 90-day reoperations, LOS, and inflation-adjusted costs.
Main Results:
- Medicaid patients showed significantly higher 90-day all-cause readmission (11.6% vs. 9.3%), shoulder-related readmission (3.3% vs. 2.3%), and reoperation rates (2.0% vs. 1.3%).
- Increased risk of extended LOS (>2 days) was observed in Medicaid patients (28.4% vs. 25.7%).
- Medicaid payer status was associated with higher direct costs (median $17,612 vs. $16,775).
Conclusions:
- Medicaid payer status is independently linked to increased 90-day readmissions, reoperations, LOS, and direct costs after primary shoulder arthroplasty.
- Findings suggest potential disincentives for providers treating Medicaid patients due to higher resource utilization.
- Risk adjustment models incorporating Medicaid status are crucial for equitable care access and to prevent penalties for healthcare systems.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 04:01
The Modified Single-working Portal Technique Using Lasso-loop Stitch with Needle for Arthroscopic Subscapularis Repair
Published on: August 8, 2025
