Related Experiment Video
Updated: Sep 12, 2026

Echocardiographic Evaluation of Atrial Communications before Transcatheter Closure
Published on: February 8, 2022
Arrhythmias before and after anatomic correction of transposition of the great arteries

Insights
Cardiac rhythm evaluation in survivors of transposition of the great arteries shows a low incidence of arrhythmias post-surgery. Long-term follow-up indicates promising results for these patients with corrected heart anatomy.
Area of Science:
- Cardiology
- Pediatric Cardiology
- Cardiac Surgery
Background:
- Transposition of the great arteries (TGA) is a complex congenital heart defect.
- Anatomic correction aims to restore normal blood flow but can impact cardiac rhythm.
- Long-term arrhythmia risk in TGA survivors requires ongoing investigation.
Purpose of the Study:
- To assess cardiac rhythm in survivors of TGA after anatomic correction.
- To evaluate the incidence and types of arrhythmias before and after surgical correction.
- To determine the medium-term safety and efficacy of surgical correction regarding cardiac rhythm.
Main Methods:
- Utilized 24-hour ambulatory electrocardiographic (ECG) recordings.
- Evaluated 92 survivors of TGA, including preoperative and postoperative assessments.
- Monitored patients for a mean follow-up period of 3.1 years.
Main Results:
- Preoperative arrhythmias were uncommon and similar to normal children.
- Postoperative recordings showed a low incidence of significant arrhythmias.
- An increase in supraventricular premature beats was observed post-surgery (4.9% to 23%, p<0.05).
- No arrhythmic deaths or symptomatic arrhythmias requiring treatment occurred during follow-up.
Conclusions:
- Anatomic correction of TGA is associated with a low incidence of important arrhythmias in the medium term.
- Supraventricular ectopy may increase post-correction, necessitating continued monitoring.
- Further longitudinal studies are needed to confirm long-term rhythm stability.
Abstract:
Cardiac rhythm has been evaluated using 24 hour ambulatory electrocardiographic (ECG) recordings in 92 survivors of anatomic correction of transposition of the great arteries. A low incidence of arrhythmias was found in preoperative recordings made in 41 patients. Thirty-four (83%) patients showed sinus rhythm exclusively; one (2.4%) patient had supraventricular premature beats and one (2.4%) paroxysmal atrial fibrillation. Six patients (14.6%) had ventricular arrhythmias, five (12.2%) with modified Lown grade 1 ventricular premature beats and one (2.4%) with a modified Lown grade 5 arrhythmia. The incidence of arrhythmias was unchanged after a first stage operation consisting of banding of the pulmonary artery with or without insertion of a systemic to pulmonary shunt. During a mean 3.1 year follow-up, there have been no cases of arrhythmic death or symptomatic arrhythmias requiring treatment. Postoperative recordings in 40 patients have shown a low incidence of important arrhythmias with 62% having recordings free from arrhythmias. There was an increase in the incidence of infrequent supraventricular premature beats from 4.9% preoperatively to 23% postoperatively (p less than 0.05), with no significant change in the incidence of ventricular arrhythmias. One patient has acquired complete heart block but all others had sinus rhythm postoperatively. Preoperative arrhythmias are uncommon in patients with transposition of the great arteries and are similar to those described in normal children. The incidence of important arrhythmias after anatomic correction is low during the medium-term period of follow-up. Further longitudinal studies will be required to determine whether this promising result is maintained.
More Related Videos


Related Concept Videos
 01:28
Mechanism of Cardiac Arrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
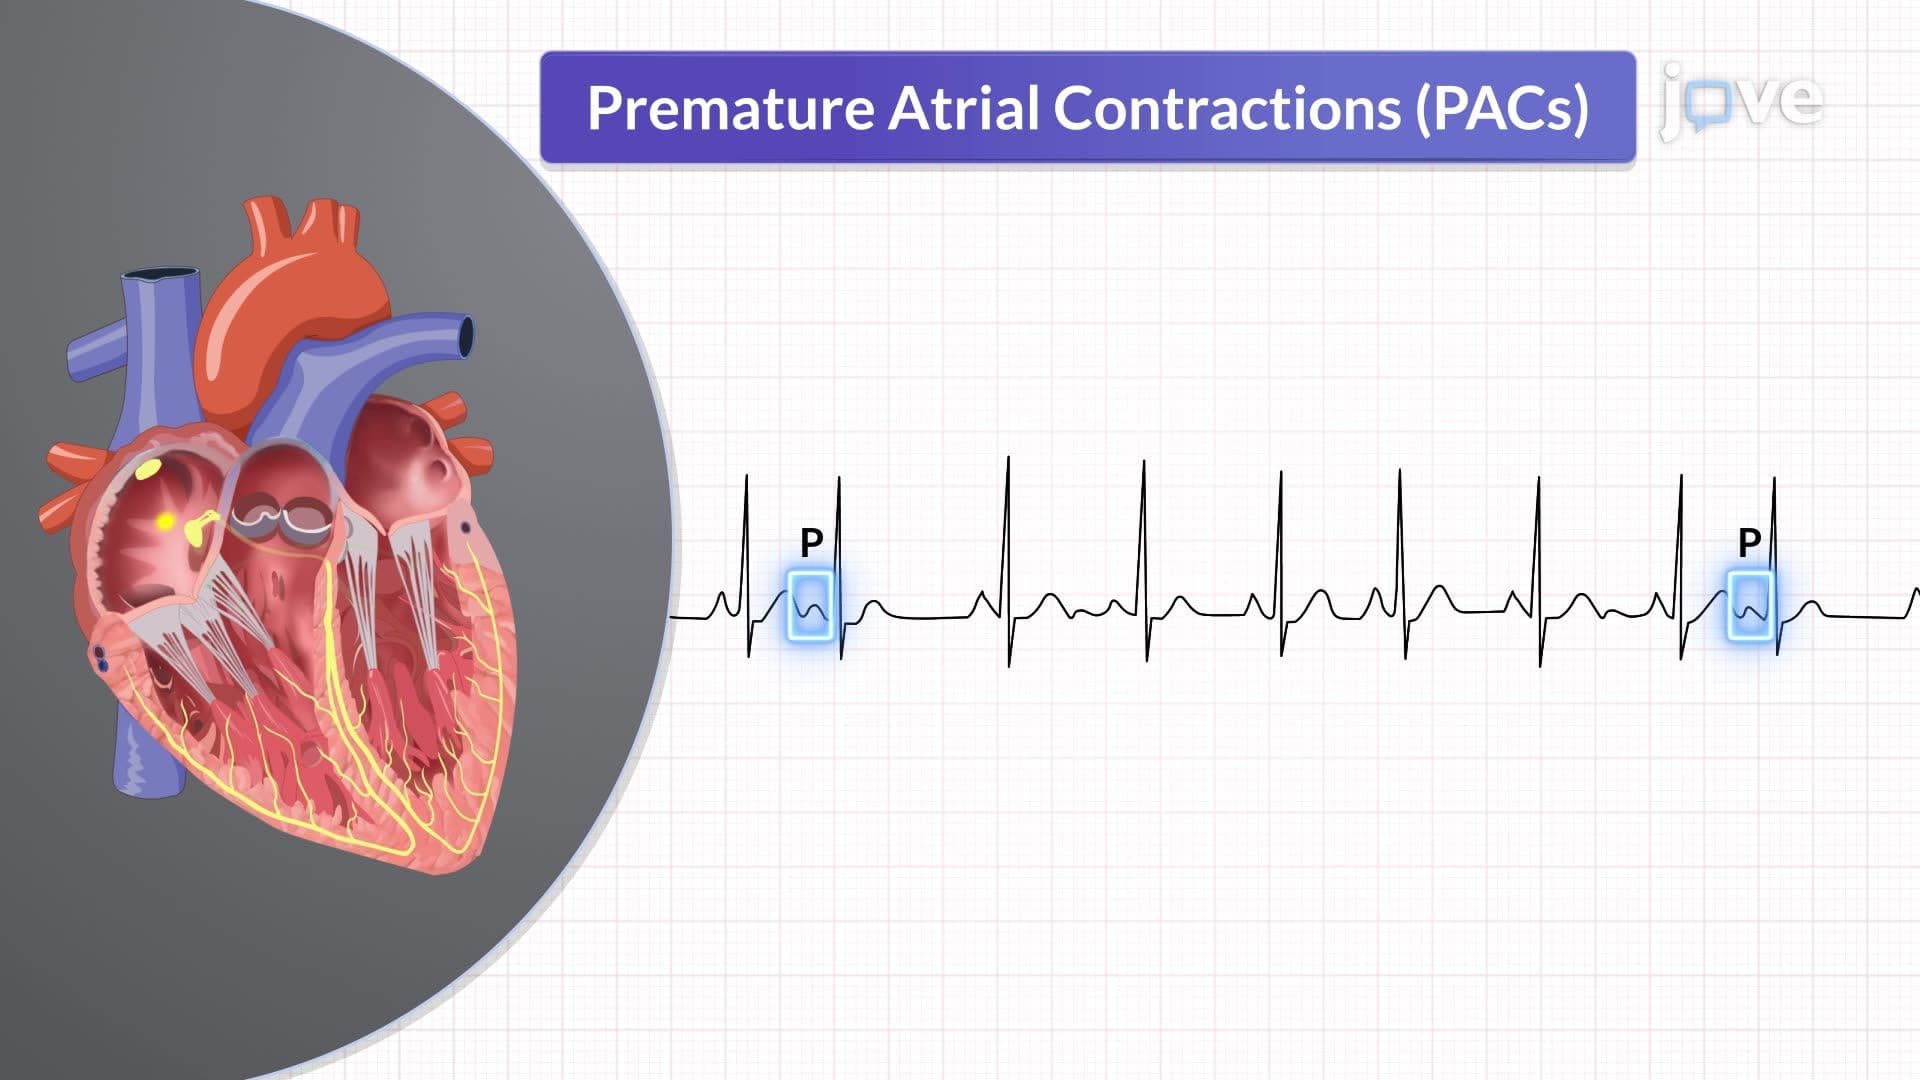 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias