Related Experiment Video
Updated: Aug 31, 2025
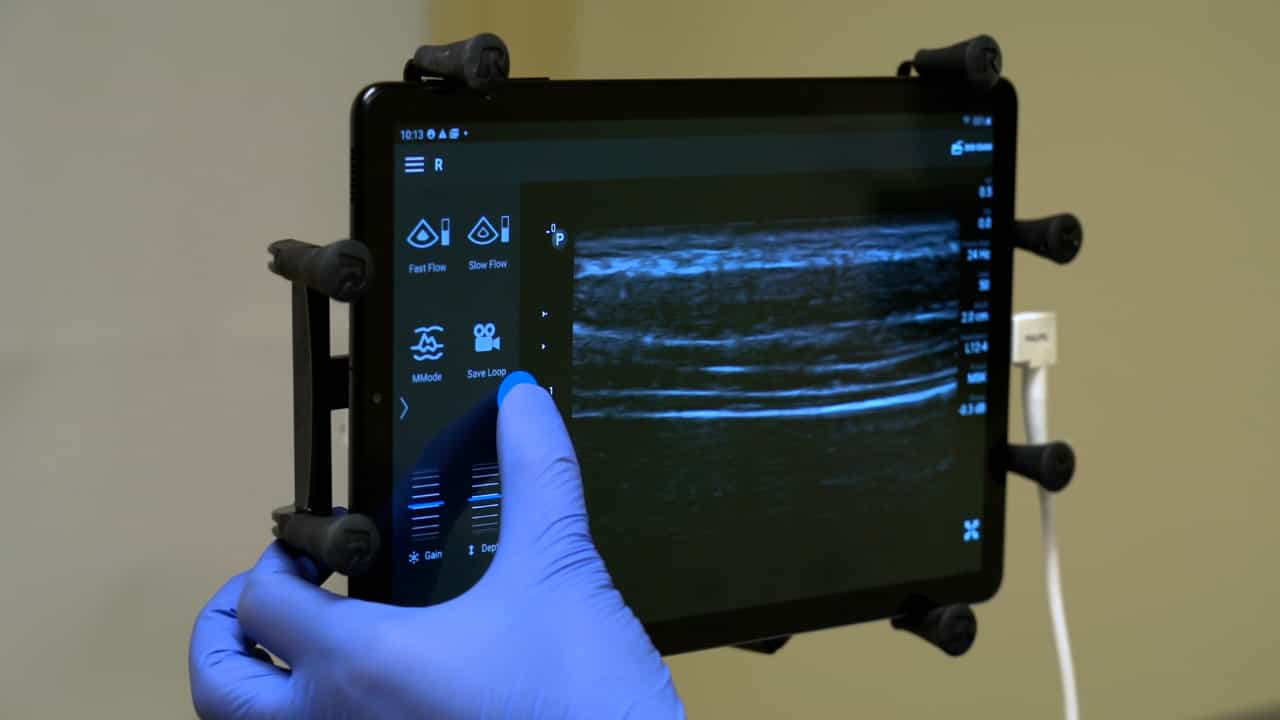

Author Spotlight: Unraveling the Impact of Mechanical Ventilation on Diaphragm Function and Patient Outcomes
Published on: November 3, 2023
Association between histological diaphragm atrophy and ultrasound diaphragm expiratory thickness in ventilated
Irene Dot1,2, Purificación Pérez-Terán1,2, Albert Francés3
1Critical Care Department, Hospital del Mar, Barcelona, Spain.

Background:
Diaphragm fiber atrophy has been evidenced after short periods of mechanical ventilation (MV) and related to critical illness-associated diaphragm weakness. Atrophy is described as a decrease in diaphragm fiber cross-sectional area (CSA) in human diaphragm biopsy, but human samples are still difficult to obtain in clinics. In recent years, ultrasound has become a useful tool in intensive care to evaluate diaphragm anatomy. The present study aimed to evaluate the ability of diaphragm expiratory thickness (Tdi) measured by ultrasound to predict diaphragm atrophy, defined by a decrease in diaphragm fiber CSA obtained through diaphragm biopsy (the gold standard technique) in ventilated patients.
Methods:
Diaphragm biopsies and diaphragm ultrasound were performed in ventilated donors and in control subjects. Demographic variables, comorbidities, severity on admission, treatment, laboratory test results and evolution variables were evaluated. Immunohistochemical analysis to determine CSA and ultrasound measurements of Tdi at end-expiration were performed, and median values of the control group were used as thresholds to determine agreement between them in further analysis. Sensitivity, specificity, and positive and negative predictive values of an ultrasound Tdi cutoff for detecting histologic atrophy were calculated. Agreement between two ultrasound observers was also assessed.
Results:
Thirty-five ventilated organ donors and 5 ventilated controls were included, without differences in basic characteristics. CSA and Tdi were lower in donors than in controls. All donors presented lower CSA, but only 74% lower Tdi regarding control group thresholds. The cut-off value for lower diaphragm expiratory thickness (Tdi < 1.7 mm) presented a sensitivity of 73%, a specificity of 67%, a positive predictive value of 96% and a negative predictive value of 17% for determining the presence of diaphragm atrophy (CSA < 2851 μm2).
Conclusions:
Diaphragm atrophy and thickness reduction is associated to MV. While a lower Tdi in diaphragm ultrasound is a good tool for diagnosing atrophy, normal or increased Tdi cannot rule atrophy out showing that both parameters should not be considered as synonymous.


Related Concept Videos
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:29
Physical Assessment of the Respiratory Tract III: Percussion
Percussion in Respiratory Assessment
Percussion evaluates underlying tissue composition with audible and tactile vibrations,...
 01:24
Physical Assessment of the Respiratory Tract II: Palpation
Thoracic Palpation
Thoracic palpation detects tenderness, masses, lesions, respiratory excursions, and vocal fremitus. The nurse assesses...
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities: