Related Experiment Video
Updated: Aug 31, 2025


Closure of a Patent Foramen Ovale PFO: An Intervention Sequence
Published on: December 23, 2022
Patent Foramen Ovale and Ascending Aortic Dilatation Causing Platypnea-Orthodeoxia Syndrome
Alaaeldin Ahmed1, Arashdeep Rupal1, Alexander Walker1
1Department of Medicine, Mount Auburn Hospital, Harvard Medical School, Cambridge, USA.

Abstract:
Platypnea-orthodeoxia syndrome (POS) is an underdiagnosed clinical syndrome characterized by dyspnea (platypnea) and hypoxemia (orthodeoxia) in the upright position that resolves when recumbent. POS is often due to an underlying right-to-left shunt. Four broad mechanisms for the shunt have been described: intracardiac shunts, intrapulmonary shunts, hepatopulmonary syndrome, and pulmonary ventilation-perfusion mismatch. A 68-year-old male with a past medical history of chronic obstructive pulmonary disease (COPD), obstructive sleep apnea, ascending aortic dilation (3.9 cm), myelofibrosis, and status post stem cell transplant complicated by graft versus host disease was found hypoxemic (oxygen saturation: 82%) on routine visit prompting hospitalization. Hypoxemia initially responded to 40% FiO2 but subsequently progressed to refractory hypoxemia on 100% FiO2. A chest computed tomography (CT) scan showed evidence of multiple segmental pulmonary emboli with patent central pulmonary arteries. Hypoxemia out of proportion to pulmonary embolism clot burden and examination findings consistent with orthodeoxia prompted further investigations. Nuclear medicine scan showed radiotracer activity in both brain and kidneys consistent with a small right-to-left shunt (5.9%). Transesophageal echocardiography (TEE) revealed a patent foramen ovale (PFO) with a right-to-left shunt across the atrial septum, with a maximum opening of 3.5 mm and tunnel length of 25 mm. Right heart catheterization (RHC) is consistent with the right-to-left shunt and normal right heart pressures. The degree of the shunt was not significant enough to explain the degree of hypoxemia, but all the diagnostic studies were performed in a supine position, possibly underestimating the degree of the shunt. PFO closure with transcatheter 30-mm Gore device (GORE® CARDIOFORM, Arizona, USA) decreased supplemental oxygen requirement from 75% high-flow nasal cannula (NC) to room air (RA) immediately after the procedure. The patient was subsequently discharged home on a baseline oxygen requirement of 2 L NC at nighttime. POS should be suspected when a patient develops severe hypoxemia after changing from a recumbent position to a sitting or standing position. The identification and correction of the shunting or mismatch often allow complete resolution of POS. Transthoracic echocardiography with agitated saline, TEE, and RHC are the diagnosis modalities of choice. Left heart cardiac catheterization remains the gold standard, which would demonstrate a mismatch in oxygen saturation between the pulmonary vein and the aorta. Our patient's PFO was successfully closed by a percutaneous transcatheter closure device leading to the complete resolution of hypoxemia immediately.
More Related Videos
 07:41
Echocardiographic Evaluation of Atrial Communications before Transcatheter Closure
Published on: February 8, 2022
 13:10
Direct Re-implantation of Left Coronary Artery into the Aorta in Adults with Anomalous Origin of Left Coronary Artery from the Pulmonary Artery ALCAPA
Published on: April 24, 2017
Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:25
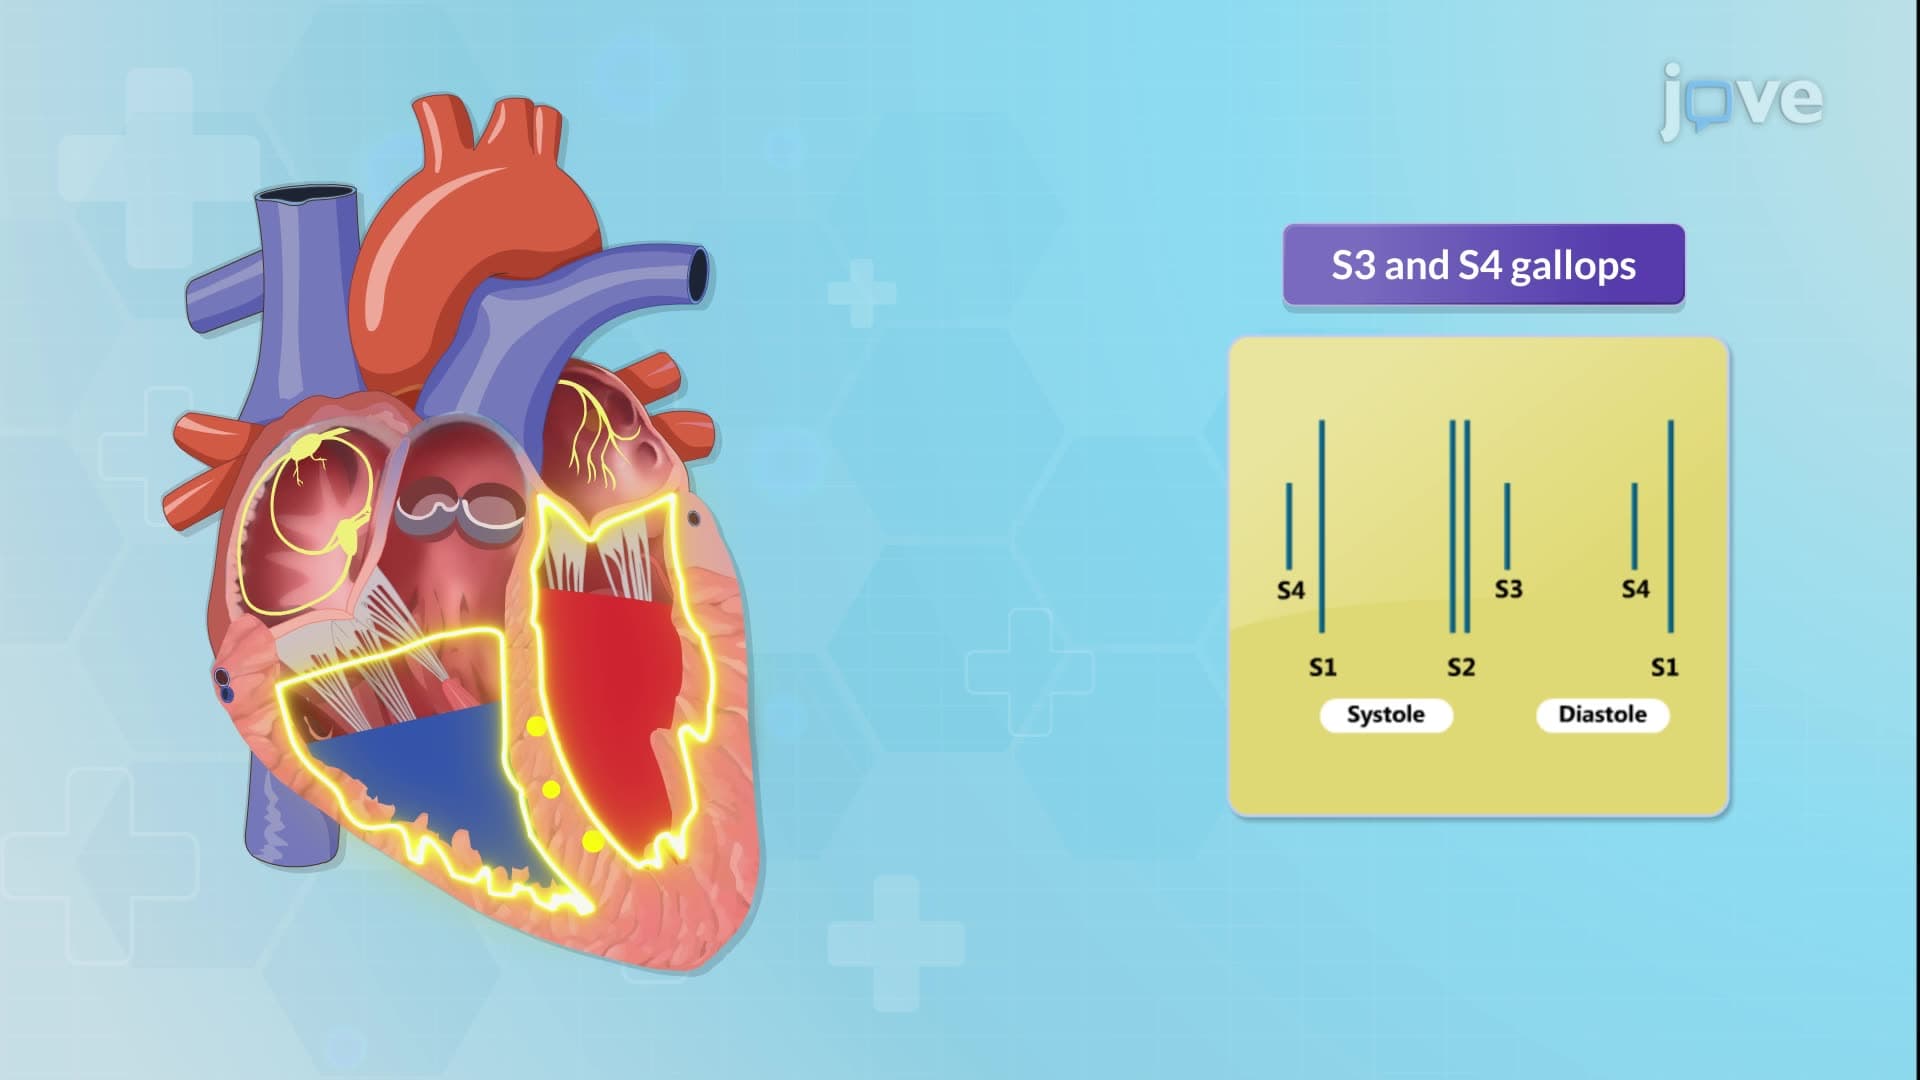
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:22
Mitral Stenosis I: Introduction
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:27
Mitral Valve Prolapse I: Introduction
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy