Related Experiment Video
Updated: Aug 31, 2025

Contractility Measurements of Human Uterine Smooth Muscle to Aid Drug Development
Published on: January 26, 2018
[Labor progression characteristics of primiparous term singleton pregnant women complicated with adenomyosis]
1Department of Obstetrics and Gynecology, Peking University Third Hospital, Beijing 100191, China.

Objective: To analyze the labor progression characteristics of primiparous term singleton pregnant women with adenomyosis. Methods: From April 2014 to May 2021, pregnant women underwent regular antenatal examination in Peking University Third Hospital were enrolled in this retrospective study, 109 primiparous term pregnant women with adenomyosis who underwent singleton, primipara, cephalic and vaginal delivery were referred as the adenomyosis group, while 109 pregnant women without adenomyosis primiparous term pregnant women at the same time were referred as the control group. The general clinical information, labor process intervention, pregnancy outcomes and labor course time of the two groups were analyzed. Results: (1) General clinical conditions: the pre-pregnancy uterine volume of the adenomyosis group was larger than that of the control group [(66.8±23.7) vs (41.4±13.1) cm3, P<0.05]. The proportion of assisted reproductive pregnancy and endometriosis in the adenomyosis group were higher than those in the control group [31.2% (34/109) vs 7.3% (8/109); 31.2% (34/109) vs 5.5% (6/109); all P<0.05]. There were no significant differences in maternal age, gestational age at delivery, pre-pregnancy body mass index, gestational weight gain, gravidity, incidence of pregnancy complications (gestational diabetes mellitus, pre-eclampsia and thyroid diseases) and premature rupture of membranes between the two groups (all P>0.05). (2) Labor process intervention and maternal and fetal outcomes: postpartum hemorrhage was higher in the adenomyosis group than the control group (median: 300 vs 260 ml, P=0.018). There were no significant differences in the proportion of labor onset, use of oxytocin, artificial rupture of membranes, perineal laceration Ⅲ and above, episiotomy, newborn weight and 1-minute Apgar score between the two groups (all P>0.05). (3) Time of labor process: there were no significant differences between the two groups in the time required for the first stage, third stage, total stage and cervical dilation 0-1, 1-2, 2-3, 3-4, 4-5, 5-6, 6-7 cm (all P>0.05). The time required for cervical dilation 7-8, 8-9, 9-10 cm and the second stage of labor in adenomyosis group (median: 20, 18, 15 and 12 minutes, respectively) were shorter than those of the control group (median: 23, 23, 23 and 26 minutes, respectively), and the differences were statistically significant (all P<0.05). (4) The effect of endometriosis on labor: there was no significant difference in the effect of endometriosis on labor in adenomyosis group (P>0.05). Conclusions: The labor process of primiparous term pregnant women with adenomyosis is significantly accelerated after the cervical dilatation for 7 cm, which should be closely observed. The third stage of labor course is managed aggressively with drugs to prevent postpartum hemorrhage.
Objective: To analyze the labor progression characteristics of primiparous term singleton pregnant women with adenomyosis. Methods: From April 2014 to May 2021, pregnant women underwent regular antenatal examination in Peking University Third Hospital were enrolled in this retrospective study, 109 primiparous term pregnant women with adenomyosis who underwent singleton, primipara, cephalic and vaginal delivery were referred as the adenomyosis group, while 109 pregnant women without adenomyosis primiparous term pregnant women at the same time were referred as the control group. The general clinical information, labor process intervention, pregnancy outcomes and labor course time of the two groups were analyzed. Results: (1) General clinical conditions: the pre-pregnancy uterine volume of the adenomyosis group was larger than that of the control group [(66.8±23.7) vs (41.4±13.1) cm3, P<0.05]. The proportion of assisted reproductive pregnancy and endometriosis in the adenomyosis group were higher than those in the control group [31.2% (34/109) vs 7.3% (8/109); 31.2% (34/109) vs 5.5% (6/109); all P<0.05]. There were no significant differences in maternal age, gestational age at delivery, pre-pregnancy body mass index, gestational weight gain, gravidity, incidence of pregnancy complications (gestational diabetes mellitus, pre-eclampsia and thyroid diseases) and premature rupture of membranes between the two groups (all P>0.05). (2) Labor process intervention and maternal and fetal outcomes: postpartum hemorrhage was higher in the adenomyosis group than the control group (median: 300 vs 260 ml, P=0.018). There were no significant differences in the proportion of labor onset, use of oxytocin, artificial rupture of membranes, perineal laceration Ⅲ and above, episiotomy, newborn weight and 1-minute Apgar score between the two groups (all P>0.05). (3) Time of labor process: there were no significant differences between the two groups in the time required for the first stage, third stage, total stage and cervical dilation 0-1, 1-2, 2-3, 3-4, 4-5, 5-6, 6-7 cm (all P>0.05). The time required for cervical dilation 7-8, 8-9, 9-10 cm and the second stage of labor in adenomyosis group (median: 20, 18, 15 and 12 minutes, respectively) were shorter than those of the control group (median: 23, 23, 23 and 26 minutes, respectively), and the differences were statistically significant (all P<0.05). (4) The effect of endometriosis on labor: there was no significant difference in the effect of endometriosis on labor in adenomyosis group (P>0.05). Conclusions: The labor process of primiparous term pregnant women with adenomyosis is significantly accelerated after the cervical dilatation for 7 cm, which should be closely observed. The third stage of labor course is managed aggressively with drugs to prevent postpartum hemorrhage.


Related Concept Videos
 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:27
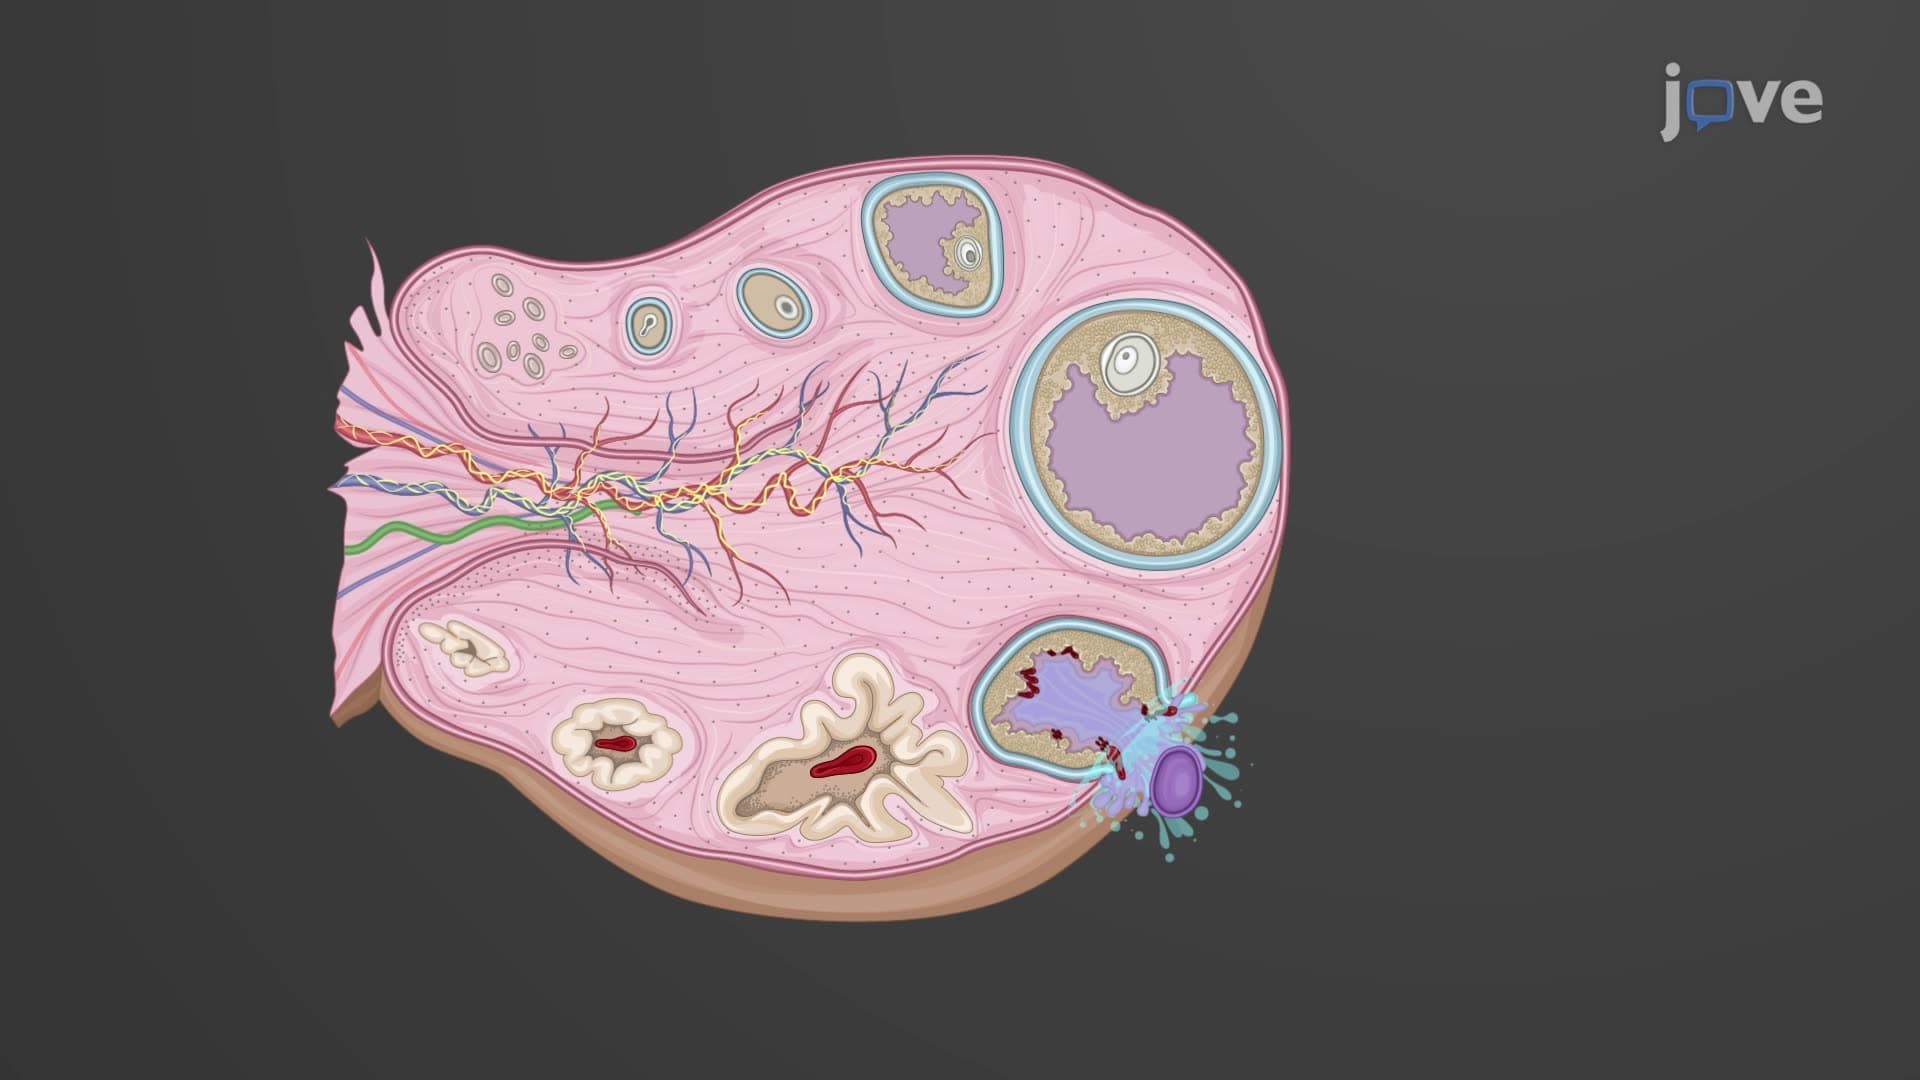
Ovarian Cycle
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a...
 01:19
Secretory Phase
Following ovulation, the corpus luteum, a temporary endocrine structure, produces progesterone and estrogens. These hormones stimulate the growth and coiling of endometrial...
 02:07
Tumor Progression
Colon cancer is one of the best-documented examples of tumor progression. Early mutation in the APC gene in colon cells causes a small growth on the colon wall called a polyp. With time, this polyp grows into a benign, pre-cancerous tumor. Further...
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...