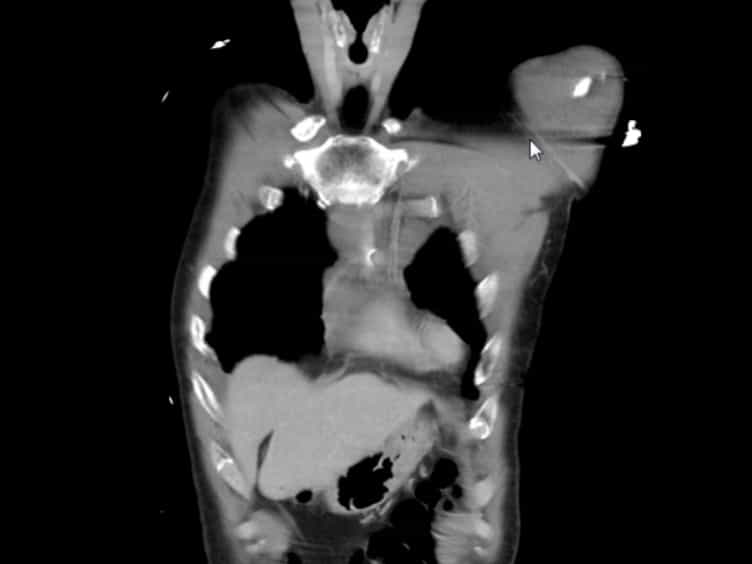

Acute clavicle fixation after blunt chest trauma: effect on pulmonary outcomes and patient disposition
Alexander Graf1, Derrick Wendler2, Tannor Court3
1Department of Orthopaedic Surgery, Medical College of Wisconsin, 9200 W. Wisconsin Ave, P.O. Box 26099, Milwaukee, WI, 53226-0099, USA. Agraf@mcw.edu.

Purpose:
Clavicle fractures are common in patients who sustain blunt chest trauma (BCT). Recently, surgical fixation of rib fractures in patients with BCT has been shown to improve pulmonary and clinical outcomes. Therefore, the purpose of this study is to assess the role of early clavicle fixation (ECF) versus non-operative (NO) treatment for midshaft clavicle fractures in this same population.
Methods:
A retrospective chart review was performed in patients with midshaft clavicle fractures and BCT at a Level I Trauma Center between 2007 and 2017. Patients with pre-existing pulmonary conditions and head injuries necessitating mechanical ventilation were excluded. Demographic data, injury mechanisms, and Thoracic Trauma Severity Scores (TTS) were analyzed. Inpatient pulmonary outcomes were assessed with serial vital capacity (VC) measurements, intubation, mechanical ventilation, and pulmonary complications data. In addition, intensive care unit (ICU) and hospital length of stay (LOS), mortality, discharge location, and incidence of postoperative complications in the ECF group were also measured.
Results:
Thirty-six patients underwent ECF, and 24 underwent NO treatment. The ECF cohort was statistically younger and had a greater incidence of clavicle fracture shortening than the NO group. There was no difference in pulmonary outcomes, ICU or hospital LOS, or mortality between groups. There were no complications associated with ECF. Patients who underwent ECF were more likely to discharge to home. There were no postoperative complications associated with ECF.
Conclusion:
ECF of midshaft clavicle fractures does not improve pulmonary outcomes in patients with BCT. However, despite the lack of pulmonary benefit, there appears to be no added risk of harm. Therefore, ECF is a reasonable consideration in this patient population who otherwise meet clavicle fracture operative indications.
More Related Videos

Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.