Related Experiment Video
Updated: Aug 30, 2025


A Retrospective Study on Endoscopic Surgery for the Treatment of Paravertebral Abscess in Spinal Tuberculosis Patients
Published on: October 25, 2024
Gauze for concern: A Case Report and systematic review of delayed presentation of paraspinal textiloma
Karthik Shyam1, Pushpa Bhari Thippeswamy1, Ajoy Prasad Shetty1
1Department of Radiology, Ganga Medical Center and Hospital, Mettupalayam Main Road, Coimbatore, Tamil Nadu, 641009, India.

Abstract:
Textilomas, gossypibomas, muslinomas and gauzomas, otherwise collectively known as Retained Non-absorbable Hemostatic Material (RNHM), are surgical materials such as cotton or gauze pads that are accidentally retained in the surgical bed post-operatively. They may present acutely with signs of infection or may rarely remain chronic and asymptomatic; the latter posing a significant challenge to clinical and imaging diagnosis. Textilomas are not routinely reported due to their medicolegal implications and are usually encountered fortuitously. Here, we report a case of an individual who presented with a non-specific lower backache, had a remote history of lumbar discectomy and in whom a textiloma at the postoperative site was seen to mimic a soft-tissue mass on imaging. In addition, we review current, up-to-date literature on delayed presentations of such retained materials after surgery of the lumbar spine.
Case Report:
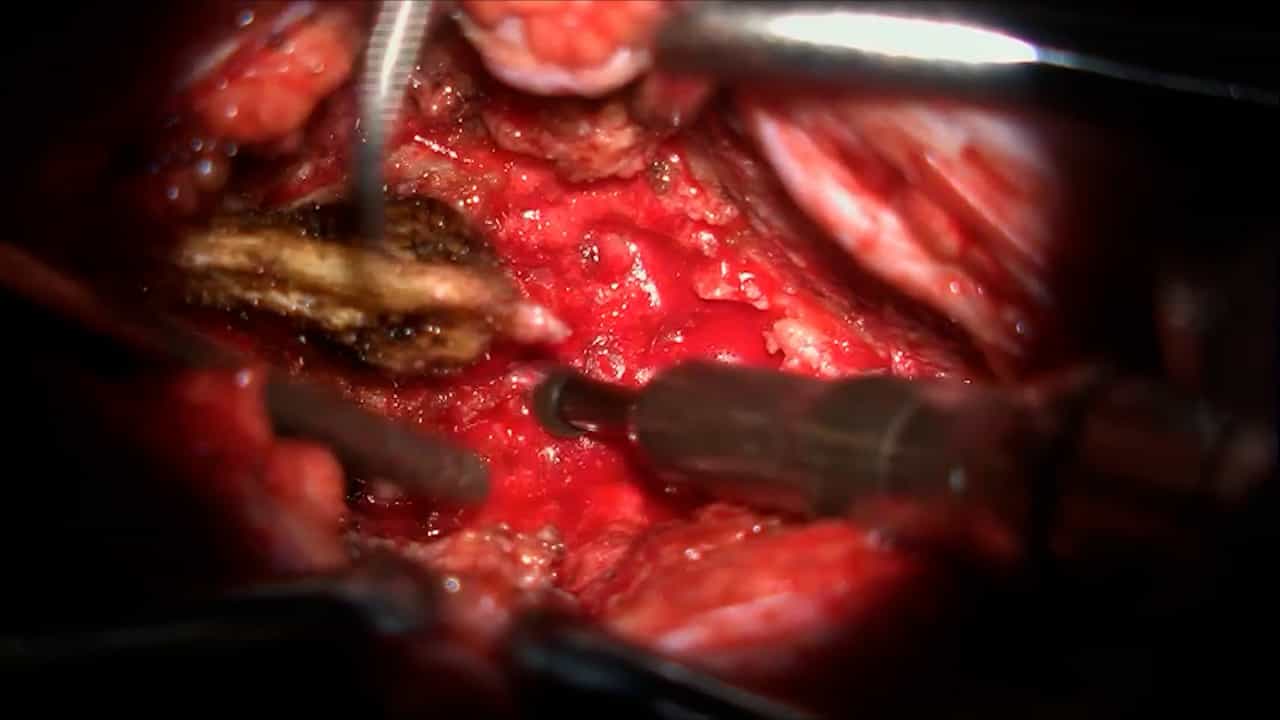
A 43-year-old male presented with pain in his right lower back and gluteal region. He had undergone an L4-L5 discectomy 11 years ago, remained asymptomatic since, and noticed an insidious, worsening pain a week before presentation. Mild tenderness was elicited over the region of pain. A clinical diagnosis of L4-L5 extraforaminal disc prolapse with deep surgical site infection was made. Ultrasound showed an iso-to-hyperechogenic lesion in the right lower paraspinal region. MRI showed a very well-defined, ovoid T1-hypointense and T2-iso-hypointense lesion in the deep posterior paraspinal region of the L4/5 level adjacent to right laminar process of L4 vertebra. The lesion caused scalloping and chronic erosion of the laminar process. No obvious air pockets were present. The features of infection, like soft tissue oedema and collection, were absent. Based on imaging, differentials of nerve sheath tumour and gossipybomas was made. Open wound exploration was performed, which showed a wad of gauze within the right L4-L5 interlaminar space, with thin surrounding granulation tissue. The L4-L5 disc and exiting nerve root were normal. The mass was removed, local washing was done and wound was closed.
Conclusion:
Though unfortunate and relatively rare, the possibility of a textiloma must be considered among the differential diagnoses of a mass in the spinal region in the event of prior surgery, no matter how remote the history. Clinical presentation may vary, but the imaging appearance is largely consistent and can be relied upon to prevent unnecessary investigation and facilitate early surgical removal of the offending retained material.
More Related Videos
 04:33
Spinal Hernia Repair and Cauda Equina Repositioning After Lumbar Decompression under Three-Dimensional Microscopy: A Case Report and Literature Review
Published on: November 8, 2024
 06:28
Biomechanical Changes Related to Low Back Pain: An Innovative Tool for Movement Pattern Assessment and Treatment Evaluation in Rehabilitation
Published on: December 13, 2024
