Related Experiment Video
Updated: Aug 29, 2025
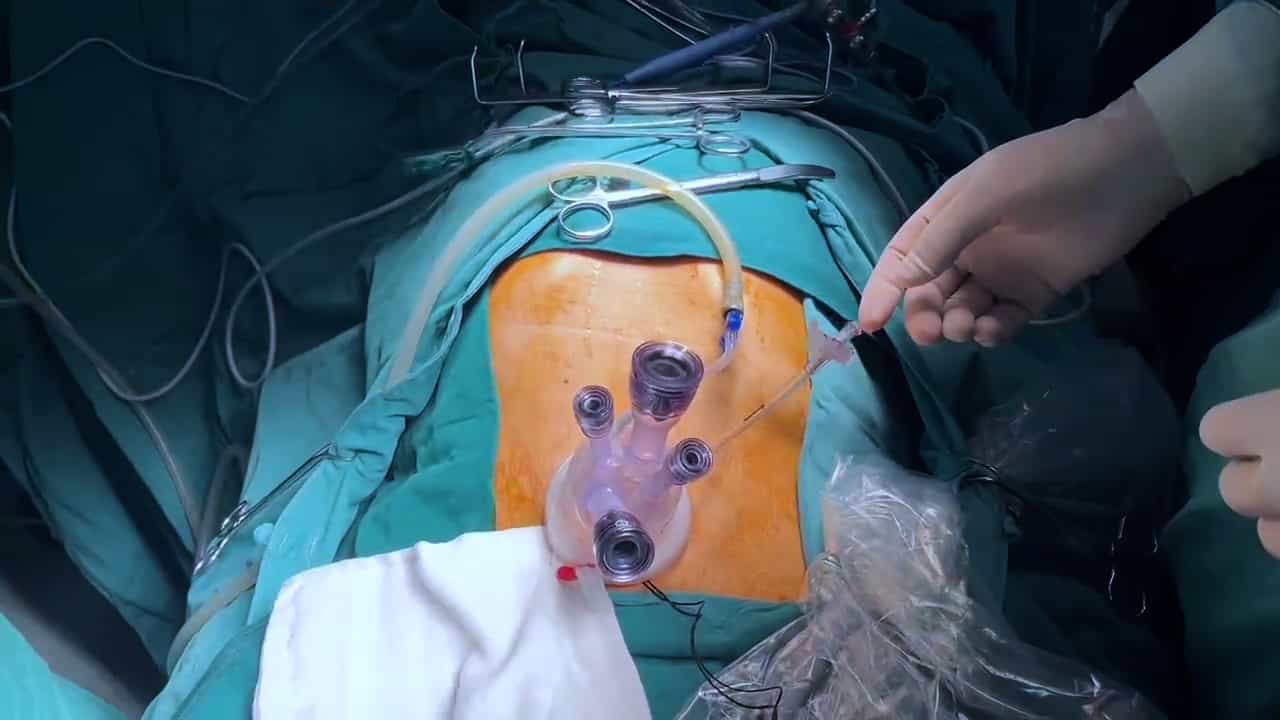
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
[A multicenter retrospective study on the efficacy of different anti-reflux reconstruction methods after proximal
1Department of General Surgery, the First Affiliated Hospital of Nanjing Medical University, Nanjing 210029, China.

Abstract:
Objective: To examine the clinical efficacy of 3 anti-reflux methods of digestive tract reconstruction after proximal gastrectomy for gastric cancer. Methods: The clinical data and follow-up data of gastric cancer patients who underwent anti-reflux reconstruction after proximal gastrectomy in 11 medical centers of China from September 2016 to August 2021 were retrospectively collected, including 273 males and 65 females, aging of (63±10) years (range: 28 to 91 years). Among them, 159 cases were performed with gastric tube anastomosis (GTA), 107 cases with double tract reconstruction (DTR), and 72 cases with double-flap technique (DFT), respectively. The duration of operation, length of postoperative hospital stay and early postoperative complications (referring to Clavien-Dindo classification) of different anti-reflux reconstruction methods were assessed. Body mass index, hemoglobin and albumin were used to reflect postoperative nutritional status. Reflux esophagitis was graded according to Los Angeles criteria based on the routinely gastroscopy within 12 months after surgery. The postoperative quality of life (QoL) was evaluated by Visick score system. The ANOVA analysis, Kruskal-Wallis rank sum test, χ2 test and Fisher's exact test were used for comparison between multiple groups, and further comparison among groups were performed with LSD, Tamhane's test or Bonferroni corrected χ2 test. The mixed effect model was used to compare the trends of Body mass index, hemoglobin and albumin over time among different groups. Results: The operation time of DFT was significantly longer than that of GTA and DTR ((352±63) minutes vs. (221±66) minutes, (352±63) minutes vs. (234±61) minutes, both P<0.01). The incidence of early complications with Clavien-Dindo grade Ⅱ to Ⅴ in GTA, DFT and DTR groups was 17.0% (27/159), 9.7% (7/72) and 10.3% (11/107), respectively, without significant difference among these three groups (χ2=3.51, P=0.173). Body mass index decreased more significantly in GTA than DFT group at 6 and 12 months after surgery (mean difference=1.721 kg/m2, P<0.01; mean difference=2.429 kg/m2, P<0.01). body mass index decreased significantly in DTR compared with DFT at 12 months after surgery (mean difference=1.319 kg/m2, P=0.027). There was no significant difference in hemoglobin or albumin fluctuation between different reconstruction methods perioperative. The incidence of reflux esophagitis one year after surgery in DTR group was 12.9% (4/31), which was lower than that in DFT (45.9% (17/37), χ2=8.63, P=0.003). Follow-up of postoperative quality of life showed the incidence of Visick grade 2 to 4 in DFT group was lower than that in GTA group (10.4% (7/67) vs. 34.6% (27/78), χ2=11.70, P=0.018), while there was no significant difference between DFT and DTR group (10.4% (7/67) vs. 22.2% (8/36, P>0.05). Conclusions: Compared with GTA and DTR, DFT is more time-consuming, but there is no significant difference in early complications among three methods. DFT reconstruction is more conducive to maintain postoperative nutritional status and improve QoL, especially compared with GTA. The risk of reflux esophagitis after DTR reconstruction is lower than that of DFT.


Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...