Related Experiment Video
Updated: Aug 29, 2025
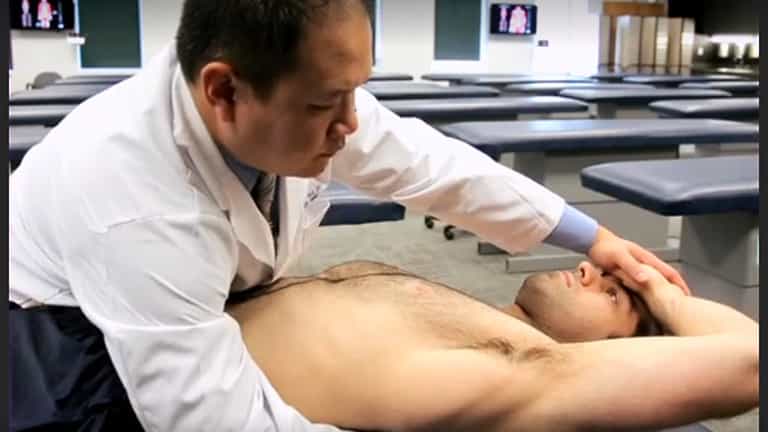
Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
Chest physiotherapy for pneumonia in adults
Xiaomei Chen1, Jiaojiao Jiang2, Renjie Wang2
1Department of Dermatology & Venereology, West China Hospital, Sichuan University, Chengdu, China.

Background:
Despite conflicting evidence, chest physiotherapy has been widely used as an adjunctive treatment for adults with pneumonia. This is an update of a review first published in 2010 and updated in 2013.
Objectives:
To assess the effectiveness and safety of chest physiotherapy for pneumonia in adults.
Search Methods:
We updated our searches in the following databases to May 2022: the Cochrane Central Register of Controlled Trials (CENTRAL) via OvidSP, MEDLINE via OvidSP (from 1966), Embase via embase.com (from 1974), Physiotherapy Evidence Database (PEDro) (from 1929), CINAHL via EBSCO (from 2009), and the Chinese Biomedical Literature Database (CBM) (from 1978).
Selection Criteria:
Randomised controlled trials (RCTs) and quasi-RCTs assessing the efficacy of chest physiotherapy for treating pneumonia in adults.
Data Collection And Analysis:
We used standard methodological procedures expected by Cochrane.
Main Results:
We included two new trials in this update (540 participants), for a total of eight RCTs (974 participants). Four RCTs were conducted in the United States, two in Sweden, one in China, and one in the United Kingdom. The studies looked at five types of chest physiotherapy: conventional chest physiotherapy; osteopathic manipulative treatment (OMT, which includes paraspinal inhibition, rib raising, and myofascial release); active cycle of breathing techniques (which includes active breathing control, thoracic expansion exercises, and forced expiration techniques); positive expiratory pressure; and high-frequency chest wall oscillation. We assessed four trials as at unclear risk of bias and four trials as at high risk of bias. Conventional chest physiotherapy (versus no physiotherapy) may have little to no effect on improving mortality, but the certainty of evidence is very low (risk ratio (RR) 1.03, 95% confidence interval (CI) 0.15 to 7.13; 2 trials, 225 participants; I² = 0%). OMT (versus placebo) may have little to no effect on improving mortality, but the certainty of evidence is very low (RR 0.43, 95% CI 0.12 to 1.50; 3 trials, 327 participants; I² = 0%). Similarly, high-frequency chest wall oscillation (versus no physiotherapy) may also have little to no effect on improving mortality, but the certainty of evidence is very low (RR 0.75, 95% CI 0.17 to 3.29; 1 trial, 286 participants). Conventional chest physiotherapy (versus no physiotherapy) may have little to no effect on improving cure rate, but the certainty of evidence is very low (RR 0.93, 95% CI 0.56 to 1.55; 2 trials, 225 participants; I² = 85%). Active cycle of breathing techniques (versus no physiotherapy) may have little to no effect on improving cure rate, but the certainty of evidence is very low (RR 0.60, 95% CI 0.29 to 1.23; 1 trial, 32 participants). OMT (versus placebo) may improve cure rate, but the certainty of evidence is very low (RR 1.59, 95% CI 1.01 to 2.51; 2 trials, 79 participants; I² = 0%). OMT (versus placebo) may have little to no effect on mean duration of hospital stay, but the certainty of evidence is very low (mean difference (MD) -1.08 days, 95% CI -2.39 to 0.23; 3 trials, 333 participants; I² = 50%). Conventional chest physiotherapy (versus no physiotherapy, MD 0.7 days, 95% CI -1.39 to 2.79; 1 trial, 54 participants) and active cycle of breathing techniques (versus no physiotherapy, MD 1.4 days, 95% CI -0.69 to 3.49; 1 trial, 32 participants) may also have little to no effect on duration of hospital stay, but the certainty of evidence is very low. Positive expiratory pressure (versus no physiotherapy) may reduce the mean duration of hospital stay by 1.4 days, but the certainty of evidence is very low (MD -1.4 days, 95% CI -2.77 to -0.03; 1 trial, 98 participants). Positive expiratory pressure (versus no physiotherapy) may reduce the duration of fever by 0.7 days, but the certainty of evidence is very low (MD -0.7 days, 95% CI -1.36 to -0.04; 1 trial, 98 participants). Conventional chest physiotherapy (versus no physiotherapy, MD 0.4 days, 95% CI -1.01 to 1.81; 1 trial, 54 participants) and OMT (versus placebo, MD 0.6 days, 95% CI -1.60 to 2.80; 1 trial, 21 participants) may have little to no effect on duration of fever, but the certainty of evidence is very low. OMT (versus placebo) may have little to no effect on the mean duration of total antibiotic therapy, but the certainty of evidence is very low (MD -1.07 days, 95% CI -2.37 to 0.23; 3 trials, 333 participants; I² = 61%). Active cycle of breathing techniques (versus no physiotherapy) may have little to no effect on duration of total antibiotic therapy, but the certainty of evidence is very low (MD 0.2 days, 95% CI -4.39 to 4.69; 1 trial, 32 participants). High-frequency chest wall oscillation plus fibrobronchoscope alveolar lavage (versus fibrobronchoscope alveolar lavage alone) may reduce the MD of intensive care unit (ICU) stay by 3.8 days (MD -3.8 days, 95% CI -5.00 to -2.60; 1 trial, 286 participants) and the MD of mechanical ventilation by three days (MD -3 days, 95% CI -3.68 to -2.32; 1 trial, 286 participants), but the certainty of evidence is very low. One trial reported transient muscle tenderness emerging after OMT in two participants. In another trial, three serious adverse events led to early withdrawal after OMT. One trial reported no adverse events after positive expiratory pressure treatment. Limitations of this review were the small sample size and unclear or high risk of bias of the included trials.
Authors' Conclusions:
The inclusion of two new trials in this update did not change the main conclusions of the original review. The current evidence is very uncertain about the effect of chest physiotherapy on improving mortality and cure rate in adults with pneumonia. Some physiotherapies may slightly shorten hospital stays, fever duration, and ICU stays, as well as mechanical ventilation. However, all of these findings are based on very low certainty evidence and need to be further validated.
More Related Videos
 07:10
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
 05:19
Author Spotlight: An Effective Traditional Chinese Medicinal Treatment for Chronic Obstructive Pulmonary Disease with Abdominal Distension
Published on: September 1, 2023
Related Concept Videos
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Pneumonia III: Complications and Assessment
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: