Related Experiment Video
Updated: Aug 29, 2025
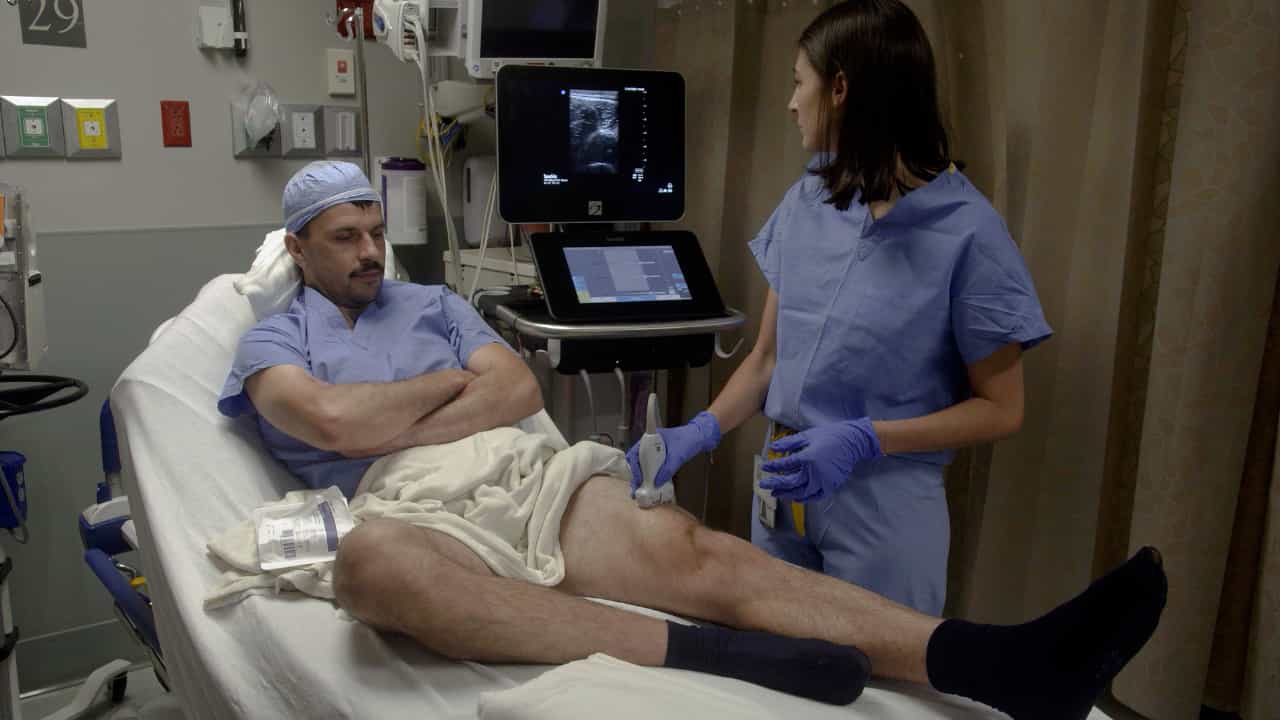

Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Comparison of Multidimensional Frailty Instruments for Estimation of Long-term Patient-Centered Outcomes After
Louise Y Sun1,2,3, Habib Jabagi4, Jiming Fang2
1Division of Cardiac Anesthesiology, University of Ottawa Heart Institute, Ottawa, Ontario, Canada.

Insights
Frailty instruments like ACG, HFRS, and PFI predict patient outcomes after cardiac surgery. HFRS and PFI showed varying performance over time for predicting adverse events and mortality.
Area of Science:
- Cardiology
- Gerontology
- Health Services Research
Background:
- Frailty assessment is crucial for predicting patient outcomes after cardiac surgery.
- Limited data exists on the comparative performance of existing frailty instruments for patient-relevant outcomes.
Purpose of the Study:
- To evaluate the accuracy of the Johns Hopkins Adjusted Clinical Groups (ACG) frailty indicator, Hospital Frailty Risk Score (HFRS), and Preoperative Frailty Index (PFI) in predicting long-term patient-centered outcomes post-cardiac surgery.
Main Methods:
- Retrospective cohort study of adult cardiac surgery patients in Ontario, Canada (2008-2017).
- Primary outcome: patient-defined adverse cardiovascular and noncardiovascular events (PACE). Secondary outcomes: mortality.
- Cause-specific hazard and Cox models used to assess frailty's association with outcomes; AUROC curves calculated over 10 years.
Main Results:
- All three frailty instruments (ACG, HFRS, PFI) were associated with increased rates of PACE and mortality.
- The Hospital Frailty Risk Score (HFRS) demonstrated the highest predictive accuracy for PACE in the initial 2 years and mortality in the first 4 years.
- The Preoperative Frailty Index (PFI) showed higher predictive accuracy for longer-term outcomes after the initial periods.
Conclusions:
- Frailty instruments effectively predict patient-relevant outcomes and mortality after cardiac surgery.
- The choice of frailty instrument may depend on the specific outcome and follow-up duration.
- Findings support optimizing risk stratification and personalized care for cardiac surgery patients.
Importance:
Little is known about the performance of available frailty instruments in estimating patient-relevant outcomes after cardiac surgery.
Objective:
To examine how well the Johns Hopkins Adjusted Clinical Groups (ACG) frailty indicator, the Hospital Frailty Risk Score (HFRS), and the Preoperative Frailty Index (PFI) estimate long-term patient-centered outcomes after cardiac surgery.
Design, Setting, And Participants:
This retrospective cohort study was conducted in Ontario, Canada, among residents 18 years and older who underwent coronary artery bypass grafting or aortic, mitral or tricuspid valve, or thoracic aorta surgery between October 2008 and March 2017. Long-term care residents, those with discordant surgical encounters, and those receiving dialysis or dependent on a ventilator within 90 days were excluded. Statistical analysis was conducted from July 2021 to January 2022.
Main Outcomes And Measures:
The primary outcome was patient-defined adverse cardiovascular and noncardiovascular events (PACE), defined as the composite of severe stroke, heart failure, long-term care admission, new-onset dialysis, and ventilator dependence. Secondary outcomes included mortality and individual PACE events. The association between frailty and PACE was examined using cause-specific hazard models with death as a competing risk, and the association between frailty and death was examined using Cox models. Areas under the receiver operating characteristic curve (AUROC) were determined over 10 years of follow-up for each frailty instrument.
Results:
Of 88 456 patients (22 924 [25.9%] female; mean [SD] age, 66.3 [11.1] years), 14 935 (16.9%) were frail according to ACG criteria, 63 095 (71.3%) according to HFRS, and 76 754 (86.8%) according to PFI. Patients with frailty were more likely to be older, female, and rural residents; to have lower income and multimorbidity; and to undergo urgent surgery. Patients meeting ACG criteria (hazard ratio [HR], 1.66; 95% CI, 1.60-1.71) and those with higher HFRS scores (HR per 1.0-point increment, 1.10; 95% CI, 1.09-1.10) and PFI scores (HR per 0.1-point increment, 1.75; 95% CI, 1.73-1.78) had higher rates of PACE. Similar magnitudes of association were observed for each frailty instrument with death and individual PACE components. The HFRS had the highest AUROC for estimating PACE during the first 2 years and death during the first 4 years, after which the PFI had the highest AUROC.
Conclusions And Relevance:
These findings could help to tailor the use of frailty instruments by outcome and follow-up duration, thus optimizing preoperative risk stratification, patient-centered decision-making, candidate selection for prehabilitation, and personalized monitoring and health resource planning in patients undergoing cardiac surgery.
More Related Videos
 05:53
Measuring Frailty in HIV-infected Individuals. Identification of Frail Patients is the First Step to Amelioration and Reversal of Frailty
Published on: July 24, 2013
 06:52
Assessment of Dependence in Activities of Daily Living Among Older Patients in an Acute Care Unit
Published on: September 30, 2020