Related Experiment Video
Updated: Aug 29, 2025


Antigenic Liposomes for Generation of Disease-specific Antibodies
Published on: October 25, 2018
Management of antibiotic allergy in children: a practical approach
Nikolaos Kitsos1, Dimitrios Cassimos2, Ioannis Xinias3
1Allergy Unit, 3rd Pediatric Department, Aristotle University of Thessaloniki, Thessaloniki, Greece; nkitsos@gmail.com.

Insights
Many children are labeled with antibiotic allergies, but few are confirmed. Proper diagnostic workup is crucial to avoid unnecessary broad-spectrum antibiotic use and its associated healthcare costs and resistance.
Area of Science:
- Pediatric Allergy and Immunology
- Clinical Pharmacology
- Infectious Diseases
Background:
- Approximately 10% of children are diagnosed with antibiotic allergies, most commonly to beta-lactam antibiotics.
- A significant number of these diagnoses are not confirmed by allergy testing.
- Unconfirmed antibiotic allergies lead to the use of alternative, more expensive broad-spectrum antibiotics, contributing to antibiotic resistance and increased healthcare costs.
Purpose of the Study:
- To present a practical approach for managing pediatric patients experiencing antibiotic hypersensitivity reactions.
- To provide updated guidelines for diagnosing and managing antibiotic allergy in children.
Main Methods:
- Systematic literature review using PubMed with keywords "antibiotic allergy" and "children."
- Analysis of 5165 retrieved citations to update existing guidelines.
- Focus on evidence-based approaches for diagnosis and management.
Main Results:
- Management strategies vary based on the specific antibiotic implicated.
- Penicillin-allergic patients may tolerate cephalosporins, particularly third-generation ones, if R1 side chains differ.
- For cephalosporin or macrolide allergies, challenge tests or skin tests with different side chains are recommended. Sulfonamide hypersensitivity is best managed with alternative antibiotics.
- Skin tests are not recommended for quinolone allergy; a quinolone challenge test is the most appropriate diagnostic tool.
Conclusions:
- Immunologically mediated antibiotic hypersensitivity is less common than reported adverse drug reactions.
- Accurate diagnostic workup is essential to confirm the causal role of an antibiotic in a hypersensitivity reaction.
- Avoiding the premature "labeling" of children as antibiotic-allergic without proper evaluation is critical to prevent overuse of broad-spectrum antibiotics.
Background:
About 10% of children are declared as allergic to antibiotics, with beta(β)-lactams being the most common perpetrators. However, few of these are confirmed by allergy tests. This characteristic of being allergic follows a child well into adulthood, leading to alternative, usually more expensive broad-spectrum antibiotics, contributing to antibiotic resistance and increasing healthcare expenses.
Objective:
This review presents a practical approach to managing pediatric patients with antibiotic hypersensitivity reactions.
Material And Methods:
We updated the guidelines on antibiotic allergy in children by conducting systematic literature research using the best available evidence from PubMed search by entering the keywords "antibiotic allergy" and "children." The search output yielded 5165 citations.
Results:
Management of antibiotic allergy depends on the culprit antibiotic, and it includes confirmation of the diagnosis and finding a safe alternative to the culprit antibiotic. In particular patients with a history indicative of penicillin allergy can be treated with cephalosporins as an alternative to penicillin, especially with third-generation cephalosporins, except for those with similar R1 side chains. In patients with a history of immediate-type reactions to cephalosporins who require treatment with cephalosporins or penicillin, skin tests with cephalosporin or penicillin with different side chains should be performed. If allergy to macrolides is suspected, challenge tests are currently the only reliable diagnostic tool. The best strategy for managing patients with sulfonamide hypersensitivity is an alternative antibiotic. The skin prick tests and intradermal tests are not recommended for diagnosis of quinolone allergy, as they can activate dermal mast cells leading to false-positive results. Quinolone challenge test is the most appropriate test for diagnosing quinolone hypersensitivity.
Conclusion:
Although adverse drug reactions to antibiotics are frequently documented, immunologically mediated hypersensitivity is unusual. In the event of an reaction, an appropriate diagnostic workup is required to identify the drug's causal role. It is critical to avoid "labeling" a child as allergic without first conducting a proper diagnostic workup.


Related Concept Videos
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 02:06
Allergic Reactions
 01:26
Tonsillitis II: Management
 01:30
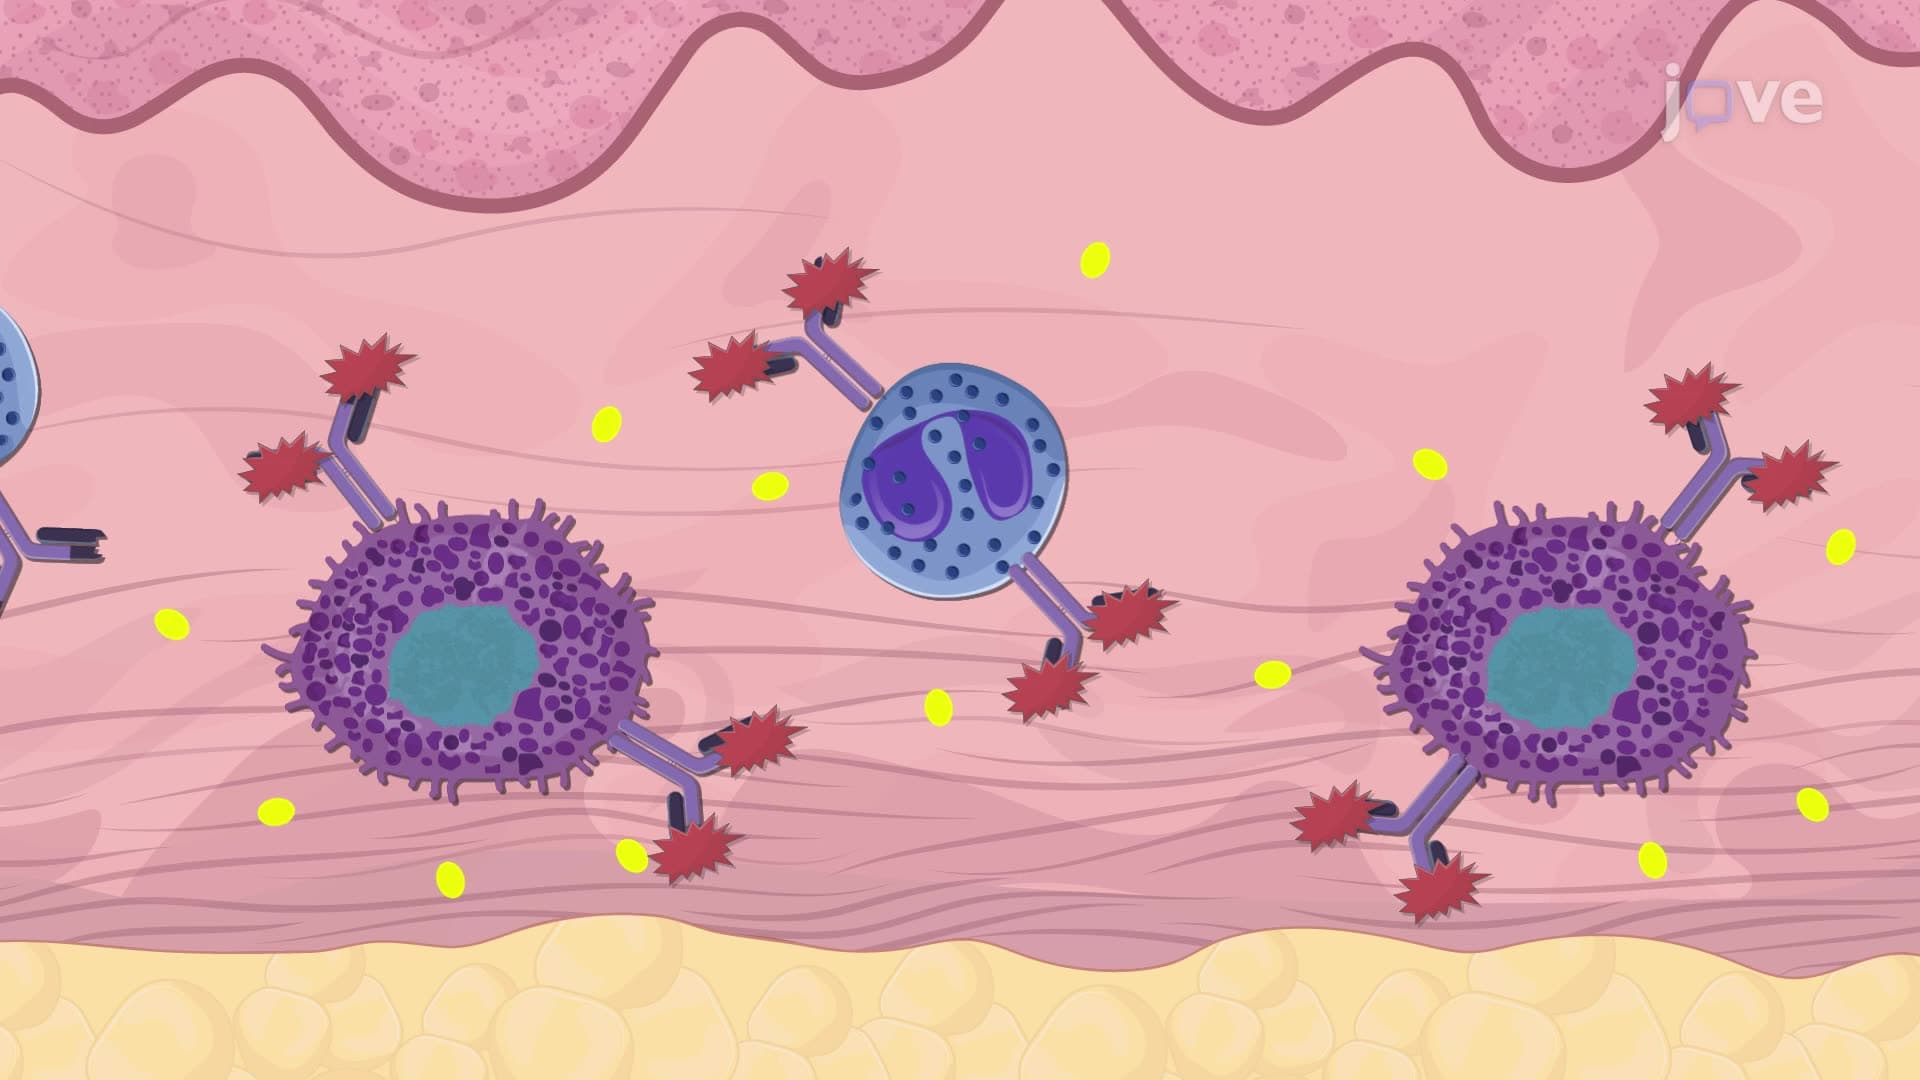
Hypersensitivities
Types of Hypersensitivities
Hypersensitivity reactions are categorized into four types: Type 1, Type 2, Type 3, and Type 4. Each type has a distinct mechanism...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms: