Related Experiment Video
Updated: Aug 29, 2025


Quantifying Arms and Legs Contributions during Repetitive Electrically-Assisted Sit-To-Stand Exercise in Paraplegics: A Pilot Study
Published on: November 11, 2022
Reliability and validity of sit-to-stand test protocols in patients with coronary artery disease
Zheng Wang1, Jianhua Yan2, Shu Meng2
1Department of Sport Rehabilitation, School of Kinesiology, Shanghai University of Sport, Shanghai, China.

Background:
Sit-To-Stand (STS) tests are reported as feasible alternatives for the assessment of functional fitness but the reliability of these tests in people with coronary artery disease (CAD) has not been reported. This study explored the test-retest reliability, convergent and known-groups validity of the five times, 30-sec and 1-min sit-to-stand test (FTSTS test, 30-s STS test and 1-min STS test respectively) in patients with CAD. The feasibility of applying these tests to distinguish the level of risk for cardiovascular events in CAD patients was also investigated.
Methods:
Patients with stable CAD performed a 6MWT and 3 STS tests in random order on the same day. Receiver operating characteristic (ROC) curve analyses were conducted using STS test data to differentiate patients with low or high risk of cardiovascular events based on the risk level determined by distance covered in the 6MWT as > or ≤ 419 m. Thirty patients repeated the 3 STS tests on the following day.
Results:
112 subjects with diagnoses of atherosclerosis or post-percutaneous coronary intervention, or post-acute myocardial infarction (post-AMI) participated in the validity analysis. All 3 STS tests demonstrated moderate and significant correlation with the 6MWT (coefficient values r for the FTSTS, 30-s STS and 1-min STS tests were-0.53, 0.57 and 0.55 respectively). Correlations between left ventricular ejection fraction (LVEF) and all STS tests and between 6MWT and LVEF were only weak (r values ranged from 0.27 to 0.31). Subgroup analysis showed participants in the post-AMI group performed worse in all tests compared to non-myocardial infarction (non-MI) group. The area under the curve (AUC) was 0.80 for FTSTS (sensitivity: 75.0%, specificity: 73.8%, optimal cut-off: >11.7 sec), and the AUC, sensitivity, specificity and optimal cut-off for 30-s STS and 1-min STS test were 0.83, 75.0%, 76.2%, ≤ 12 repetitions and 0.80, 71.4%, 73.8%, ≤ 23 repetitions respectively. The intraclass correlation coefficients (ICC) for repeated measurements of the FTSTS, 30-s STS and 1-min STS tests were 0.96, 0.95 and 0.96 respectively, with the minimal detectable change (MDC95) computed to be 1.1 sec 1.8 repetitions and 3.9 repetitions respectively.
Conclusions:
All STS tests demonstrated good test-retest reliability, convergent and known-groups validity. STS tests may discriminate low from high levels of risk for a cardiovascular event in patients with CAD.
More Related Videos
 08:24
Sit-to-stand-and-walk from 120% Knee Height: A Novel Approach to Assess Dynamic Postural Control Independent of Lead-limb
Published on: August 30, 2016
 07:10
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Related Concept Videos
 01:26
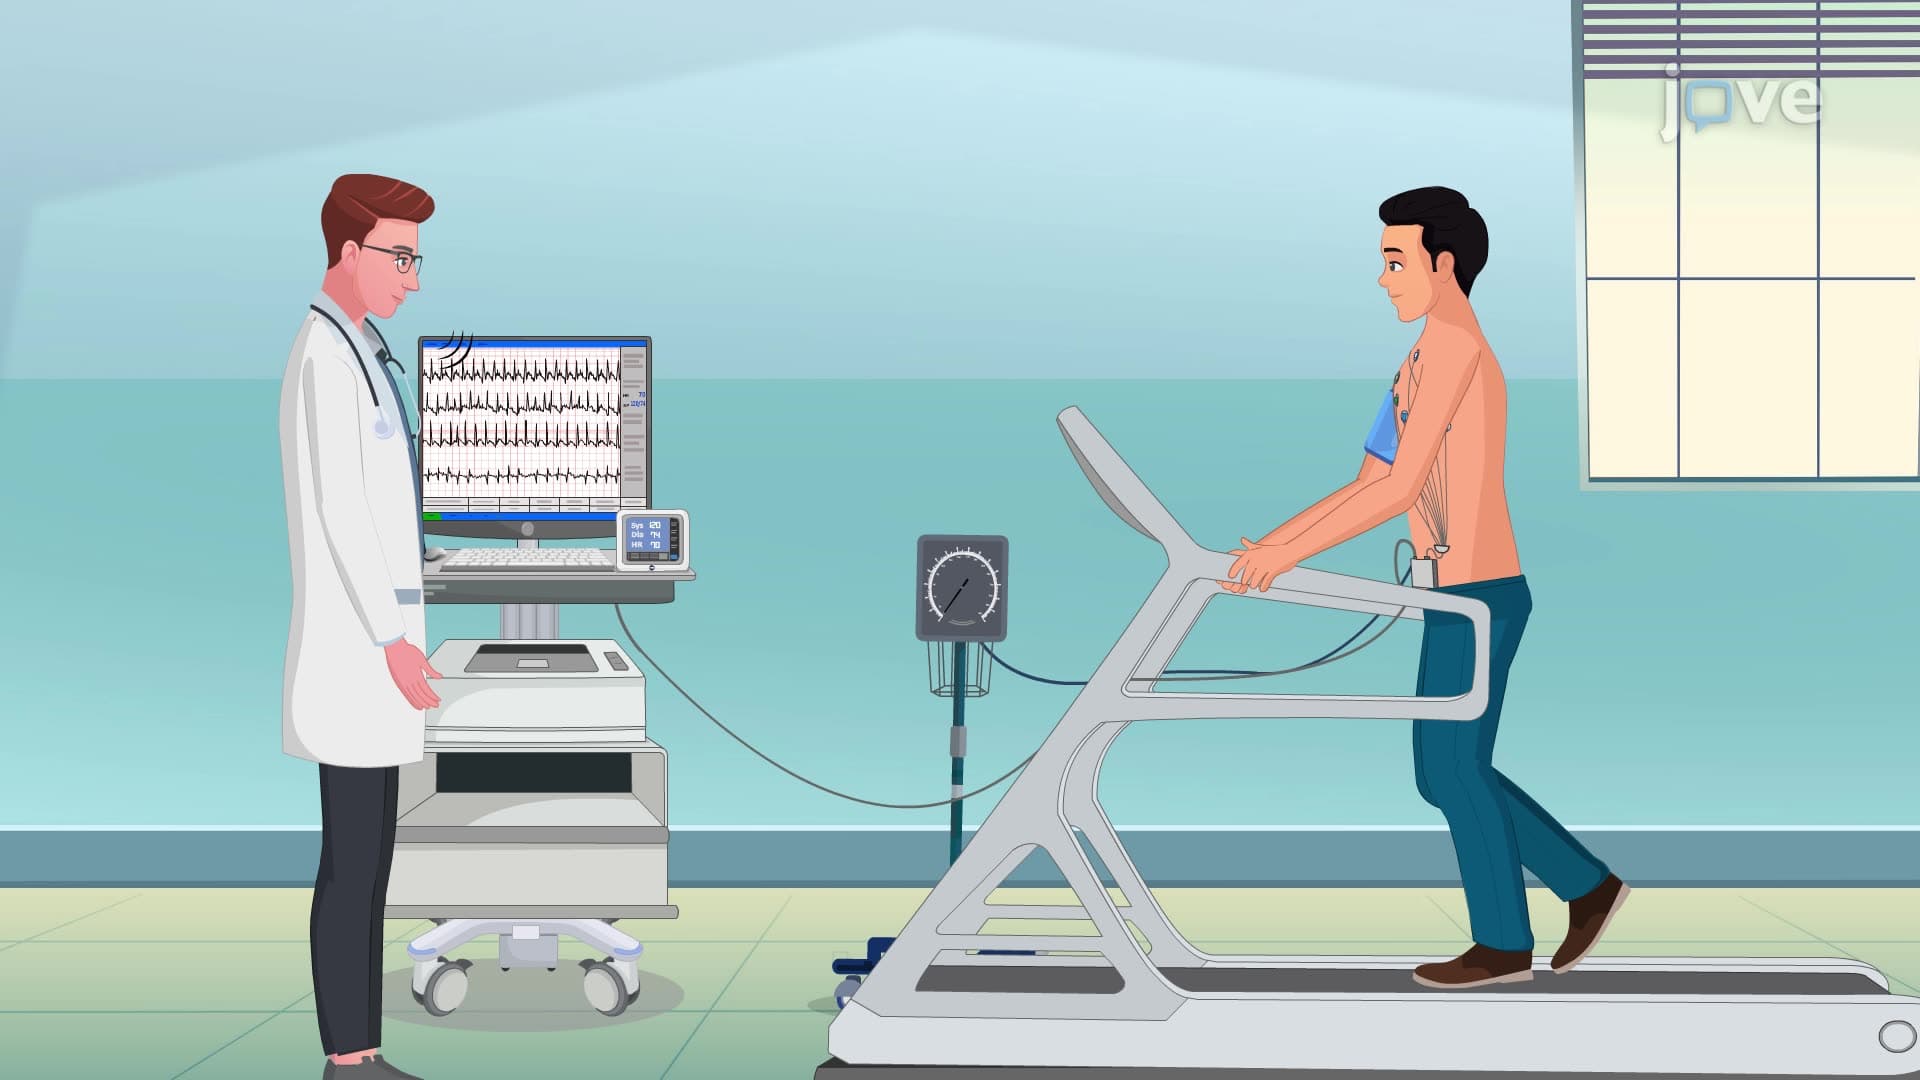
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure