

High prevalence of vertebral deformity in tumor-induced osteomalacia associated with impaired bone microstructure
1Department of Endocrinology, Key Laboratory of Endocrinology, National Commission of Health, State Key Laboratory of Complex Severe and Rare Diseases, Peking Union Medical College Hospital, Chinese Academy of Medical Sciences & Peking Union Medical College, Shuaifuyuan No. 1, Wangfujing Street, Dongcheng District, Beijing, 100730, China.

Purpose:
Patients with tumor-induced osteomalacia (TIO) often suffer from irreversible height loss due to vertebral deformity. However, the prevalence of vertebral deformity in TIO patients varies among limited studies. In addition, the distribution and type of vertebral deformity, as well as its risk factors, remain unknown. This study aimed to identify the prevalence, distribution, type and risk factors for vertebral deformity in a large cohort of TIO patients.
Methods:
A total of 164 TIO patients were enrolled in this retrospective study. Deformity in vertebrae T4-L4 by lateral thoracolumbar spine radiographs was evaluated according to the semiquantitative method of Genant. Bone microstructure was evaluated by trabecular bone score (TBS) and high-resolution peripheral QCT (HR-pQCT).
Results:
Ninety-nine (99/164, 60.4%) patients had 517 deformed vertebrae with a bimodal pattern of distribution (T7-9 and T11-L1), and biconcave deformity was the most common type (267/517, 51.6%). Compared with patients without vertebral deformity, those with vertebral deformity had a higher male/female ratio, longer disease duration, more height loss, lower serum phosphate, higher bone turnover markers, lower TBS, lower areal bone mineral density (aBMD), lower peripheral volumetric BMD (vBMD) and worse microstructure. Lower trabecular vBMD and worse trabecular microstructure in the peripheral bone and lower spine TBS were associated with an increased risk of vertebral deformity independently of aBMD. After adjusting for the number of deformed vertebrae, we found little difference in clinical indexes among the patients with different types of vertebral deformity. However, we found significant correlations of clinical indexes with the number of deformed vertebrae and the spinal deformity index.
Conclusion:
We reported a high prevalence of vertebral deformity in the largest cohort of TIO patients and described the vertebral deformity in detail for the first time. Risk factors for vertebral deformity included male sex, long disease duration, height loss, abnormal biochemical indexes and bone impairment. Clinical manifestation, biochemical indexes and bone impairment were correlated with the number of deformed vertebrae and degree of deformity, but not the type of deformity.

Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:55
Bone Structure
 01:31
Osteoclasts in Bone Remodeling
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:40
Bone Remodeling
 01:27
Compact Bone
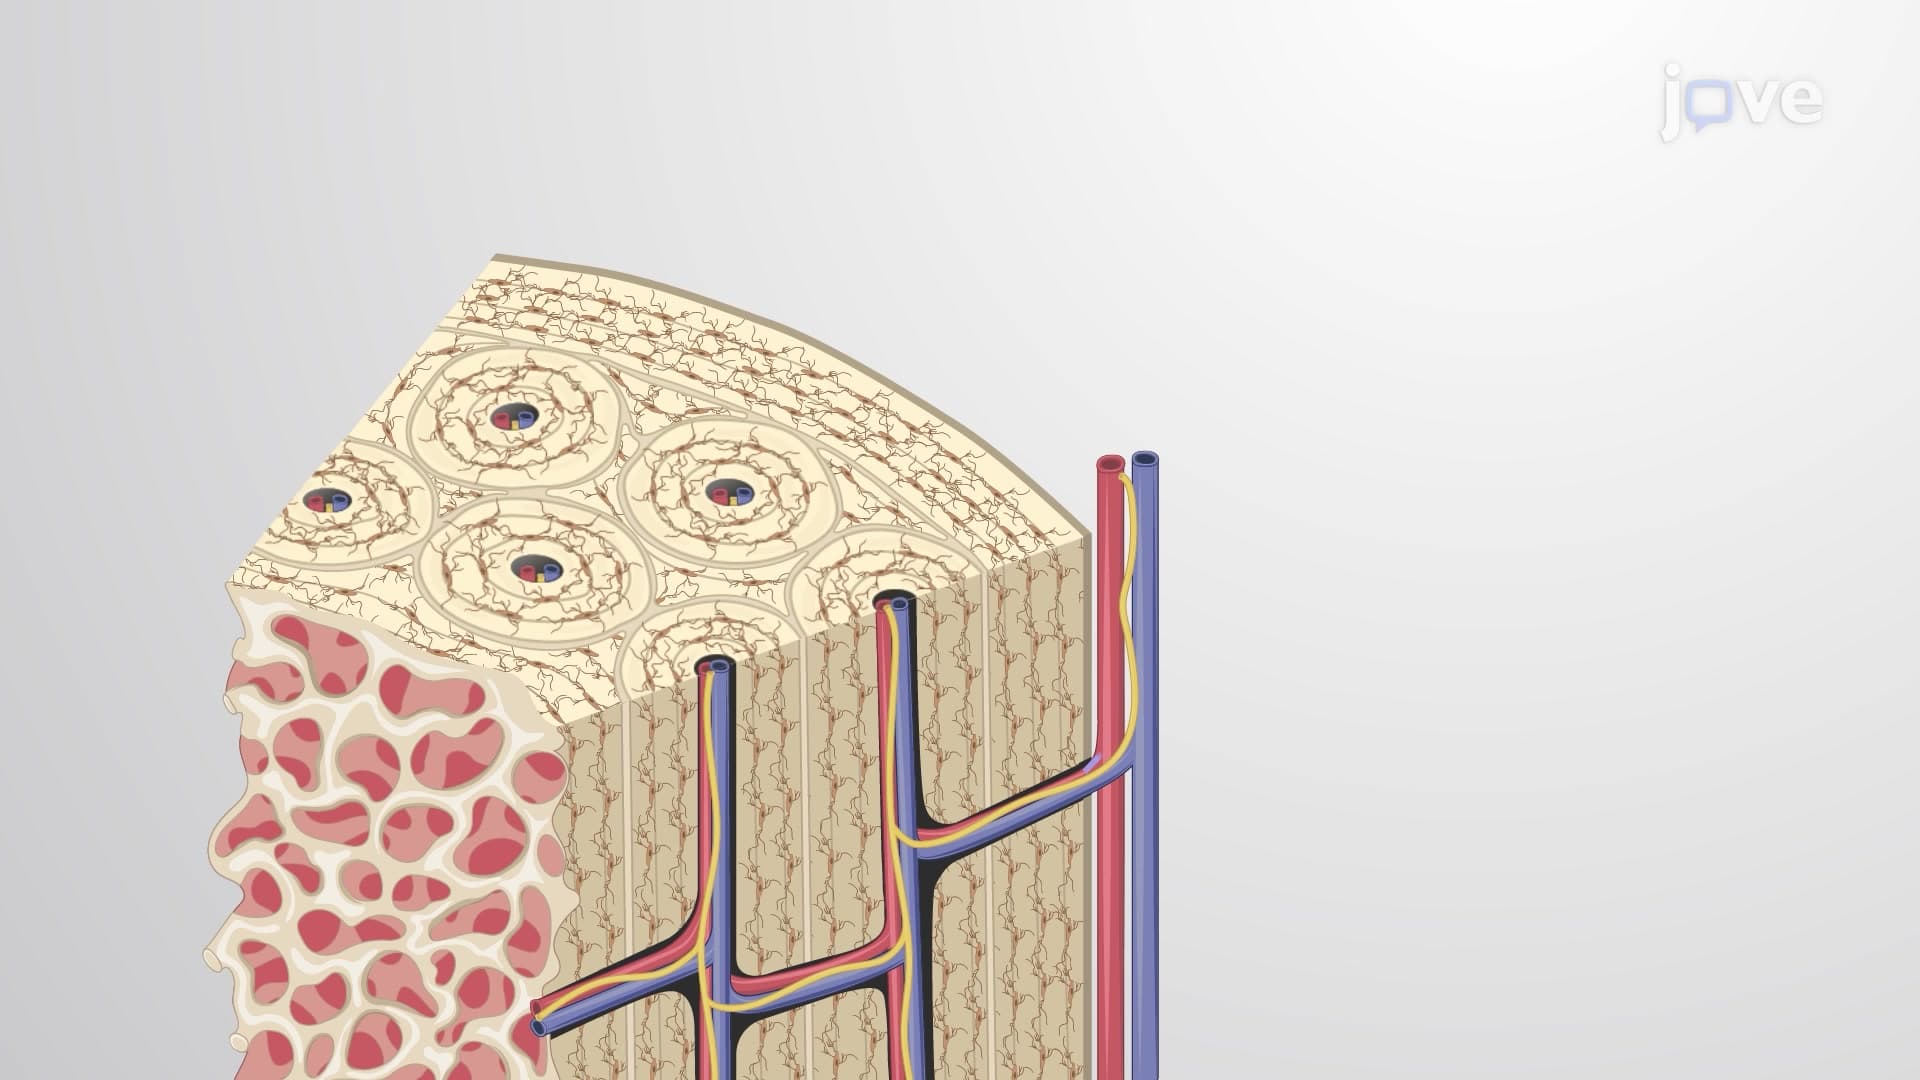
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...