Related Experiment Video
Updated: Aug 28, 2025
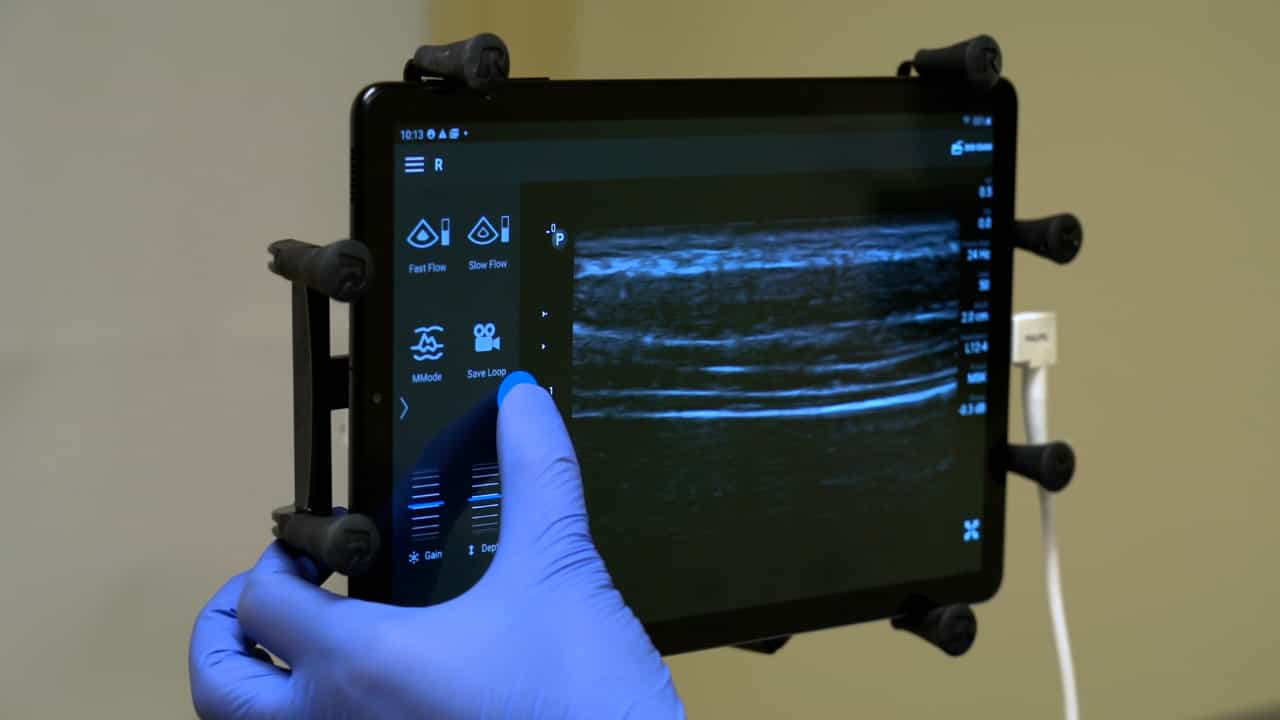

Author Spotlight: Unraveling the Impact of Mechanical Ventilation on Diaphragm Function and Patient Outcomes
Published on: November 3, 2023
[Effect of respiratory mechanics-guided sedation strategy on diaphragm function in mechanical ventilated patients
Zhen Liu1, Suqiu Meng2, Yang Wu1
1Department of Pulmonary Medicine, Huxi Hospital Affiliated to Jining Medical College (Shanxian Central Hospital), Heze 274300, Shandong, China.

Objective:
To investigate the effects of respiratory mechanics-guided sedation strategy on diaphragm function in chronic obstructive pulmonary disease (COPD) patients treated with mechanical ventilation (MV).
Methods:
A prospective study was conducted. Patients with acute exacerbation of chronic obstructive pulmonary disease (AECOPD) received invasive MV who were admitted to the Affiliated Huxi Hospital of Jining Medical University from May 2020 to May 2021 were enrolled. The patients were divided into observational group and control group by random number table method. All patients were intubated for MV, and received bronchodilators, glucocorticoid, anti-infectives, expectorant, nutritional support, analgesia and sedation. The sedatives were dexmedetomidine combined with propofol, and the analgesics were sufentanil in both groups. Respiratory mechanics monitoring was performed every 6 hours in the observational group, and the depth of sedation was adjusted according to the parameters of respiratory mechanics: when airway resistance (Raw) > 20 cmH2O×L-1×s-1, deep sedation was given to maintain Richmond agitation-sedation scale (RASS) ≤ -3; when the Raw was 10-20 cmH2O×L-1×s-1, the initial depth of sedation maintained to reach the RASS score of -2-0; when Raw < 10 cmH2O×L-1×s-1, withdrawn the sedation, or given light sedation, and maintained the RASS score of -2-0. While the control group received light sedation. The patients' diaphragmatic excursions (DE) was measured by bedside ultrasound, tidal volume (VT) and respiratory rate (RR) were recorded, and the diaphragmatic rapid shallow breathing index (D-RSBI, D-RSBI = RR/DE) and diaphragmatic excursion efficiency (DEE, DEE = VT/DE) were calculated. The differences in DE, D-RSBI, and DEE before and 3 days and 5 days of treatment between the two groups were compared. The difference in the RASS score within 3 days of sedation between the two groups was compared. The differences in the duration of MV and 28-day mortality between the two groups were compared.
Results:
A total of 96 patients were selected. Six patients were excluded due to delirium or the duration of MV shorter than 3 days. Finally, 90 patients were enrolled, with 46 in the observational group, and 44 in the control group. There were no statistically significant differences in DE, D-RSBI or DEE before treatment between the two groups. After treatment, D-RSBI in both groups was gradually decreased, and DEE was gradually increased with time. The D-RSBI at 3 days and 5 days of treatment in the observational group were significantly lower than those in the control group (times×min-1×mm-1: 1.73±0.48 vs. 1.96±0.35 at 3 days, 1.45±0.64 vs. 1.72±0.40 at 5 days, both P < 0.05), and DEE were significantly higher than those in the control group (mL/mm: 19.7±4.3 vs. 17.1±3.9 at 3 days, 25.8±5.6 vs. 22.9±5.4 at 5 days, both P < 0.05). There was no significant difference in DE at all time points between the two groups. The RASS scores within 2 hours of sedation in the observational group were significantly lower than those in the control group (1 day: -3.78±0.92 vs. -2.34±0.68, 2 days: -2.87±1.04 vs. -2.43±0.79, both P < 0.05), while no statistical difference at 3 days was found between the two groups. The duration of MV in the observational group was significantly shorter than that in the control group (days: 5.78±2.01 vs. 6.84±2.27, P < 0.05). One patient died in each of the control group and the observational group, and there was no significant difference in the 28-day mortality between the two groups (2.3% vs. 2.2%, P > 0.05).
Conclusions:
For AECOPD patients undergoing MV, respiratory mechanics-guided sedation strategy can reduce D-RSBI, increase DEE, shorten the duration of MV, and have a certain protective effect on the diaphragm.
More Related Videos

Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:30
Acute Respiratory Failure-III
 01:23
Acute Respiratory Failure-IV
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...