Related Experiment Video
Updated: Aug 28, 2025


Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Spinopelvic Adaptations in Standing and Sitting Positions in Patients With Adult Spinal Deformity
Rami El Rachkidi1,2, Abir Massaad2, Eddy Saad2
1Department of Orthopedics and Traumatology, Hôtel-Dieu de France Hospital, Beirut, LBN.

Abstract:
Purpose To describe spinopelvic adaptations in the standing and sitting positions in patients with adult spinal deformity (ASD). Methods Ninety-five patients with ASD and 32 controls completed health-related quality of life (HRQOL) questionnaires: short form 36 (SF36), Oswestry Disability Index (ODI), and visual analog scale (VAS) for pain. They underwent biplanar radiography in both standing and sitting positions. Patients with ASD were divided into ASD-front (frontal deformity Cobb > 20°, n = 24), ASD-sag (sagittal vertical axis (SVA) > 50 mm, pelvic tilt (PT) > 25°, or pelvic incidence (PI)-lumbar lordosis (LL) > 10°, n = 40), and ASD-hyper thoracic kyphosis (TK >60°, n = 31) groups. Flexibility was defined as the difference (Δ) in radiographic parameters between the standing and sitting positions. The radiographic parameters were compared between the groups. Correlations between HRQOL scores were evaluated. Results All participants increased their SVA from standing to sitting (ΔSVA<0), except for patients with ASD-sag, who tended to decrease their SVA (78-62 mm) and maximize their pelvic retroversion (27-40° vs 10-34° in controls, p<0.001). They also showed reduced thoracic and lumbar flexibility (ΔLL = 3.4 vs 37.1°; ΔTK = -1.7 vs 9.4° in controls, p<0.001). ASD-hyperTK showed a decreased PT while sitting (28.9 vs 34.4° in controls, p<0.001); they tended to decrease their LL and TK but could not reach values for controls (ΔLL = 22.8 vs 37.1° and ΔTK = 5.2 vs 9.4°, p<0.001). The ASD-front had normal standing and sitting postures. ΔSVA and ΔLL were negatively correlated with the physical component scale (PCS of SF36) and ODI (r = -0.39 and r = -0.46, respectively). Conclusion Patients with ASD present with different spinopelvic postures and adaptations from standing to sitting positions, with those having sagittal malalignment most affected. In addition, changes in standing and sitting postures were related to HRQOL outcomes. Therefore, surgeons should consider patient sitting adaptations in surgical planning and spinal fusion. Future studies on ASD should evaluate whether physical therapy or spinal surgery can improve sitting posture and QOL, especially for those with high SVA or PT.
More Related Videos
 08:40
Quantifying Arms and Legs Contributions during Repetitive Electrically-Assisted Sit-To-Stand Exercise in Paraplegics: A Pilot Study
Published on: November 11, 2022
 06:28
Biomechanical Changes Related to Low Back Pain: An Innovative Tool for Movement Pattern Assessment and Treatment Evaluation in Rehabilitation
Published on: December 13, 2024
Related Concept Videos
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:16
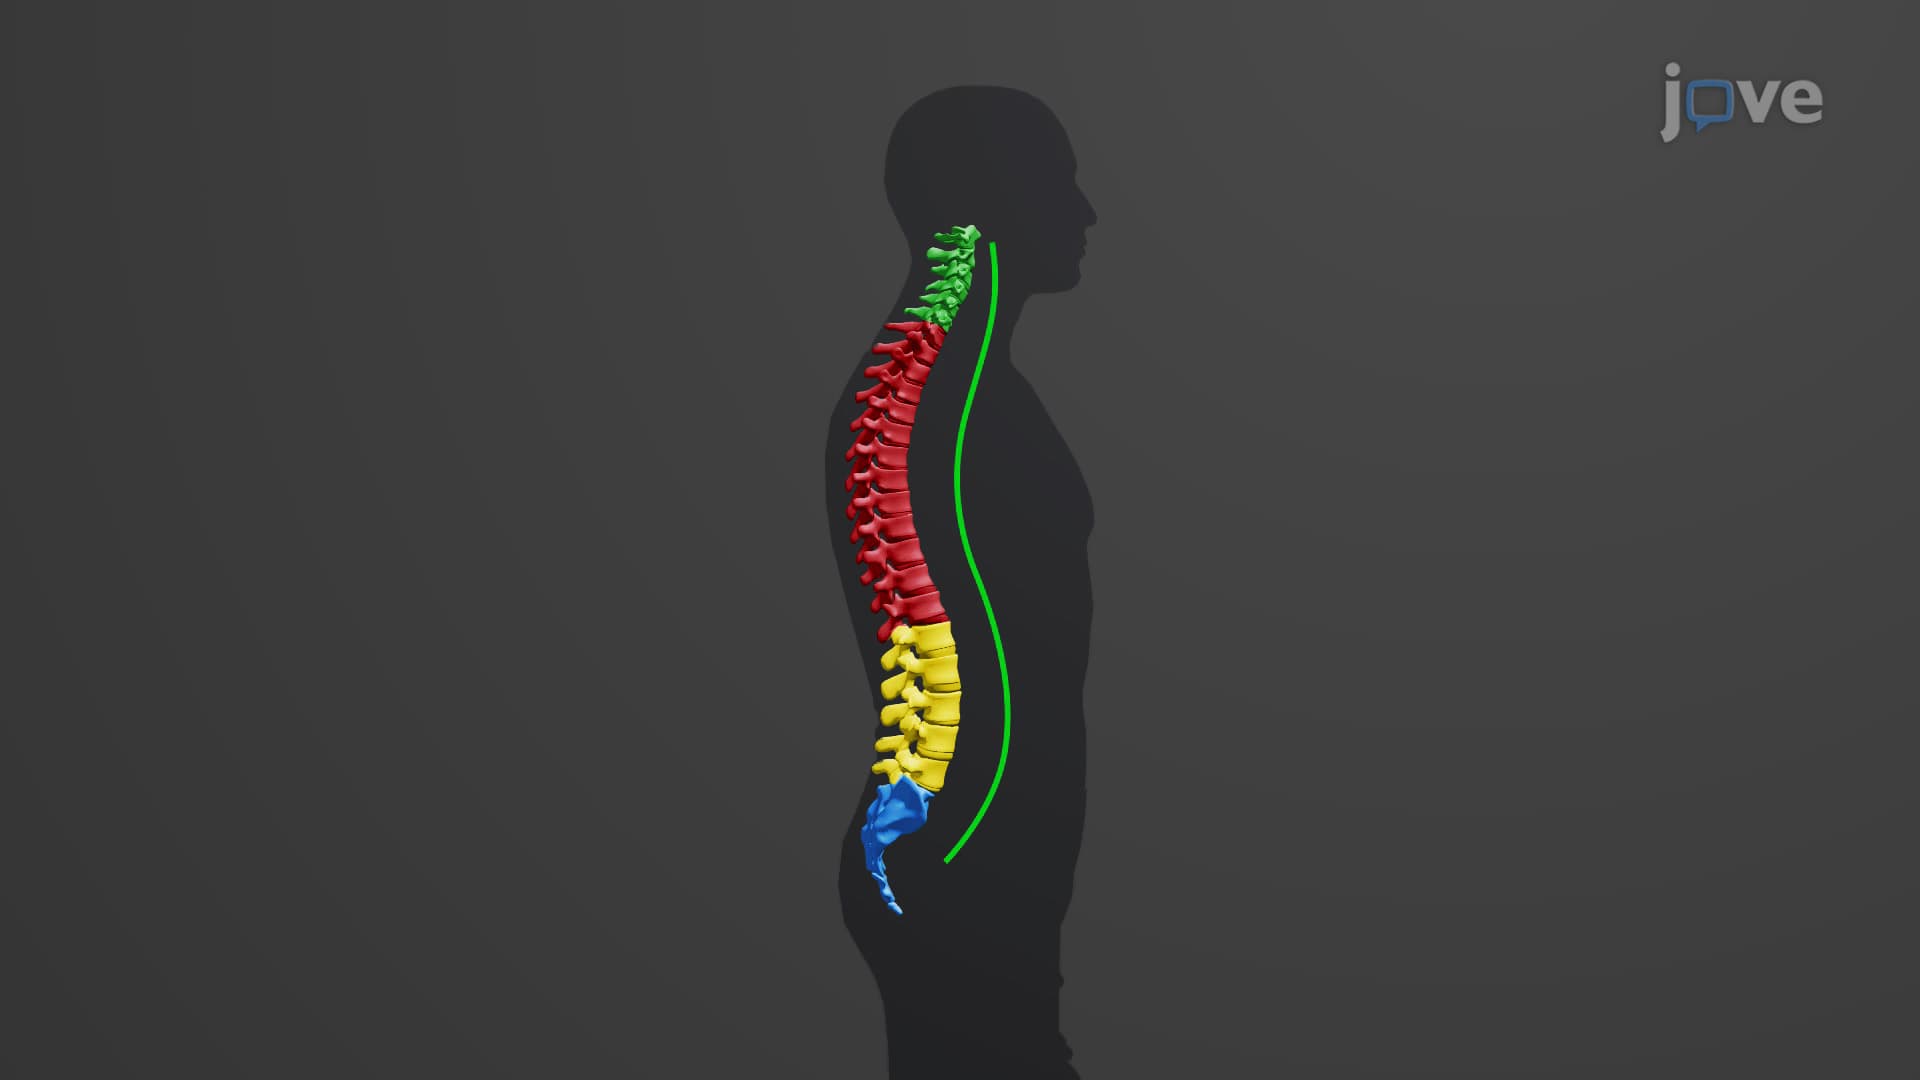
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...