Related Experiment Video
Updated: Aug 28, 2025

Non-fluoroscopic Catheter Tracking for Fluoroscopy Reduction in Interventional Electrophysiology
Published on: May 26, 2015
Coronary Arterial Spasm During Pulsed Field Ablation to Treat Atrial Fibrillation
Vivek Y Reddy1,2, Jan Petru1, Moritoshi Funasako1
1Homolka Hospital, Prague, Czech Republic (V.Y.R., J.P., M.F., K.K., P.H., M.C., M.J., S.K., P.N.).

Background:
Pulsed field ablation (PFA) has a unique safety profile when used to treat atrial fibrillation, largely related to its preferentiality for myocardial tissue ablation, in particular, esophageal sparing. A pentaspline catheter was the first such PFA system studied clinically for atrial fibrillation ablation; in these initial regulatory trials, the catheter was used for pulmonary vein isolation and left atrial posterior wall ablation. Since its regulatory approval in Europe, in clinical practice, physicians have ablated beyond pulmonary vein isolation and left atrial posterior wall ablation to expanded lesion sets in closer proximity to coronary arteries. This is an unstudied important issue because preclinical and clinical data have raised the potential for coronary arterial spasm. Herein, we studied the vasospastic potential of PFA lesion sets, both remote from and adjacent to coronary arteries.
Methods:
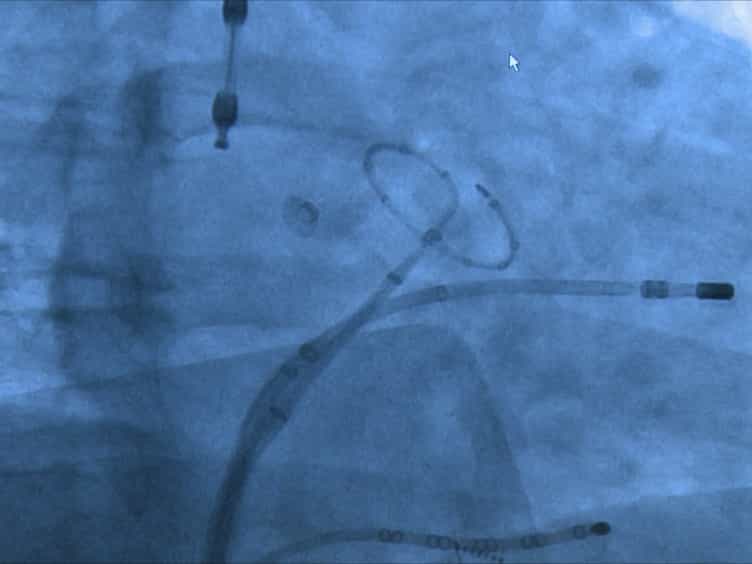
During routine atrial fibrillation ablation using the pentaspline PFA catheter, coronary angiography was performed before, during, and after pulsed field applications. The lesion sets studied included: (1) those remote from the coronary arteries such as pulmonary vein isolation (n=25 patients) and left atrial posterior wall ablation (n=5), and (2) ablation of the cavotricuspid isthmus (n=20) that is situated adjacent to the right coronary artery.
Results:
During pulmonary vein isolation and left atrial posterior wall ablation, coronary spasm did not occur, but cavotricuspid isthmus ablation provoked severe subtotal vasospasm in 5 of 5 (100%) consecutive patients, and this was relieved by intracoronary nitroglycerin in 5.5±3.5 minutes. ST-segment elevation was not observed. However, no patient (0%, P=0.004) had severe spasm if first administered parenteral nitroglycerin, either intracoronary (n=5) or intravenous (n=10), before treatment.
Conclusions:
Coronary vasospasm was not provoked during PFA at locations remote from coronary arteries, but when the energy is delivered adjacent to a coronary artery, PFA routinely provokes subclinical vasospasm. This phenomenon is attenuated by nitroglycerin, administered either post hoc to treat spasm or as prophylaxis.

Related Concept Videos
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:16
Vascular Spasm
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias