Related Experiment Video
Updated: Aug 27, 2025

Transaxillary First Rib Resection for Treatment of the Thoracic Outlet Syndrome
Published on: September 13, 2020
When Healing Hands Hurt: Epidemiology of Thoracic Outlet Syndrome Among Physicians
Stephanie D Talutis1, Hugh A Gelabert1, Jessica O'Connell1
1Division of Vascular & Endovascular Surgery, David Geffen School of Medicine at UCLA, Ronald Reagan Medical Center, University of California Los Angeles, Los Angeles, California.

Background:
Thoracic outlet syndrome (TOS) is an infrequent condition which results in disability in use of upper extremity. While TOS is often associated with manual labor, industrial workers, and accidents, it has not been reported in a physician (MD) population. Given the investment of time and effort in training to become a MD, the impact of TOS may be devastating. Our objective is to report the presentation and outcome of TOS in MDs.
Methods:
A prospectively surgical database was reviewed for MDs who sought care of disabling TOS between 1997 and 2022. Demographic, clinical, outcome and pathological data were reviewed. Outcomes were assessed based on Somatic Pain Scale (SPS), Quick Disabilities of Arm, Shoulder and Hand (DASH) scores, and Derkash scores. Results were also assessed based on return to employment.
Results:
A total of 19 MDs were identified, from 1,687 TOS cases. The group included 13 (63%) men, 6 (31%) women, average age 45 years (range 27-57). Presentations included 1 (5.3%) arterial TOS (ATOS), 9 (47.4%) venous TOS (VTOS), and 9 (47.4) neurogenic TOS (NTOS). All patients were right-handed, and symptomatic side was dominant hand in 7 (37%) patients. Etiologies included repetitive motion injury, athletic injury, and congenital bony abnormalities. Repetitive motion was associated with 3/9 (33%) NTOS. Significant athletic activities were noted in 12 of 19 (63%) MDs, including 8/9 (89%) VTOS and 4/9 (44%) NTOS. Athletic activities associated with VTOS included triathletes (2), rock climbing (1), long distance swimming (2), and weightlifting (3). Of the 9 NTOS cases, 3 were associated with weightlifting and 1 with skiing. Congenital causes included 1 (5%) abnormal first rib and 1 (5%) cervical rib. Time from symptom onset to consultation varied significantly according to diagnosis: ATOS 6 days, VTOS 97 days, and NTOS 2,335 days (P < 0.05). All underwent first rib resection (FRR), and 4 (4) patients required contralateral FRR. Time from surgery to last follow-up averaged 1,005 days (range: 37-4,535 days). On presentation, 6 patients were work disabled and 13 patients were work restricted. Following surgery, 4 MDs remained work restricted with mild to moderate symptoms. After surgery, standardized outcomes (SPS, Quick DASH, and Derkash score) improved in all metrics. All who were initially disabled returned to work without restriction. Significant non-TOS related comorbidities were present in all who had residual restriction. Return to work was documented in all.
Conclusions:
Although it has not been reported, MDs are subject to developing TOS. Causes include repetitive motions, athletic injuries, and congenital bony abnormalities. Surgical decompression is beneficial with significant reduction in pain and disability. MDs are highly motivated and insightful; accordingly, they have a very high probability of successful work resumption, with all returning to their medical positions.
Related Concept Videos
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:24
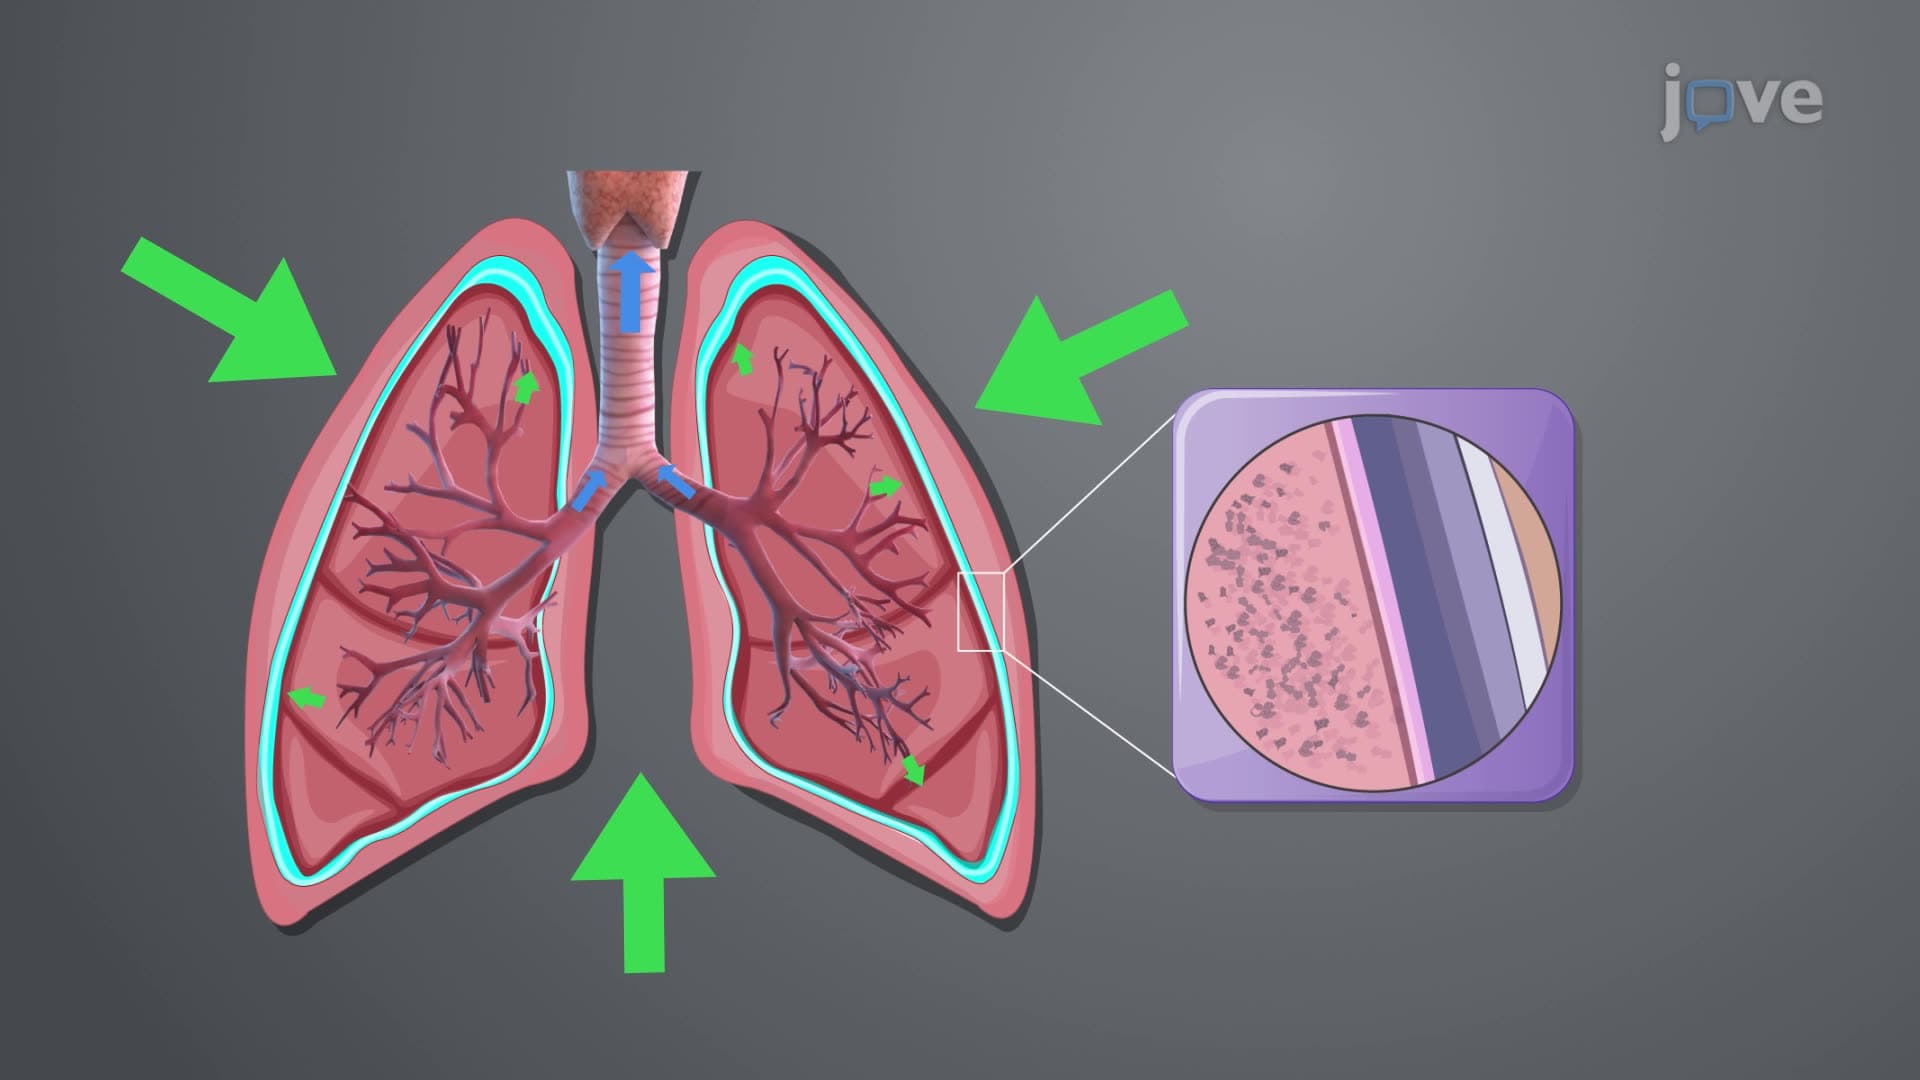
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies