Related Experiment Video
Updated: Aug 27, 2025
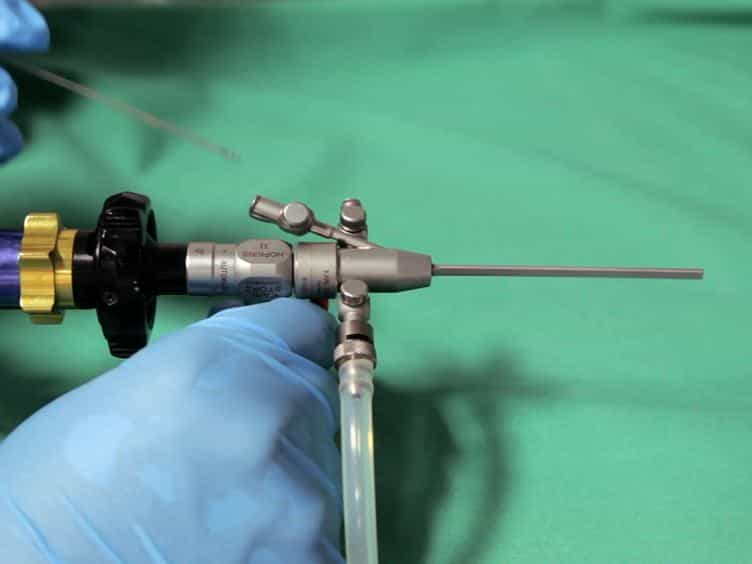
Murine Endoscopy for In Vivo Multimodal Imaging of Carcinogenesis and Assessment of Intestinal Wound Healing and Inflammation
Published on: August 26, 2014
Ulcer Size After Induction Therapy Performs Better Than Symptom Assessment for Prediction of One Year Endoscopic
Cara Pray1, Emily C L Wong1, Achuthan Aruljothy1
1Department of Medicine, Division of Gastroenterology, and Farncombe Family Digestive Health Research Institute, McMaster University, Hamilton, ON, Canada.

Background:
We evaluated whether postinduction ulcer size and patient-reported outcome (PRO) severity are associated with the achievement of 1-year endoscopic remission (ER) in patients with Crohn's disease (CD).
Methods:
This post hoc analysis combined data from several clinical trials including 283 patients with baseline ulcers ≥5 mm with repeat endoscopy after ustekinumab or adalimumab induction therapy. Patient-reported outcomes including stool frequency (SF) and abdominal pain (AP) were measured by the Crohn's Disease Activity Index. Thresholds of SF ≥4 and/or AP ≥2 indicated moderately to severely active CD. Endoscopic remission was defined as Simple Endoscopic Score for CD (SES-CD) <3. Multivariate logistic regression models adjusted for confounders (including disease duration and treatment allocation) evaluated the relationships between postinduction ulcer size, PRO symptoms, and achievement of 1-year ER.
Results:
Among the 131 CD patients who continued to have ulcers ≥5 mm after induction therapy, 48 (36.6%) achieved 1-year ER. Patients with postinduction ulcers ≥5 mm were approximately 5 times less likely to achieve 1-year ER than the 152 individuals who had small or no postinduction ulcers (odds ratio [OR], 0.20; 95% CI, 0.08-0.51, P = .001). In patients with ulcers ≥5 mm after induction, postinduction PRO scores (including PRO2 and PRO3) did not predict 1-year ER.
Conclusions:
Crohn's disease patients with ulcers ≥5 mm after induction therapy are less likely to achieve 1-year ER. Postinduction PRO severity does not offer additional prognostic information. This may suggest that objective measures of disease such as endoscopic ulcer size should be considered over symptom assessments for determining clinical response to therapy and utilized in trials for maintenance therapy.
More Related Videos
 09:01
Non-invasive Assessment of the Efficacy of New Therapeutics for Intestinal Pathologies Using Serial Endoscopic Imaging of Live Mice
Published on: March 10, 2015
 09:50
Induction of Intestinal Graft-versus-host Disease and Its Mini-endoscopic Assessment in Live Mice
Published on: February 11, 2019
Related Concept Videos
 01:21
Drugs for Treatment of Crohn's Disease in IBD Using Glucocorticoids
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:29
Drugs for Treatment of Ulcerative Colitis in IBD