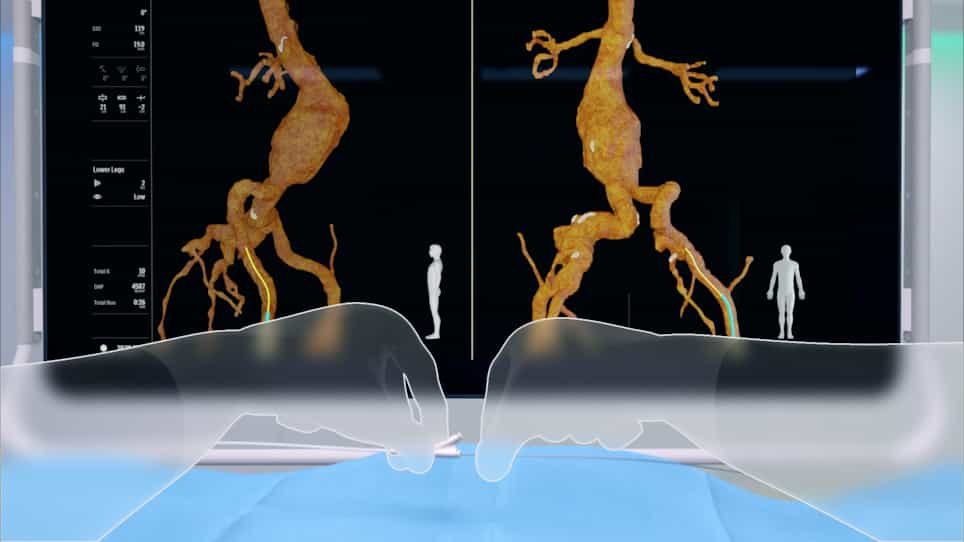
Incidence of venous thromboembolism in patients with peripheral arterial disease after endovascular intervention
Daniel G Kindell1, Kathleen Marulanda1, Deanna M Caruso2
1Department of Surgery, University of North Carolina at Chapel Hill, Chapel Hill, NC.

Objective:
Venous thromboembolism (VTE) is a well-known postoperative complication; however, the incidence of VTE after peripheral vascular intervention (PVI) has not been well described. Despite the minimally invasive nature of these procedures, the patients undergoing PVI have significant risk factors for the development of VTE. In the present study, our objective was to describe the short-term incidence of VTE after PVI, identify differences between sexes, and examine the periprocedural antiplatelet and anticoagulation regimens.
Methods:
We identified adults (age >66 years) who had undergone PVI from January 1, 2008 to September 30, 2015 from the inpatient Medicare claims data. The patients were followed for 365 days after the procedure. VTE events during follow-up were identified using the International Classification of Diseases, 9th revision, diagnosis codes. The covariate-standardized 30- and 90-day cumulative incidence of VTE events, overall and stratified by sex, were estimated using Aalen-Johansen estimators, accounting for death as a competing risk. Differences in sex between females and males were identified using Gray's test. Any antiplatelet or anticoagulant prescription fill was defined as any fill from 14 days before the endovascular intervention through the date of the VTE event. Persistence with antiplatelet and anticoagulant therapy was assessed by creating daily logs of antiplatelet and anticoagulant coverage using the dispensing dates and days of supply. Over-the-counter medications (ie, aspirin) were not evaluated.
Results:
We identified 31,593 qualifying patients with a mean age of 76.8 ± 7.4 years. Of the 31,593 patients, 46% were male, and 12% had a history of VTE. After the procedure, deep vein thrombosis (DVT) was a commonly diagnosed complication (3.8% and 4.8% at 30 and 90 days, respectively). The cumulative incidence of pulmonary embolism was 0.9% and 1.2% at 30 and 90 days after the procedure, respectively. Throughout the 90-day postoperative period, females had had a slightly increased risk of DVT compared with males (30-day risk difference, 0.007; P < .01; 90-day risk difference, 0.008; P = .02). We found no sex-based differences in the risk of pulmonary embolism. Of the patients who had developed VTE at 90 days, 970 (55%) had had no prescription fill for an antiplatelet or anticoagulant. Assuming all the patients had been taking aspirin, only 15% of the patients who had developed VTE had been taking prescribed dual antiplatelet medication persistently after PVI. In addition, among the patients who had developed VTE at 90 days, females were less likely to have had a prescription fill for an anticoagulant.
Conclusions:
The findings from our study have demonstrated that the incidence of VTE after PVI is high, with an increased risk of deep vein thrombosis for females. We also found that females were less likely to have been prescribed an anticoagulant after PVI. Future studies are needed to characterize the variables associated with an increased risk of VTE after PVI and to identify strategies to increase dual antiplatelet therapy or anticoagulant prescription adherence to reduce the risk of VTE.
More Related Videos
 08:05
Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
 07:02
A Rabbit Venous Interposition Model Mimicking Revascularization Surgery using Vein Grafts to Assess Intimal Hyperplasia under Arterial Blood Pressure
Published on: May 15, 2020
Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:30
Venous Thrombosis I: Introduction
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:27
Pulmonary Embolism III: Nursing Management