Related Experiment Video
Updated: Aug 26, 2025


Author Spotlight: Establishing a New Fluorescence-Based Protocol for In Vivo Mitochondrial Morphology Analysis in Parkinson's Disease
Published on: June 23, 2023
Morphologic and Molecular Patterns of Polymyositis With Mitochondrial Pathology and Inclusion Body Myositis
Felix Kleefeld1, Akinori Uruha1, Anne Schänzer1
1From the Department of Neurology (F.K., W.S., K.H.), Charité-Universitätsmedizin Berlin, Corporate Member of Freie Universität Berlin and Humboldt-Universität zu Berlin, Germany; Department of Neurology (A.U.), Tokyo Metropolitan Neurological Hospital, Japan; Institute of Neuropathology (A.S., A.N.), Justus Liebig University, Giessen, Germany; Pediatric Neurology (A.R.), University Children's Hospital, University of Duisburg-Essen, Faculty of Medicine, Germany, and Department of Neurology, Heimer Institute for Muscle Research, University Hospital Bergmannsheil, Ruhr-University Bochum, Germany; Departments of Rheumatology (U.S.) and Neuropathology (H.H.G.), Charité-Universitätsmedizin Berlin, Corporate Member of Freie Universität Berlin and Humboldt-Universität zu Berlin, Germany; Department of Neuropathology (H.H.G.), University Medical Center, Mainz, Germany and Charité-Universitätsmedizin Berlin, Corporate Member of Freie Universität Berlin and Humboldt-Universität zu Berlin, Germany; Department of Neuropediatrics (M.S.), Charité-Universitätsmedizin Berlin, Corporate Member of Freie Universität Berlin and Humboldt-Universität zu Berlin, Germany; Cand Department of Neurology with Institute for Translational Neurology (C.P.), University Hospital Münster, Münster, Germany and Department of Neuropathology (C.P., W.S.), Charité-Universitätsmedizin Berlin, Corporate Member of Freie Universität Berlin and Humboldt-Universität zu Berlin, Germany.

Background And Objective:
To characterize morphological and molecular underpinnings of polymyositis with mitochondrial pathology (PM-Mito) in comparison with sporadic inclusion body myositis (IBM) and to define common and distinct pathophysiologic features with a focus on interferon (IFN)-associated inflammation and T-cell response.
Methods:
In this cross-sectional study, skeletal muscle biopsy samples and clinical and laboratory data from patients with PM-Mito and IBM were analyzed at Charité university hospital in Berlin, Germany. All available PM-Mito biopsy samples, an equal number of randomly selected IBM biopsy samples, and randomly selected nondiseased controls (NDCs) were included in the study. Biopsy samples were studied by histopathology, immunohistochemistry, and quantitative PCR (qPCR) and compared with biopsies derived from NDCs. Primary outcomes included cell counts for immunohistochemistry and gene expression (fold-change values compared with those in NDCs) for qPCR.
Results:
Twenty-five skeletal muscle biopsy samples of patients with PM-Mito and IBM were included in the study and compared with 5 biopsy samples from NDCs. PM-Mito and IBM qualitatively harbored a strikingly similar molecular signature and shared important histopathologic features. Expression of IFN-induced guanylate-binding protein (GBP)6 and T-cell function-related KLRG1 distinguished IBM from PM-Mito biopsies with IBM patients showing significantly higher expression of GBP6 and KLRG1. Cryptic exon expression was detected in both patient groups with IBM patients showing higher expression levels. Skeletal muscle biopsies from IBM patients showed significantly more GBP6+ cells and KLRG1+ lymphocytes in comparison with biopsies from patients with PM-Mito. CD45+, CD68+, CD57+, PD1+, and CD8+ cytotoxic T cells were also significantly more abundant in patients with IBM. Clinically, patients with PM-Mito presented with a spectrum of muscle-related symptoms including myalgia, proximal paraparesis, proximal tetraparesis, and incomplete IBM-like patterns. Thirteen of 14 (93%) patients with PM-Mito for whom clinical follow-up was available later developed clinically defined IBM. Notably, 2 follow-up biopsies obtained 5 and 7 years after the first ones were available in this cohort, both showing histopathologic progress to net IBM including GBP6 and KLRG1 upregulation.
Discussion:
Our combined data suggest that specific IFN-mediated inflammation plays a key role in both IBM and PM-Mito. GBP6 was identified as a new molecule of type II IFN-induced inflammation distinguishing IBM from PM-Mito. Skeletal muscles from both groups harbor dysfunctional T cells of similar type, albeit in different quantity. T-cell senescence exemplified by KLRG1 positivity does not play a significant role in PM-Mito. Based on these findings, we propose to include PM-Mito in the spectrum of IBM (IBM-spectrum disease [IBM-SD]) as a possible early form of this disease. The establishment of IBM-SD as a larger entity could potentially have a significant effect on the design of trials and therapeutic interventions.
Insights
Polymyositis with mitochondrial pathology (PM-Mito) shares molecular and histopathologic features with inclusion body myositis (IBM), suggesting PM-Mito may be an early form of IBM. Guanylate-binding protein 6 (GBP6) and KLRG1 expression differentiate the two conditions.
Area of Science:
- Neurology
- Immunology
- Pathology
Background:
- Polymyositis with mitochondrial pathology (PM-Mito) and sporadic inclusion body myositis (IBM) are inflammatory myopathies with distinct clinical presentations.
- Understanding their shared and distinct pathophysiologic features, particularly interferon (IFN)-mediated inflammation and T-cell responses, is crucial for diagnosis and treatment.
Purpose of the Study:
- To compare the morphological and molecular characteristics of PM-Mito and IBM.
- To identify common and distinct features focusing on IFN-associated inflammation and T-cell responses.
Main Methods:
- Analysis of skeletal muscle biopsy samples from patients with PM-Mito, IBM, and non-diseased controls (NDCs).
- Histopathology, immunohistochemistry, and quantitative PCR (qPCR) were employed to assess cellular and molecular differences.
- Gene expression analysis focused on IFN-induced proteins and T-cell markers.
Main Results:
- PM-Mito and IBM share similar molecular signatures and histopathologic features.
- Guanylate-binding protein 6 (GBP6) and KLRG1 expression were significantly higher in IBM, distinguishing it from PM-Mito.
- IBM showed increased numbers of various immune cells, including cytotoxic T cells, compared to PM-Mito.
- A majority of PM-Mito patients (93%) later developed clinically defined IBM, with follow-up biopsies showing progression.
Conclusions:
- Interferon-mediated inflammation is central to both IBM and PM-Mito.
- GBP6 is a novel marker distinguishing IBM from PM-Mito.
- While T-cell populations differ in quantity, they are similarly dysfunctional in both conditions.
- PM-Mito is proposed to be part of the inclusion body myositis spectrum disease (IBM-SD), potentially representing an early stage.

Related Concept Videos
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:28
The Inner Mitochondrial Membrane
 01:21
Myocarditis I: Introduction
 01:19
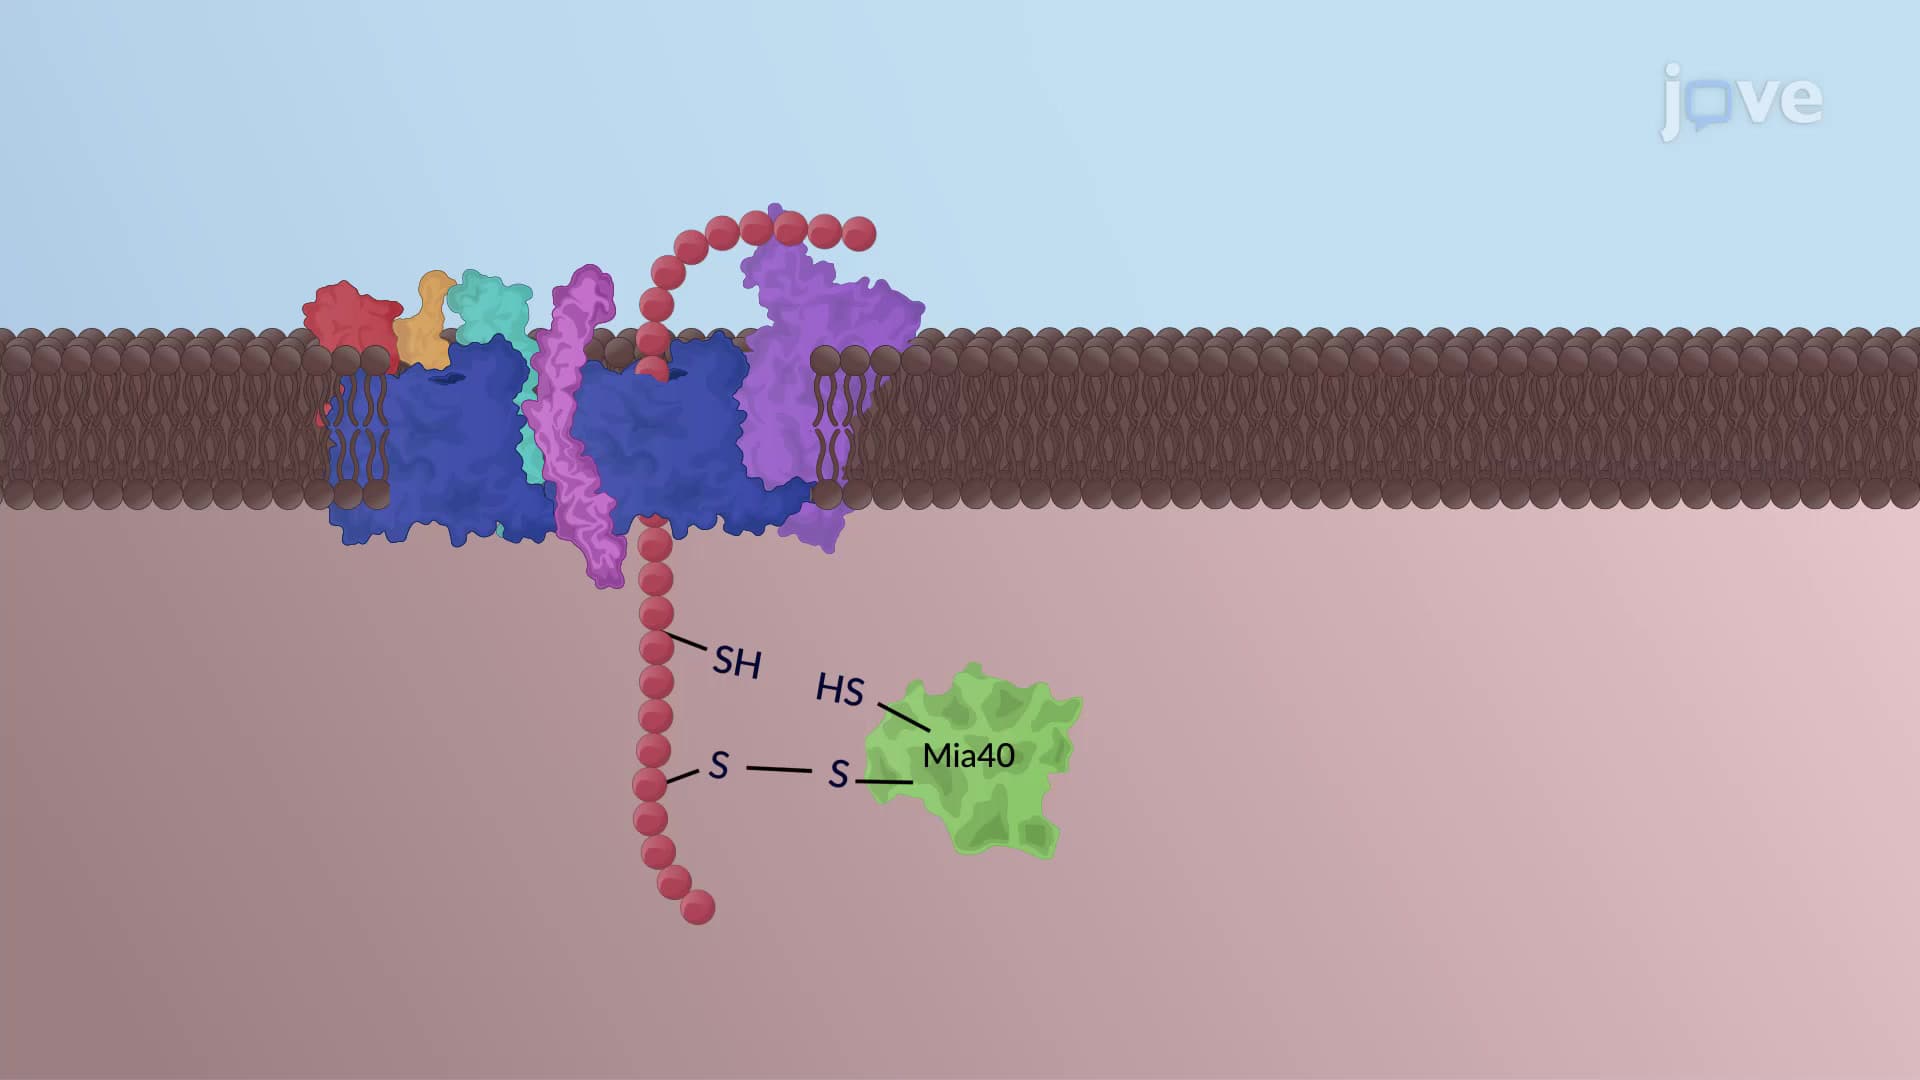
Translocation of Proteins into the Mitochondria
Sorting of outer membrane proteins:
Mitochondrial outer membrane proteins are of two types: the transmembrane, beta-barrel porins, and the membrane-anchored, alpha-helical proteins. Beta-barrel porin precursors are translocated by the TOM complex and inserted into the outer mitochondrial membrane by the SAM complex. In contrast,...