Related Experiment Video
Updated: Aug 26, 2025


Digital Home-Monitoring of Patients after Kidney Transplantation: The MACCS Platform
Published on: April 12, 2021
Response and Dynamics of Renal Function in Transplantation-Eligible Multiple Myeloma Patients Treated with a Novel
Yaeni Kim1, Sung-Soo Park2, Young-Woo Jeon3
1Department of Nephrology, Seoul St. Mary's Hospital, College of Medicine, The Catholic University of Korea, Seoul, Republic of Korea.

Newly diagnosed multiple myeloma (NDMM) frequently results in renal impairment (RI), and its natural course has not been fully elucidated in the era of novel agents. We aimed to identify the dynamics of renal function after autologous stem cell transplantation (ASCT) following induction treatment using a novel agent in transplantation-eligible NDMM patients with RI (estimated glomerular filtration rate [eGFR] ≤50 mL/min/1.73 m2) at diagnosis. The factors associated with achieving a renal response based on the term renal benefit regardless of baseline eGFR were investigated as well. In a multicenter registry database including 1795 patients with plasma cell disorder, 140 transplantation-eligible NDMM patients who developed RI at the time of initiation of treatment for NDMM were identified. They received protocol-based treatment (PBT) consisting of induction treatment using proteasome inhibitors and/or immunomodulatory drugs followed by ASCT. MM and renal responses were evaluated using the International Myeloma Working Group response criteria. To evaluate the standardized improvement of renal function irrespective of baseline eGFR, renal benefit was defined as a sustained (for at least 3 months) increase in eGFR >15 mL/min/1.73 m2. The mean patient age was 54.7 ± 7.4 years. With a mean baseline eGFR of 24.8 ± 13.9, the renal complete response (renalCR) and renal benefit rates were 49.3% and 67.9%, respectively. In a multivariable analysis, the 3 factors significantly associated with reduced likelihood of achieving both renalCR and renal benefit were age ≥55 years, light chain type NDMM, and failure to improve eGFR by 5 mL/min/1.73 m2 with supportive care when measured 3 days prior to induction therapy and at the initiation of chemotherapy. Hypertension and advanced eGFR also were associated with poor renalCR achievement. The mean eGFR improved until the time of ASCT and then decreased gradually over time. The mean eGFR improved significantly until 4 months post-PBT compared with each eGFR at previous time points, but this significant improvement disappeared by 5 months post-PBT. In a subgroup of patients who developed RI after undergoing ASCT (n = 55), the eGFR increased temporarily at 1 month post-ASCT; however, this improvement reverted to baseline at 2 months post-ASCT. Among another subgroup of 27 patients who were dialysis-dependent at the time of initial treatment, 18 (66.7%) were no longer dialysis-dependent after a median of 60 days. The best renal response was acquired early during the PBT period, and ASCT did not have a robust impact on the renal outcome. Patients who failed to achieve a renal benefit should be provided with the best supportive care for chronic kidney disease, and this simplified criterion for evaluating the renal response needs to be validated in larger studies before it can be recommended. © 2022 American Society for Transplantation and Cellular Therapy. Published by Elsevier Inc.
Newly diagnosed multiple myeloma (NDMM) frequently results in renal impairment (RI), and its natural course has not been fully elucidated in the era of novel agents. We aimed to identify the dynamics of renal function after autologous stem cell transplantation (ASCT) following induction treatment using a novel agent in transplantation-eligible NDMM patients with RI (estimated glomerular filtration rate [eGFR] ≤50 mL/min/1.73 m2) at diagnosis. The factors associated with achieving a renal response based on the term renal benefit regardless of baseline eGFR were investigated as well. In a multicenter registry database including 1795 patients with plasma cell disorder, 140 transplantation-eligible NDMM patients who developed RI at the time of initiation of treatment for NDMM were identified. They received protocol-based treatment (PBT) consisting of induction treatment using proteasome inhibitors and/or immunomodulatory drugs followed by ASCT. MM and renal responses were evaluated using the International Myeloma Working Group response criteria. To evaluate the standardized improvement of renal function irrespective of baseline eGFR, renal benefit was defined as a sustained (for at least 3 months) increase in eGFR >15 mL/min/1.73 m2. The mean patient age was 54.7 ± 7.4 years. With a mean baseline eGFR of 24.8 ± 13.9, the renal complete response (renalCR) and renal benefit rates were 49.3% and 67.9%, respectively. In a multivariable analysis, the 3 factors significantly associated with reduced likelihood of achieving both renalCR and renal benefit were age ≥55 years, light chain type NDMM, and failure to improve eGFR by 5 mL/min/1.73 m2 with supportive care when measured 3 days prior to induction therapy and at the initiation of chemotherapy. Hypertension and advanced eGFR also were associated with poor renalCR achievement. The mean eGFR improved until the time of ASCT and then decreased gradually over time. The mean eGFR improved significantly until 4 months post-PBT compared with each eGFR at previous time points, but this significant improvement disappeared by 5 months post-PBT. In a subgroup of patients who developed RI after undergoing ASCT (n = 55), the eGFR increased temporarily at 1 month post-ASCT; however, this improvement reverted to baseline at 2 months post-ASCT. Among another subgroup of 27 patients who were dialysis-dependent at the time of initial treatment, 18 (66.7%) were no longer dialysis-dependent after a median of 60 days. The best renal response was acquired early during the PBT period, and ASCT did not have a robust impact on the renal outcome. Patients who failed to achieve a renal benefit should be provided with the best supportive care for chronic kidney disease, and this simplified criterion for evaluating the renal response needs to be validated in larger studies before it can be recommended. © 2022 American Society for Transplantation and Cellular Therapy. Published by Elsevier Inc.
More Related Videos
 09:41
An Organotypic High Throughput System for Characterization of Drug Sensitivity of Primary Multiple Myeloma Cells
Published on: July 15, 2015
 06:38
A Syngeneic Mouse Model of Metastatic Renal Cell Carcinoma for Quantitative and Longitudinal Assessment of Preclinical Therapies
Published on: April 12, 2017
Related Concept Videos
 01:16
Kidney Transplant III: Nursing Management
 01:30
Continuous Renal Replacement Therapy
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:28
Kidney Transplant I: Introduction
 01:06
Renal Drug Clearance: Overview
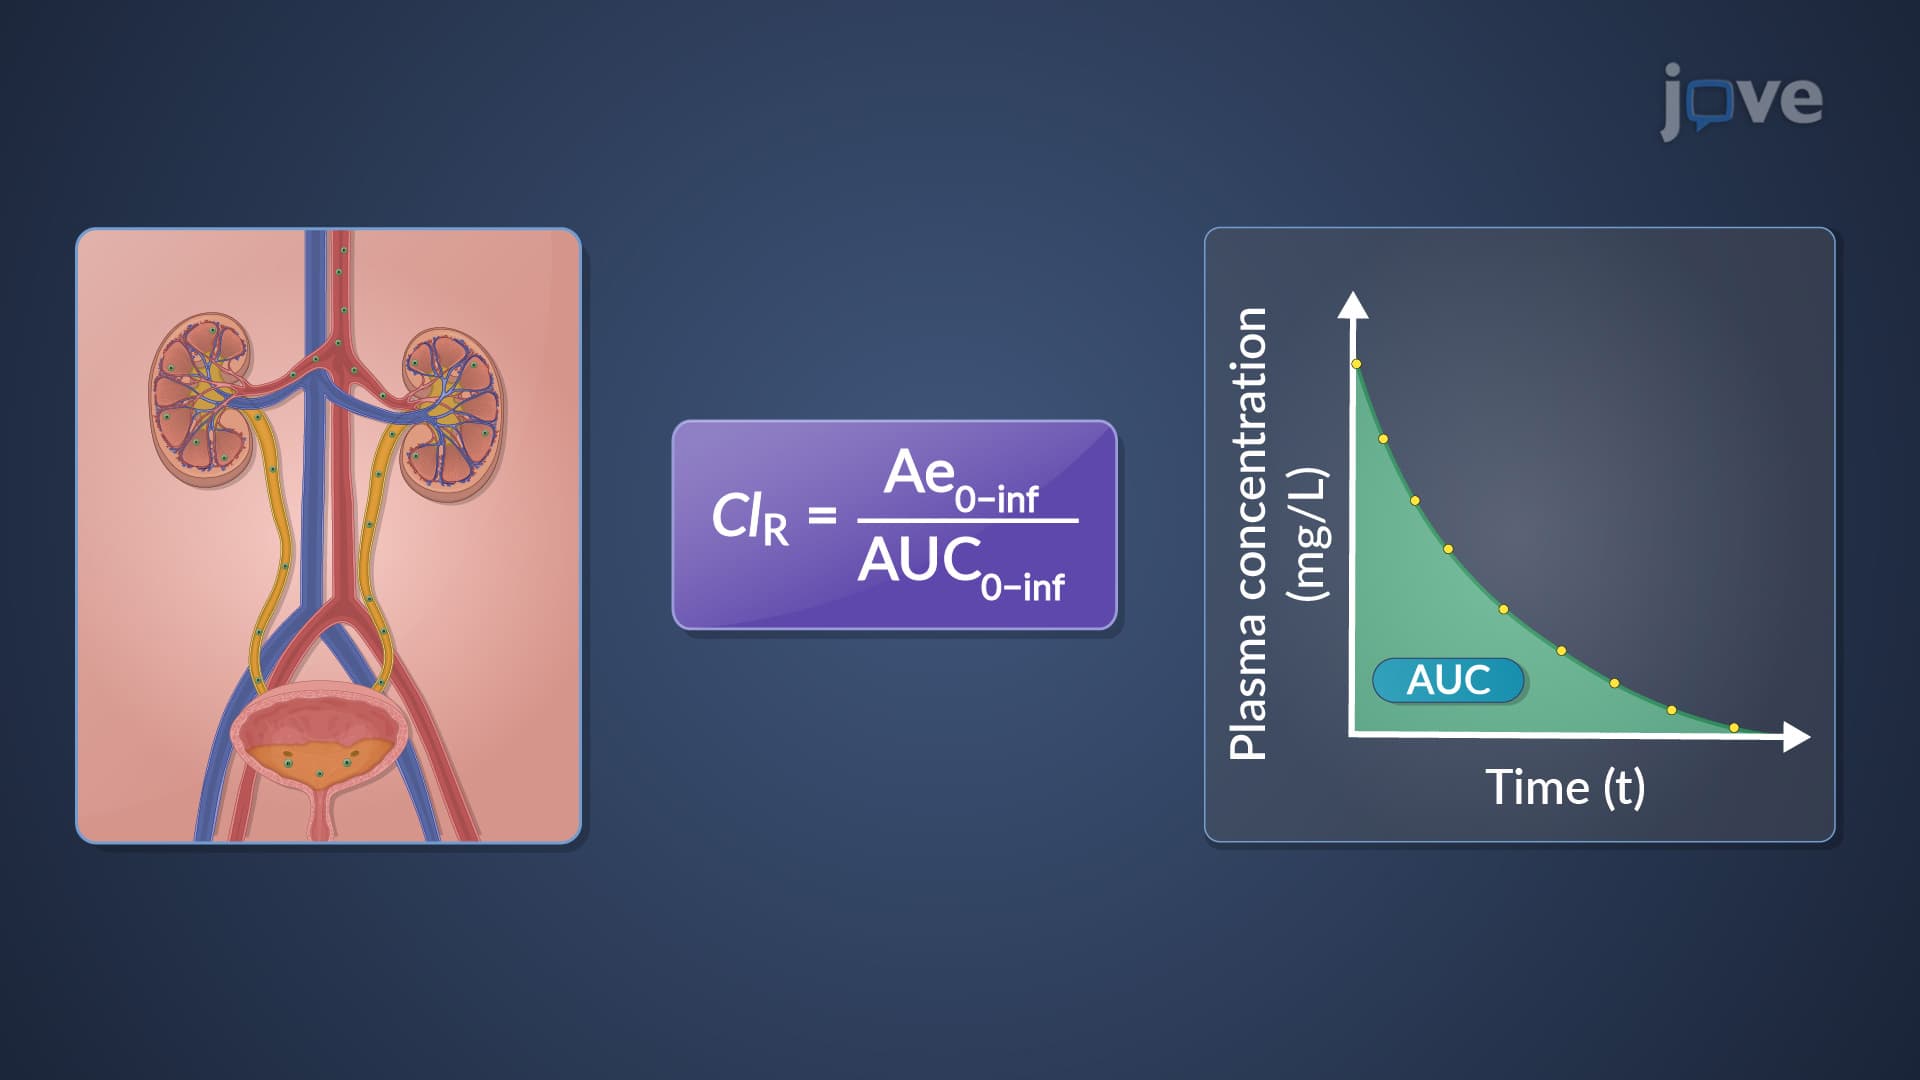
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:28
Renal Drug Excretion: Tubular Secretion