Related Experiment Video
Updated: Aug 26, 2025

Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
Non-invasive estimation of QLV from the standard 12-lead ECG in patients with left bundle branch block
Jacob Melgaard1, Peter M van Dam2,3, Anders Sommer4
1CardioTech Research Group, Department of Health Science and Technology, Faculty of Medicine, Aalborg University, Aalborg, Denmark.

Insights
A new non-invasive method estimates left ventricular lead (LV) timing (QLV) using standard ECGs, improving cardiac resynchronization therapy (CRT) planning. This technique helps optimize LV lead placement for better heart failure treatment outcomes.
Area of Science:
- Cardiology
- Biomedical Engineering
- Medical Imaging
Background:
- Cardiac resynchronization therapy (CRT) treats heart failure with electrical dyssynchrony, often indicated by a left bundle branch block (LBBB) pattern on ECG.
- Optimal CRT outcomes depend on precise left ventricular (LV) lead placement in the latest activated region, measured by QLV.
- Current limitations include unpredictable coronary venous anatomy and inability to non-invasively measure QLV pre-implantation.
Purpose of the Study:
- To develop and validate a novel non-invasive method for estimating QLV from standard 12-lead ECGs in sinus rhythm.
- To assess the accuracy of this method in predicting optimal LV lead positioning for CRT.
Main Methods:
- A cohort of 135 CRT recipients provided 12-lead ECGs, LV electrograms, and LV lead positions.
- A computational heart model was used to iteratively fit the electrical activation pattern to match measured ECGs.
- QLV was non-invasively estimated by calculating the time difference between ECG Q-wave onset and calculated LV activation time.
Main Results:
- The non-invasive QLV estimation showed no significant difference compared to measured QLV.
- The median distance between the actual and estimated LV pacing sites was 18.6 mm, indicating good spatial accuracy.
Conclusions:
- Standard 12-lead ECGs and a generic heart model can accurately estimate QLV.
- This non-invasive method holds potential for improving patient selection, optimizing CRT implant procedures, and simulating stimulation parameters.
Abstract:
Background: Cardiac resynchronization therapy (CRT) is a treatment for patients with heart failure and electrical dyssynchrony, i.e., left bundle branch block (LBBB) ECG pattern. CRT resynchronizes ventricular contraction with a right ventricle (RV) and a left ventricle (LV) pacemaker lead. Positioning the LV lead in the latest electrically activated region (measured from Q wave onset in the ECG to LV sensing by the left pacemaker electrode [QLV]) is associated with favorable outcome. However, optimal LV lead placement is limited by coronary venous anatomy and the inability to measure QLV non-invasively before implantation. We propose a novel non-invasive method for estimating QLV in sinus-rhythm from the standard 12-lead ECG. Methods: We obtained 12-lead ECG, LV electrograms and LV lead position in a standard LV 17-segment model from procedural recordings from 135 standard CRT recipients. QLV duration was measured post-operatively. Using a generic heart geometry and corresponding forward model for ECG computation, the electrical activation pattern of the heart was fitted to best match the 12-lead ECG in an iterative optimization procedure. This procedure initialized six activation sites associated with the His-Purkinje system. The initial timing of each site was based on the directions of the vectorcardiogram (VCG). Timing and position of the sites were then changed iteratively to improve the match between simulated and measured ECG. Noninvasive estimation of QLV was done by calculating the time difference between Q-onset on the computed ECG and the activation time corresponding to centroidal epicardial activation time of the segment where the LV electrode is positioned. The estimated QLV was compared to the measured QLV. Further, the distance between the actual LV position and the estimated LV position was computed from the generic ventricular model. Results: On average there was no difference between QLV measured from procedural recordings and non-invasive estimation of QLV ( ). Median distance between actual LV pacing site and the estimated pacing site was 18.6 mm (IQR 17.3 mm). Conclusion: Using the standard 12-lead ECG and a generic heart model it is possible to accurately estimate QLV. This method may potentially be used to support patient selection, optimize implant procedures, and to simulate optimal stimulation parameters prior to pacemaker implantation.
Related Concept Videos
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and...
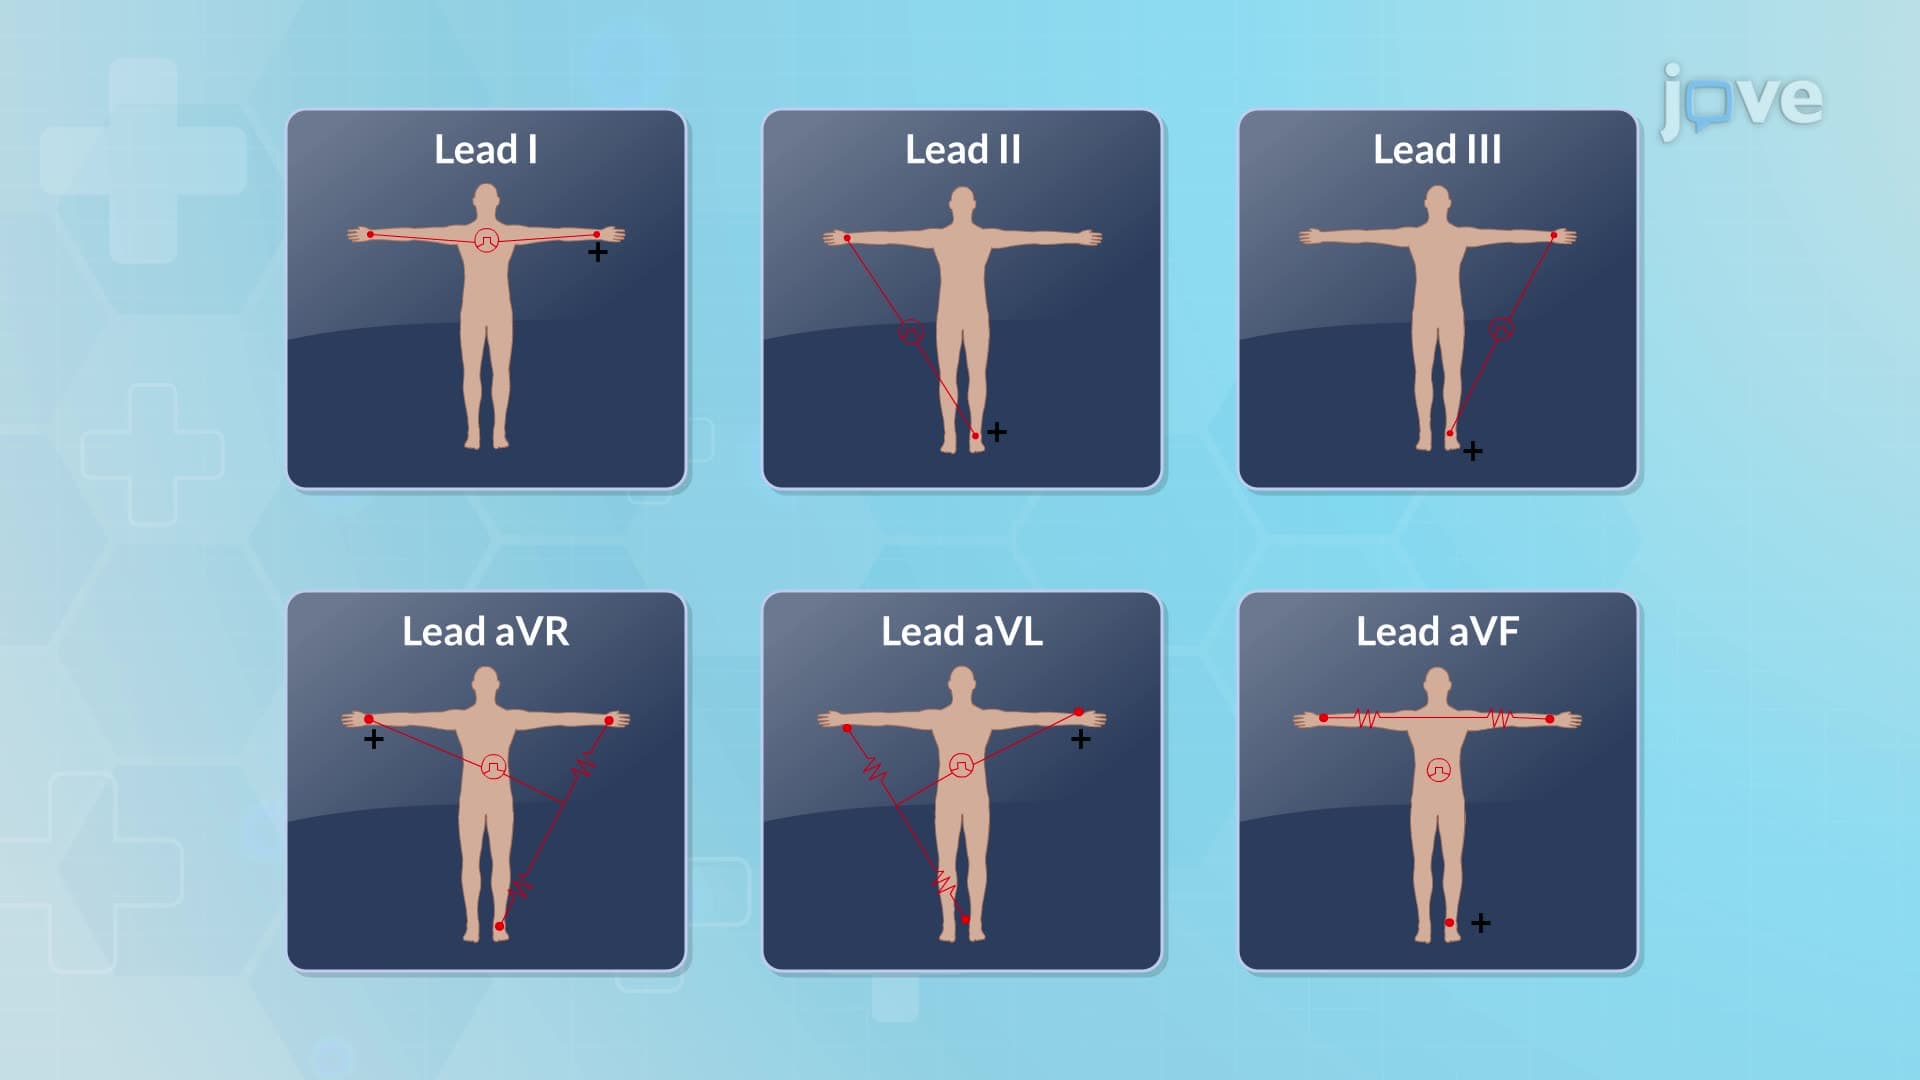 01:28
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin...
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias