Related Experiment Video
Updated: Sep 13, 2026
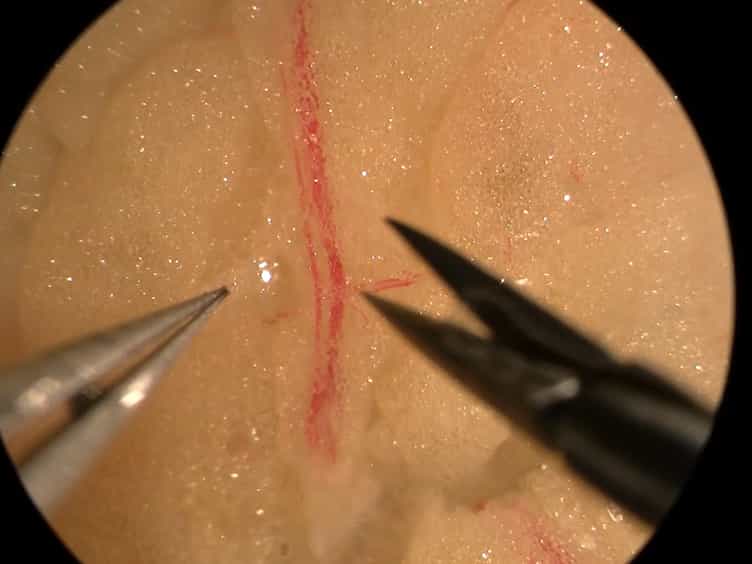

Assessment of Human Adipose Tissue Microvascular Function Using Videomicroscopy
Published on: September 29, 2017
Intestinal arteriolar responses to mucosal and serosal applications of adenosine analogues

Abstract:
Adenosine or its synthetic analogues were topically applied to the intestinal jejunum while steady-state blood flow was calculated in submucosal arterioles using video microscopy. Blood flow increased (220 or 130% of control) with the serosal application of 10(-6) M N-ethyl carboxamido adenosine (NECA, A2-selective agonist) or 2-chloro adenosine (2CA, nonselective agonist) but not with cyclohexyl adenosine (CHA, A1-selective agonist). The nonselective competitive antagonist, 8-phenyl theophylline, attenuated the response evoked by NECA. The mucosal application of 10(-6) M CHA caused blood flow decreases (81% of control), but neither NECA nor 2CA evoked a response. These observations suggest a mucosal diffusion barrier, so the concentrations of the analogues were raised one hundredfold. Serosal 10(-4) M CHA or NECA caused blood flow increases, but the effects were negligible with mucosal application, suggesting that the mucosa was indeed impermeable to these compounds. The responses evoked by 10(-4) M 2CA were similar on the serosa or mucosa (200-220% of control), submaximal (maximum = 400% of control at 10(-3) M), and not antagonized by 8-phenyl theophylline or by the cellular uptake inhibitor, nitrobenzyl-6-thio guanosine. In context with earlier studies, greater than 10(-6) M 2CA probably evokes vasodilation that is not entirely mediated by extracellular receptors. Serosal adenosine (10(-4) M) caused submaximal blood flow increases (200% of control) that were not potentiated by nitrobenzyl-6-thio guanosine or another transport inhibitor, dipyridamole.(ABSTRACT TRUNCATED AT 250 WORDS)
More Related Videos
 08:41
Assessment of Vascular Tone Responsiveness using Isolated Mesenteric Arteries with a Focus on Modulation by Perivascular Adipose Tissues
Published on: June 3, 2019
 05:58
Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
Related Concept Videos
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:31
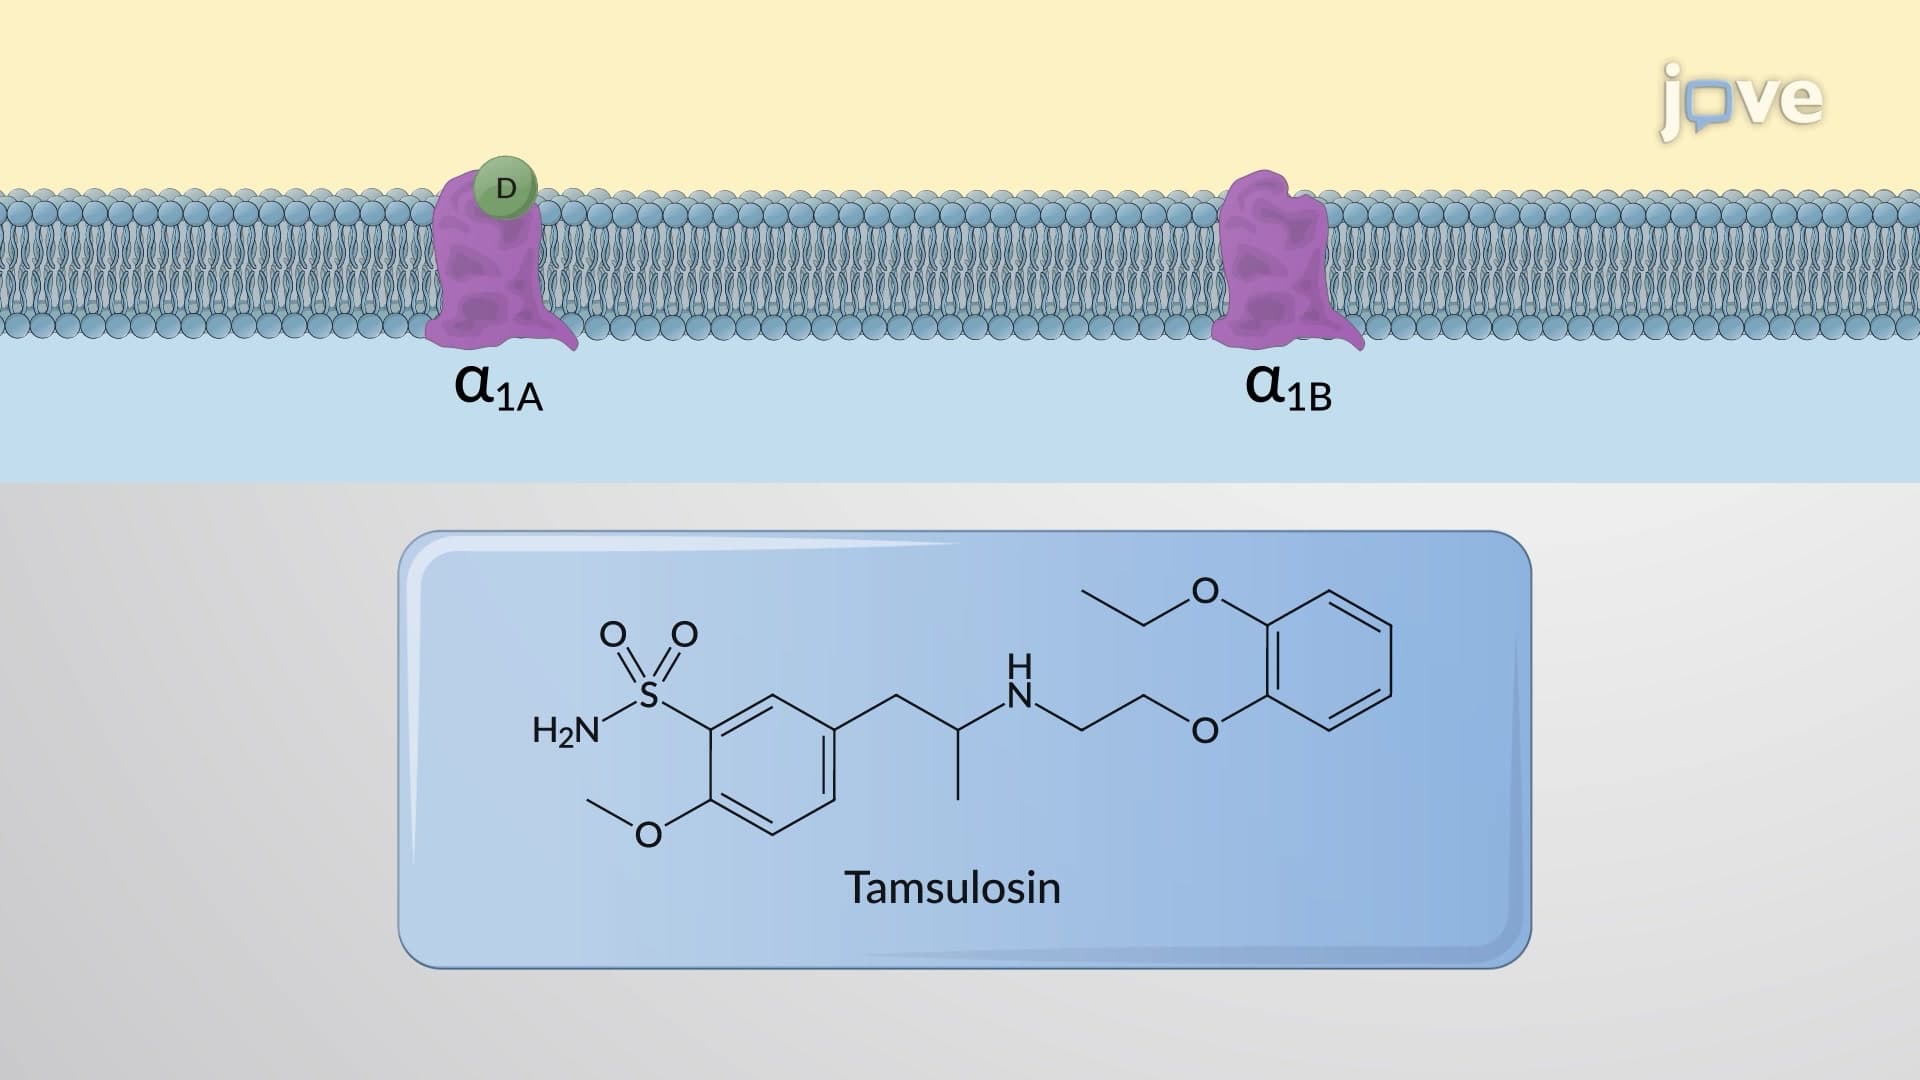
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
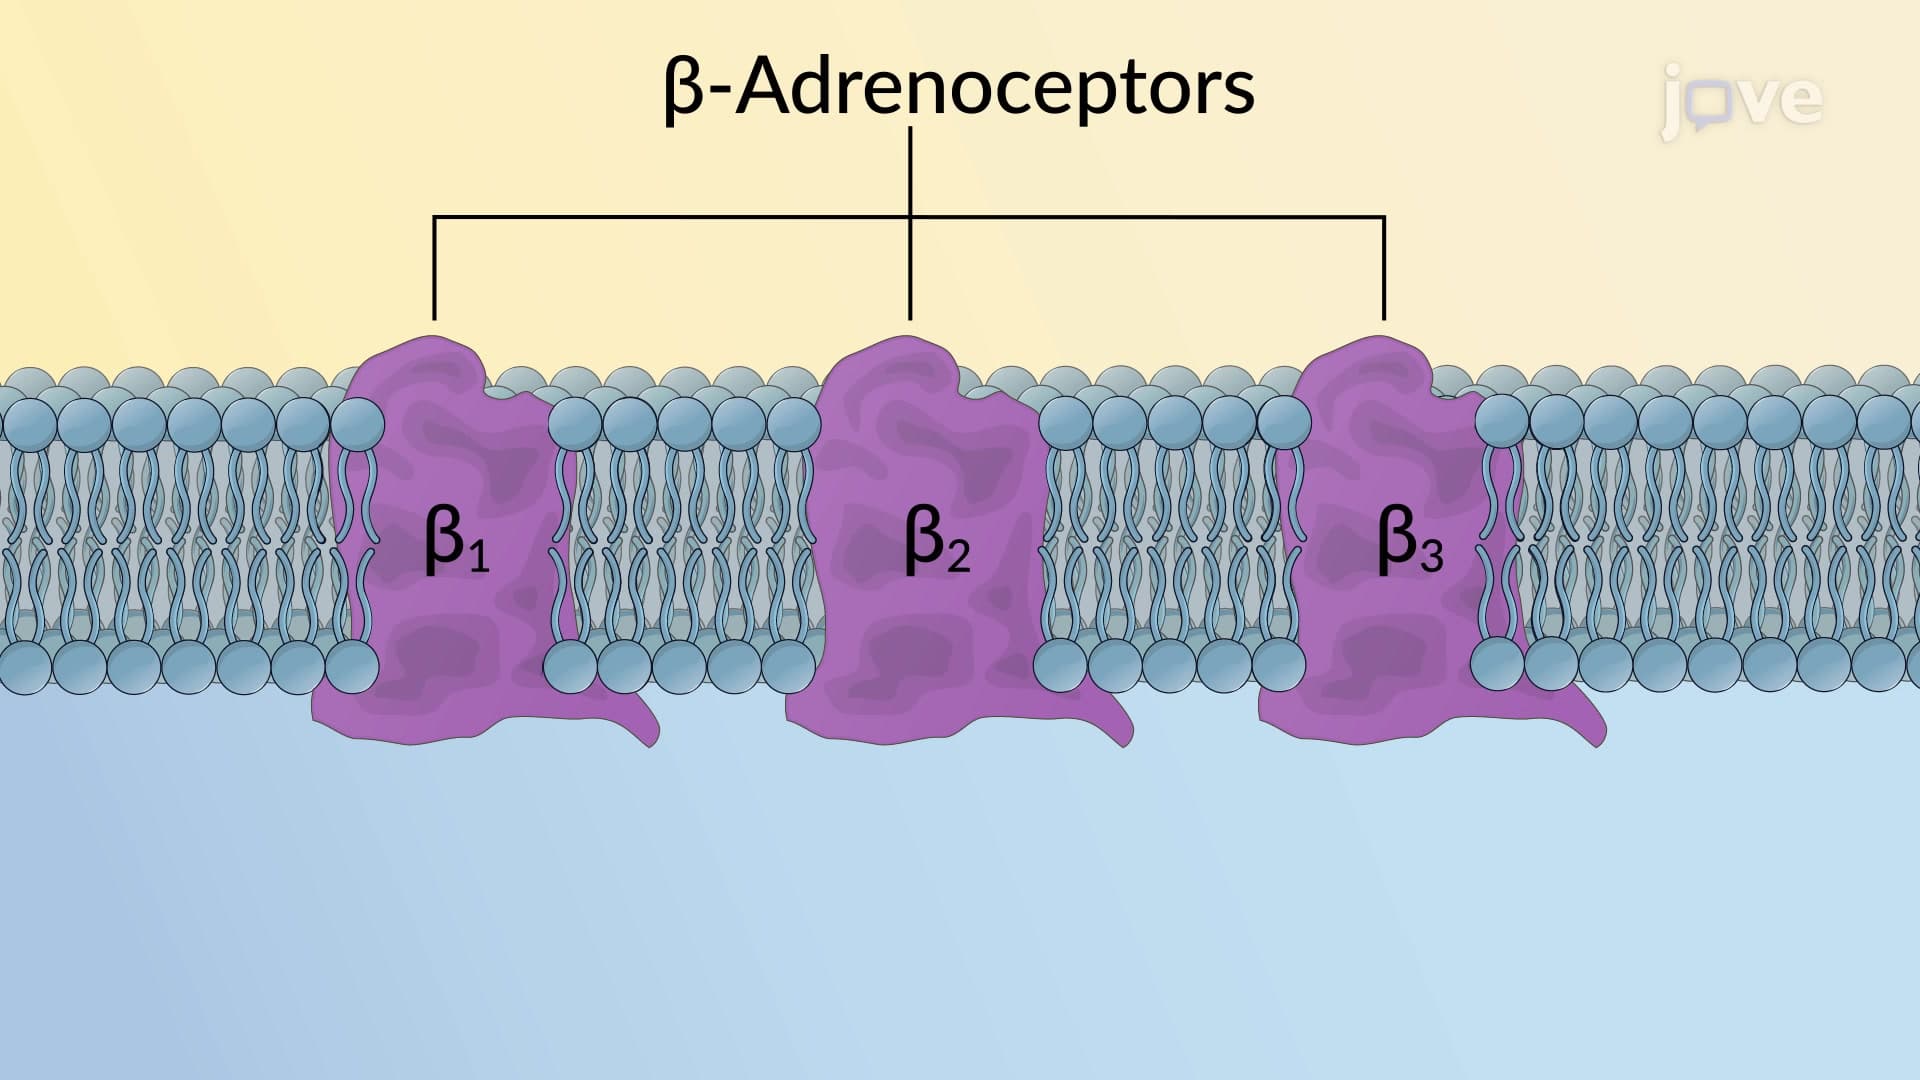
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers