Immunohistochemical comparison of lateral bone augmentation using a synthetic TiO2 block or a xenogeneic graft in
Minh Khai Le Thieu1,2, Sabine Stoetzel2, Maryam Rahmati1
1Department of Periodontology, Institute of Clinical Dentistry, Faculty of Dentistry, University of Oslo, Oslo, Norway.

Objectives:
To evaluate osteogenic markers and alveolar ridge profile changes in guided bone regeneration (GBR) of chronic noncontained bone defects using a nonresorbable TiO2 block.
Materials And Methods:
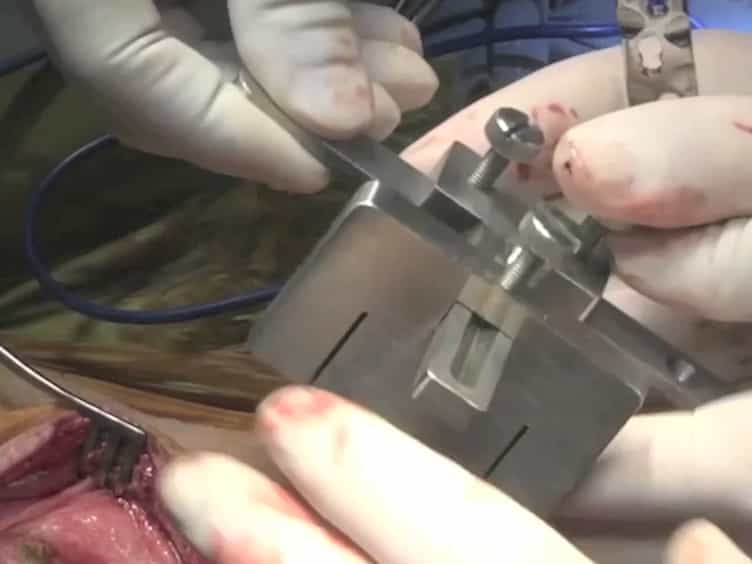
Three buccal bone defects were created in each hemimandible of eight beagle dogs and allowed to heal for 8 weeks before GBR. Treatment was assigned by block randomization: TiO2 block: TiO2 -scaffold and a collagen membrane, DBBM particulates: Deproteinized bovine bone mineral (DBBM) and a collagen membrane, Empty control: Only collagen membrane. Bone regeneration was assessed on two different healing timepoints: early (4 weeks) and late healing (12 weeks) using several immunohistochemistry markers including alpha-smooth muscle actin (α-SMA), osteopontin, osteocalcin, tartrate-resistant acid phosphatase, and collagen type I. Histomorphometry was performed on Movat Pentachrome-stained and Von Kossa/Van Gieson-stained sections. Stereolithographic (STL) models were used to compare alveolar profile changes.
Results:
The percentage of α-SMA and osteopontin increased in TiO2 group after 12 weeks of healing at the bone-scaffold interface, while collagen type I increased in the empty control group. In the defect area, α-SMA decreased in the empty control group, while collagen type I increased in the DBBM group. All groups maintained alveolar profile from 4 to 12 weeks, but TiO2 group demonstrated the widest soft tissue contour profile.
Conclusions:
The present findings suggested contact osteogenesis when GBR is performed with a TiO2 block or DBBM particulates. The increase in osteopontin indicated a potential for bone formation beyond 12 weeks. The alveolar profile data indicated a sustained lateral increase in lateral bone augmentation using a TiO2 block and a collagen membrane, as compared with DBBM and a collagen membrane or a collagen membrane alone.