Related Experiment Video
Updated: Aug 26, 2025

Live Imaging of Antifungal Activity by Human Primary Neutrophils and Monocytes in Response to A. fumigatus
Published on: April 19, 2017
Population pharmacokinetics of voriconazole and initial dosage optimization in patients with talaromycosis
Zhiwen Jiang1,2, Yinyi Wei3, Weie Huang4
1Department of Dermatology and Venereology, The First Affiliated Hospital of Guangxi Medical University, Nanning, China.

Abstract:
The high variability and unpredictability of the plasma concentration of voriconazole (VRC) pose a major challenge for clinical administration. The aim of this study was to develop a population pharmacokinetics (PPK) model of VRC and identify the factors influencing VRC PPK in patients with talaromycosis. Medical records and VRC medication history of patients with talaromycosis who were treated with VRC as initial therapy were collected. A total of 233 blood samples from 69 patients were included in the study. A PPK model was developed using the nonlinear mixed-effects models (NONMEM). Monte Carlo simulation was applied to optimize the initial dosage regimens with a therapeutic range of 1.0-5.5 mg/L as the target plasma trough concentration. A one-compartment model with first-order absorption and elimination adequately described the data. The typical voriconazole clearance was 4.34 L/h, the volume of distribution was 97.4 L, the absorption rate constant was set at 1.1 h-1, and the bioavailability was 95.1%. Clearance was found to be significantly associated with C-reactive protein (CRP). CYP2C19 polymorphisms had no effect on voriconazole pharmacokinetic parameters. Monte Carlo simulation based on CRP levels showed that a loading dose of 250 mg/12 h and a maintenance dose of 100 mg/12 h are recommended for patients with CRP ≤ 96 mg/L, whereas a loading dose of 200 mg/12 h and a maintenance dose of 75 mg/12 h are recommended for patients with CRP > 96 mg/L. The average probability of target attainment of the optimal dosage regimen in CRP ≤ 96 mg/L and CRP > 96 mg/L groups were 61.3% and 13.6% higher than with empirical medication, and the proportion of Cmin > 5.5 mg/L decreased by 28.9%. In conclusion, the VRC PPK model for talaromycosis patients shows good robustness and predictive performance, which can provide a reference for the clinical individualization of VRC. Adjusting initial dosage regimens based on CRP may promote the rational use of VRC.
More Related Videos
 06:49
Reduced Itraconazole Concentration and Durations Are Successful in Treating Batrachochytrium dendrobatidis Infection in Amphibians
Published on: March 14, 2014
 08:54
Broth Microdilution In Vitro Screening: An Easy and Fast Method to Detect New Antifungal Compounds
Published on: February 14, 2018
Related Concept Videos
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady...
 01:15
Drug Dosage Regimen: Overview
Typically, the starting dose and dosing interval are guided by the manufacturer's recommendations based on clinical trials conducted during and after drug...
 01:01
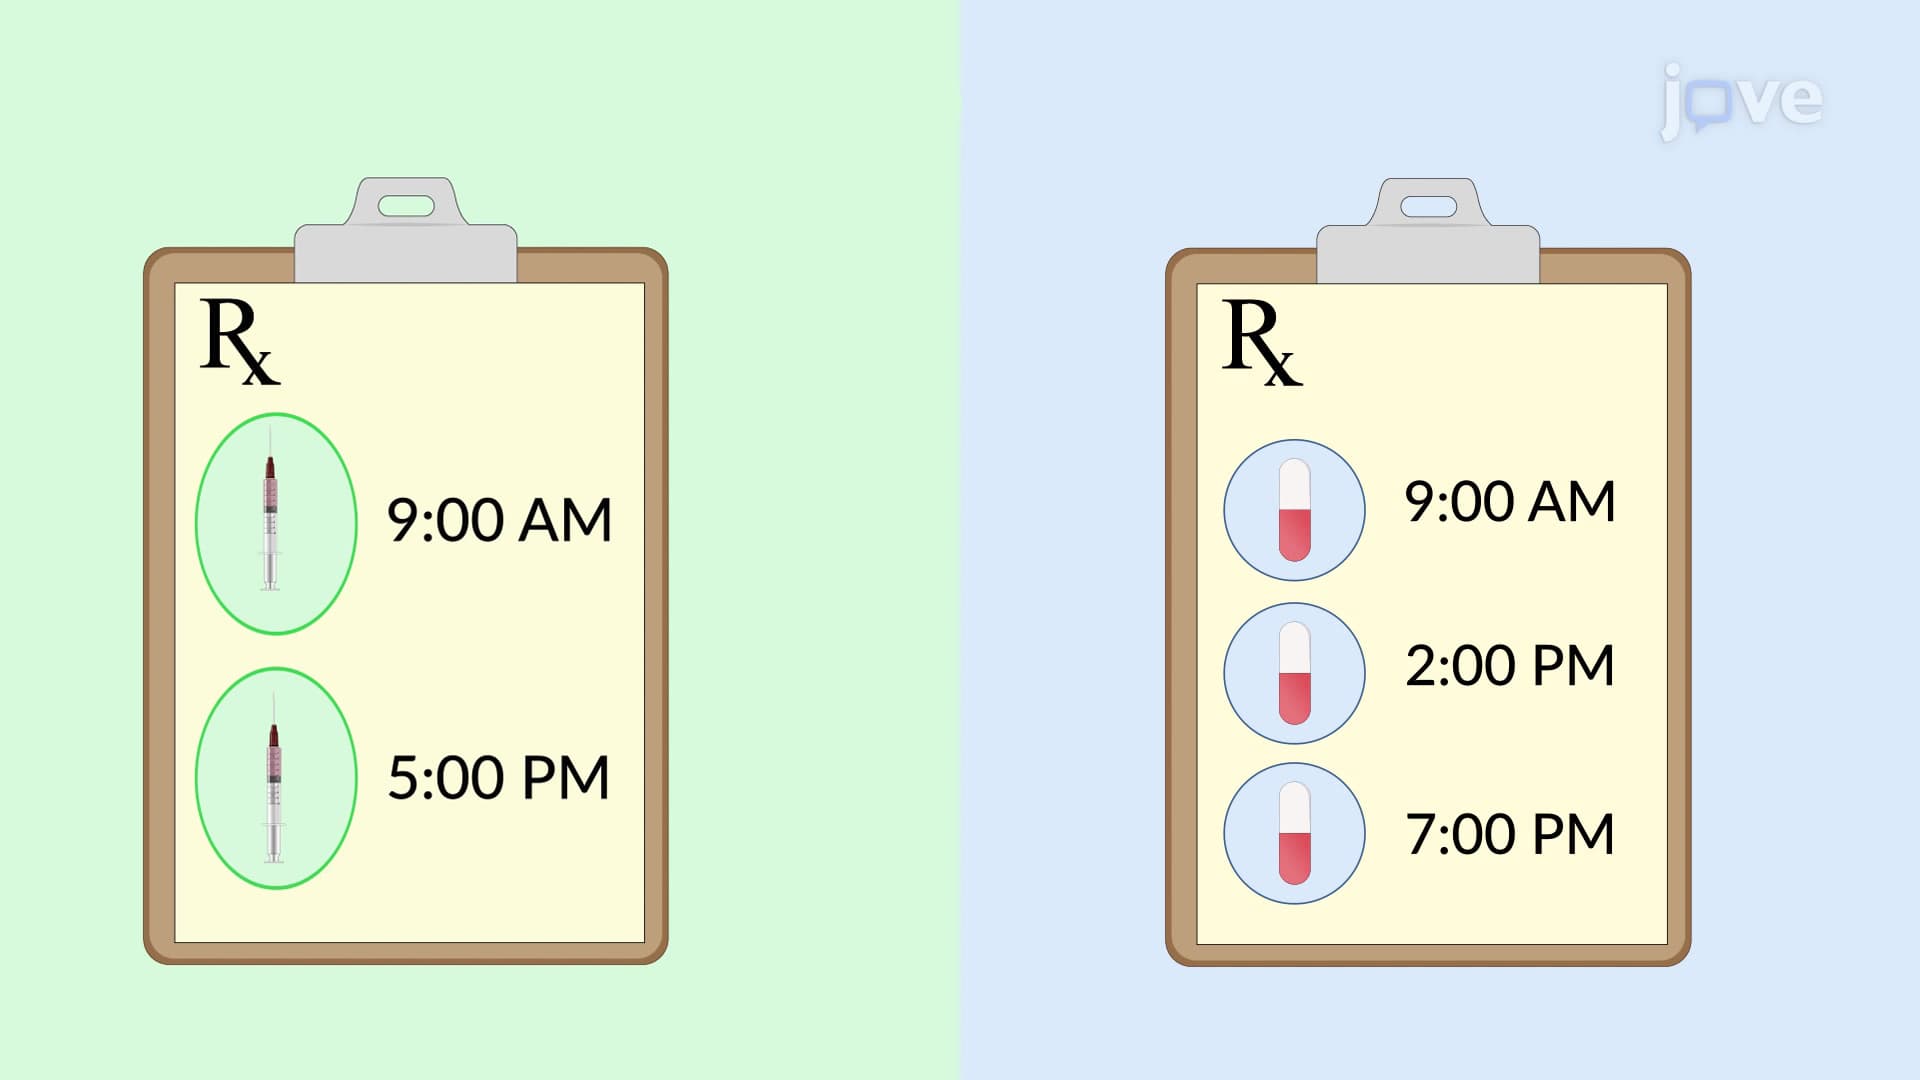
Dosage Regimen: Fixed Dose
Fixed-dose regimens can be used for various routes of administration, including intravenous (IV) injections and oral medications. For IV administration, a predetermined amount of the drug is...
 01:10
Pharmacokinetics: Overview
 01:23
Nonlinear Pharmacokinetics: Dependence of Elimination Half-Life and Dose Clearance
A study on guinea pigs examined the...
 00:59
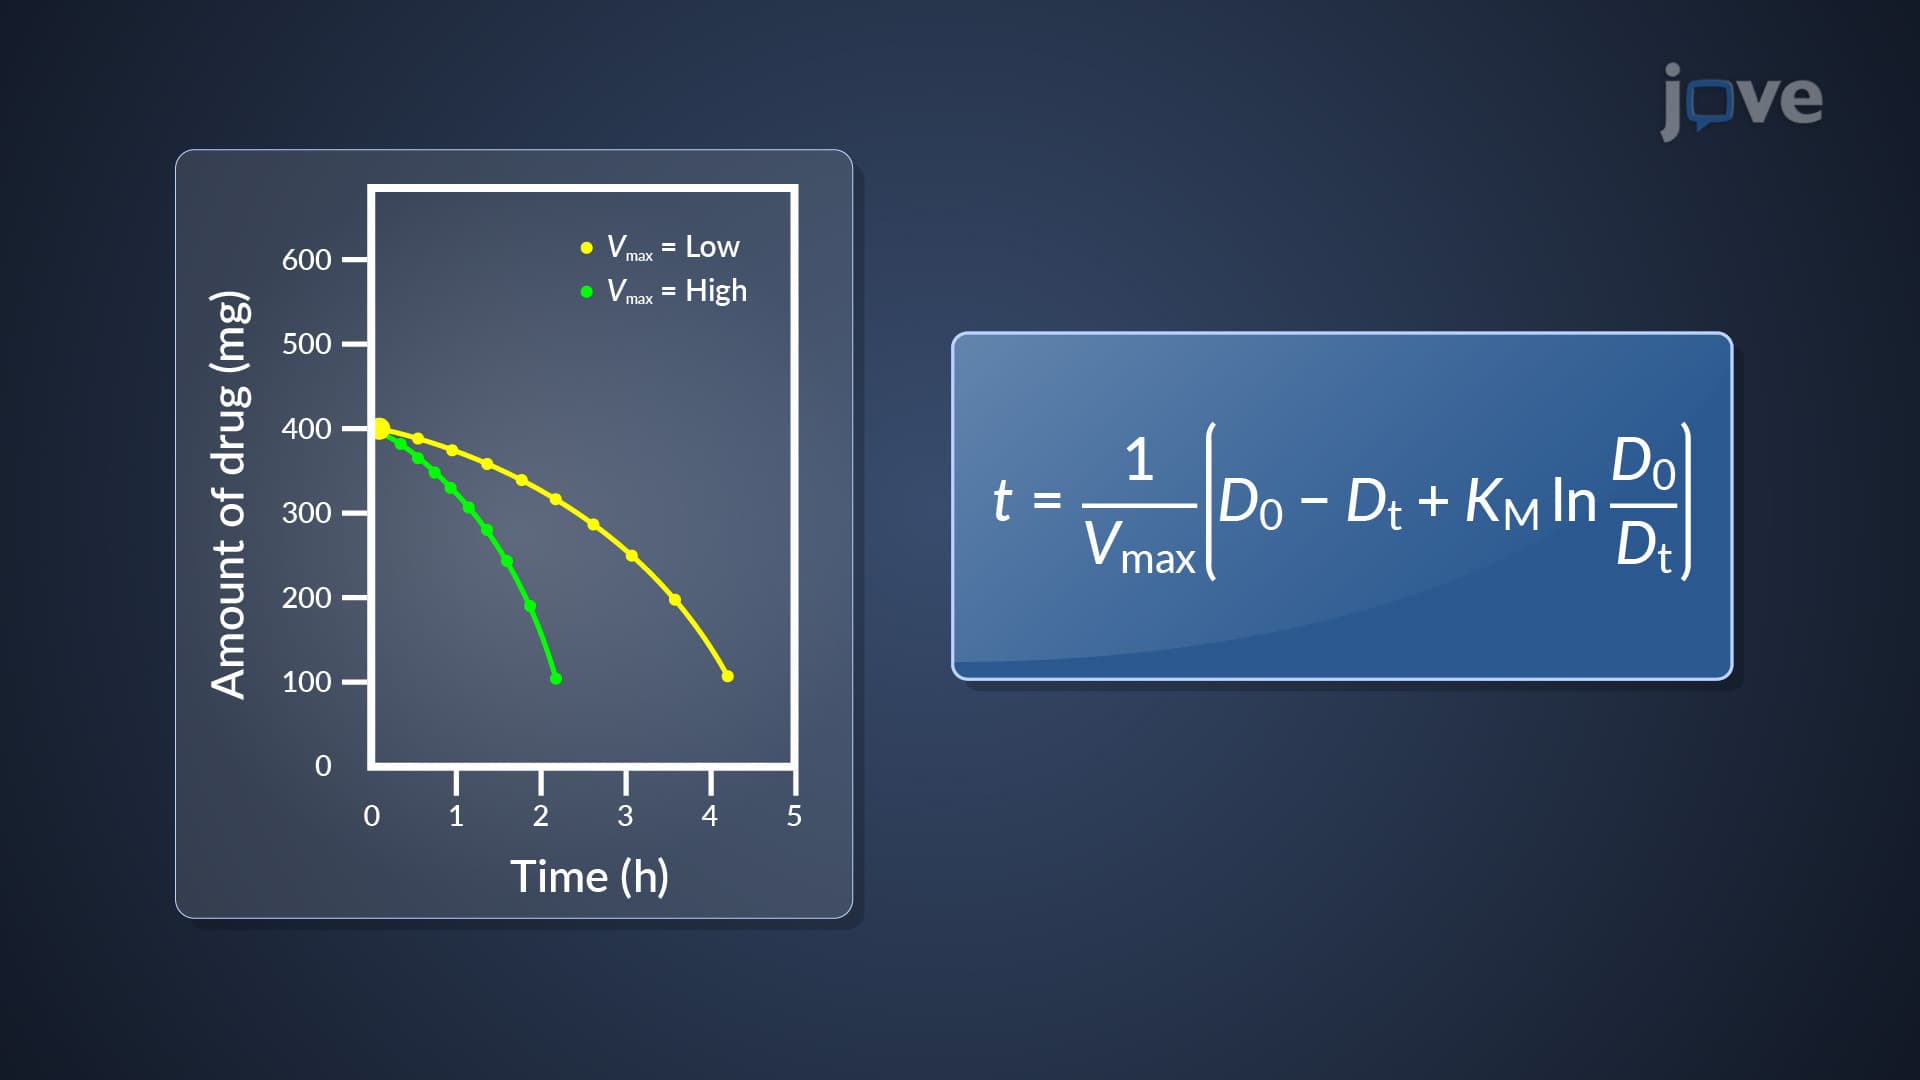
Nonlinear Pharmacokinetics: Drug Elimination for IV Bolus Injection
Following the administration of a single intravenous (IV) bolus injection, we can determine the concentration of the drug in the plasma at any given time. This calculation is achieved using a specific equation that integrates the values of Vmax and KM.
We can also...