Cerebrospinal Fluid Shunting in Children with Hydrocephalus and Increased Intracranial Pressure Secondary to Human Immunodeficiency Virus-Related Cryptococcal Meningitis
Related Experiment Video
Updated: Aug 25, 2025
Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
Basil Enicker1, Colleen Aldous2
1Department of Neurosurgery, Inkosi Albert Luthuli Central Hospital, KwaZulu-Natal, Durban, South Africa; Nelson R. Mandela School of Medicine, University of KwaZulu-Natal, Durban, South Africa.

Insights
Cerebrospinal fluid (CSF) shunting is a viable treatment for hydrocephalus in children with HIV-related cryptococcal meningitis, reducing mortality. This study highlights shunt outcomes in pediatric patients, offering crucial data for managing this rare condition.
Area of Science:
- Pediatric Neurosurgery
- Infectious Diseases
- Critical Care Medicine
Background:
- Hydrocephalus and increased intracranial pressure (ICP) due to HIV-related cryptococcal meningitis are uncommon in children.
- The efficacy and outcomes of cerebrospinal fluid (CSF) shunting in this pediatric population are not well-documented.
Purpose of the Study:
- To report the experience and outcomes of CSF shunting in managing hydrocephalus and increased ICP in children with HIV-related cryptococcal meningitis.
- To evaluate the role of shunting procedures in this specific pediatric cohort.
Main Methods:
- Retrospective review of data from a single neurosurgery unit over 14 years.
- Inclusion of patient demographics, clinical presentation, Glasgow Coma Scale scores, CSF pressure, antiretroviral therapy status, laboratory results, neuroimaging, shunting procedures, complications, and mortality.
- Analysis of outcomes including mortality and survival rates at 1-year follow-up.
Main Results:
- Seventeen children underwent CSF shunting, with a median age of 10 years; all were on antiretroviral therapy.
- Common symptoms included headaches (100%), visual impairment (82%), and seizures (47%), with 88% having elevated CSF opening pressure (>30 cm H2O).
- Ventriculoperitoneal shunts were most common (82%), with infection and obstruction each occurring in 18% of cases. Mortality was 18%, with 59% alive at 1 year.
Conclusions:
- CSF shunting, including ventriculoperitoneal and lumboperitoneal shunts, is a critical management option for pediatric hydrocephalus secondary to HIV-related cryptococcal meningitis.
- Treatment with shunts is effective regardless of CD4 count and can significantly reduce mortality in suitable pediatric patients.
- This study provides the largest series on CSF shunting for this condition in children, underscoring its importance in reducing mortality.
Background:
Hydrocephalus and increased intracranial pressure secondary to human immunodeficiency virus-related cryptococcal meningitis are rare in children. The role and outcomes of cerebrospinal fluid (CSF) shunting in children are not well reported. We report our experience with CSF shunting in the management of this condition in children over a 14-year period.
Methods:
This was a retrospective review of data collected from a single neurosurgery unit. Data collected included demographics, clinical characteristics, Glasgow Coma Scale score, lumbar puncture opening pressure, antiretroviral therapy, laboratory results, neuroimaging findings, shunting procedures, complications, and mortality.
Results:
Seventeen children underwent CSF shunting. Median age was 10 years (range, 6-13), most being male (76%). All children were on antiretroviral therapy. Median Glasgow Coma Scale score was 15 (interquartile range [IQR], 14-15). Clinical characteristics included headaches (100%), visual impairment (82%), and seizures (47%). Lumbar puncture opening pressure was >30 cm H2O in 88% of children. Median CD4 count was 45 cells/μL (IQR, 17-56). Computed tomography brain scans showed hydrocephalus in 14 children (82%). Surgical procedures included ventriculoperitoneal shunts (82%) and lumboperitoneal shunts (18%). Shunt complications included infection (18%) and obstruction (18%). Staphylococcus aureus was cultured in all infections. Median follow-up was 45 months (IQR, 7.5-74). Three children (18%) died during the admission period. Ten children (59%) were alive at 1 year follow-up.
Conclusions:
This study is the largest series reporting on CSF shunting of hydrocephalus and increased intracranial pressure in children with human immunodeficiency virus-related cryptococcal meningitis. Treatment with ventriculoperitoneal shunt and lumboperitoneal shunt regardless of the CD4 count is an important option in suitable children to reduce mortality.

Related Concept Videos
 01:21
Cerebrospinal Fluid
CSF Production
CSF is produced mainly in the choroid plexus, a network of capillaries and ependymal cells located within the ventricular system of the brain....
 01:18
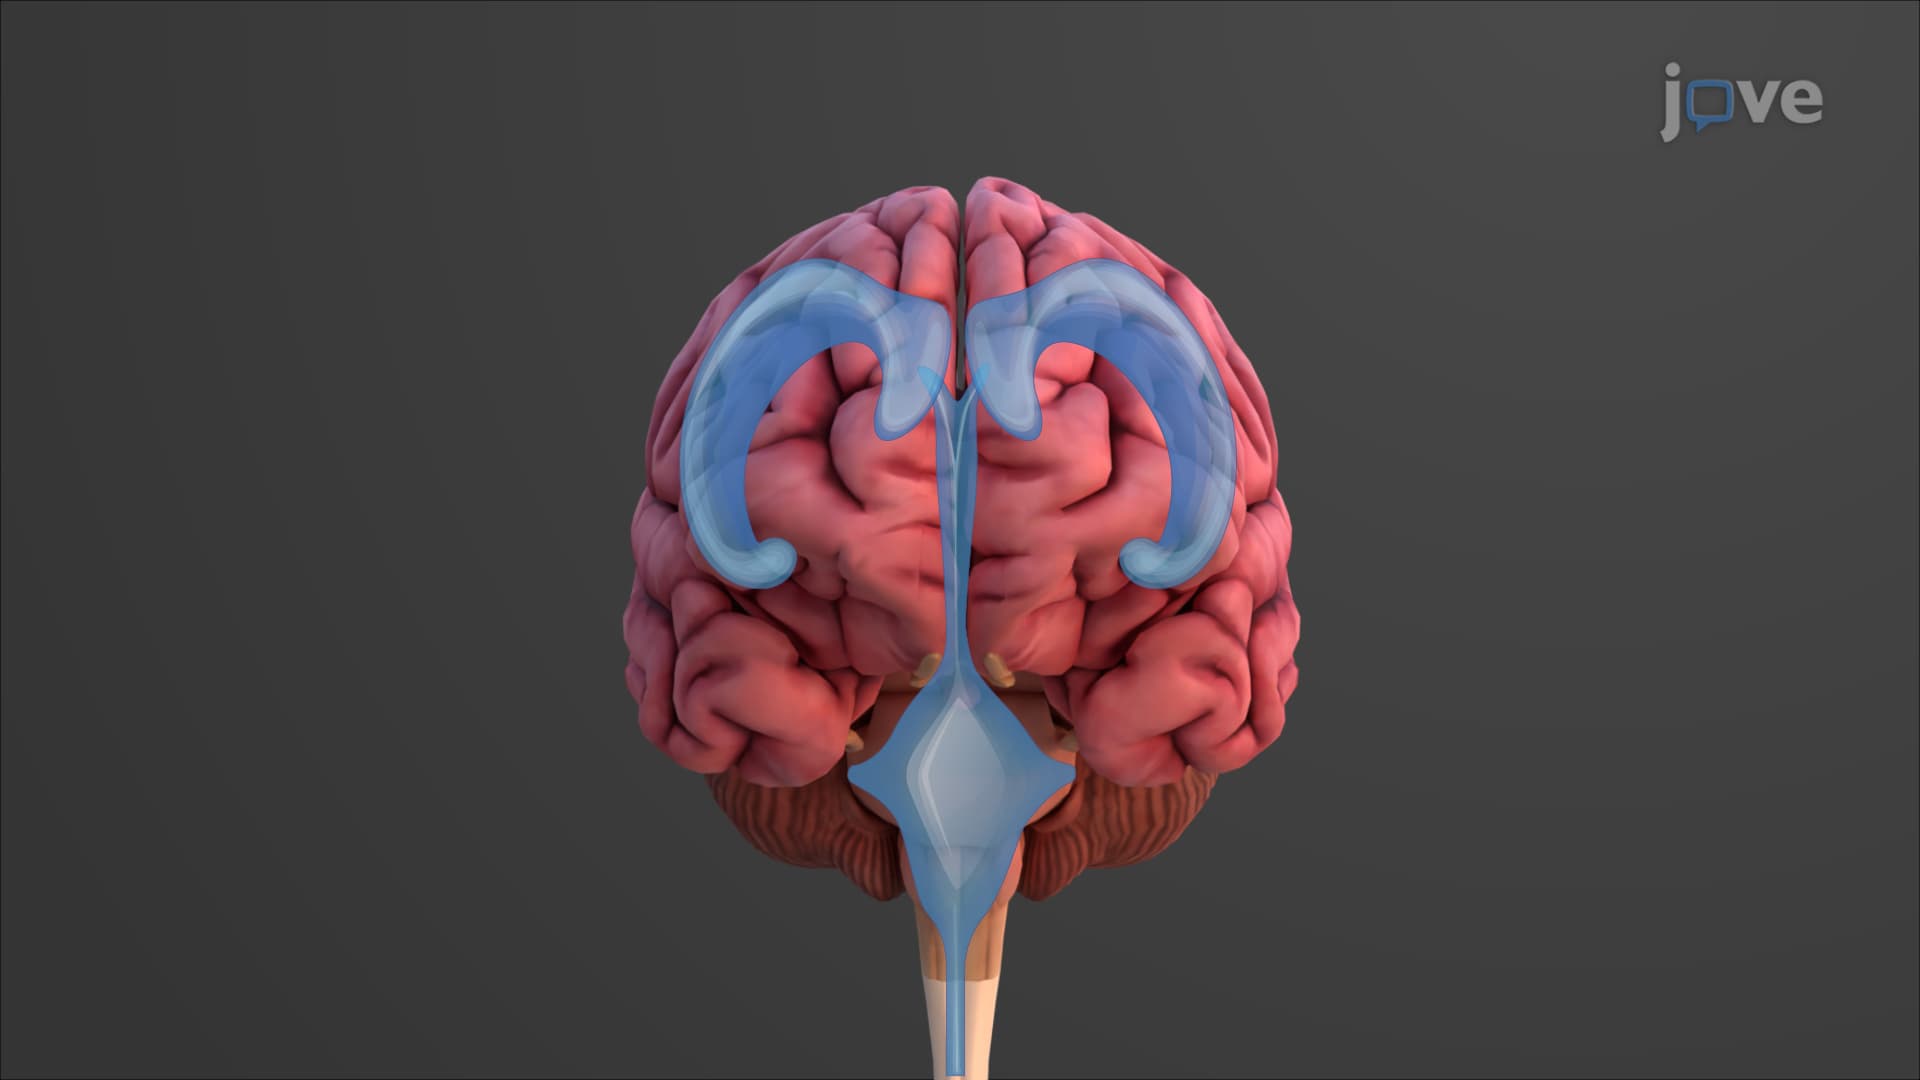
Anatomy of the Brain: Ventricles