Related Experiment Video
Updated: Aug 25, 2025

Author Spotlight: Studying Clinical Characters and Epilepsy Outcomes After Frontal Disconnection in Patients with MOGHE
Published on: August 16, 2024
Seizure outcome after resection of insular glioma: a systematic review, meta-analysis, and institutional experience
John J Y Zhang1,2, Keng Siang Lee1,3, Doris D Wang1
11Department of Neurological Surgery, University of California, San Francisco, California.

Objective:
Gliomas arising from the insular cortex can be epileptogenic, with a significant proportion of patients having medically refractory epilepsy. The impact of surgery on seizure control for such tumors is not well established. In this study, the authors aimed to investigate seizure outcomes after resection of insular gliomas using a meta-analysis and institutional experience.
Methods:
Three databases (Ovid MEDLINE, Embase, and Cochrane Central Register of Controlled Trials) were systematically searched for published studies of seizure outcomes after insular glioma resection from database inception to March 27, 2021. In addition, data were retrospectively collected on all adults (age > 17 years) who had undergone insular glioma resection between June 1997 and June 2015 at the authors' institution. Primary outcome measures were seizure freedom rates at 1 year and the last follow-up. Secondary outcome measures consisted of persistent postoperative neurological deficit beyond 90 days, mortality, and tumor progression or recurrence.
Results:
Eight studies reporting on 453 patients who had undergone 460 operations were included in the meta-analysis. The pooled mean age of the patients was 42 years. The pooled percentages of patients with extents of resection (EORs) ≥ 90%, 70%-89%, and < 70% were 55%, 33%, and 11%, respectively. The pooled seizure freedom rate at 1 year was 73% for Engel class IA and 78% for Engel class I. The pooled seizure freedom rate at the last follow-up was 60% for Engel class IA and 79% for Engel class I. The pooled percentage of persistent neurological deficit beyond 90 days was 3%. At the authors' institution, 109 patients had undergone resection of insular glioma. A greater EOR was the only significant independent predictor of seizure freedom after surgery (HR 0.290, p = 0.017). The optimal threshold for seizure freedom corresponded to an EOR of 81%. Patients with an EOR > 81% had a significantly higher seizure freedom rate (OR 2.16, p = 0.048).
Conclusions:
Maximal safe resection can be performed with minimal surgical morbidity to achieve favorable seizure freedom rates in both the short and long term. When gross-total resection is not possible, an EOR > 81% confers the greatest sensitivity and specificity for achieving seizure freedom. Systematic review registration no.: CRD42021249404 (https://www.crd.york.ac.uk/prospero/).
More Related Videos
 11:29
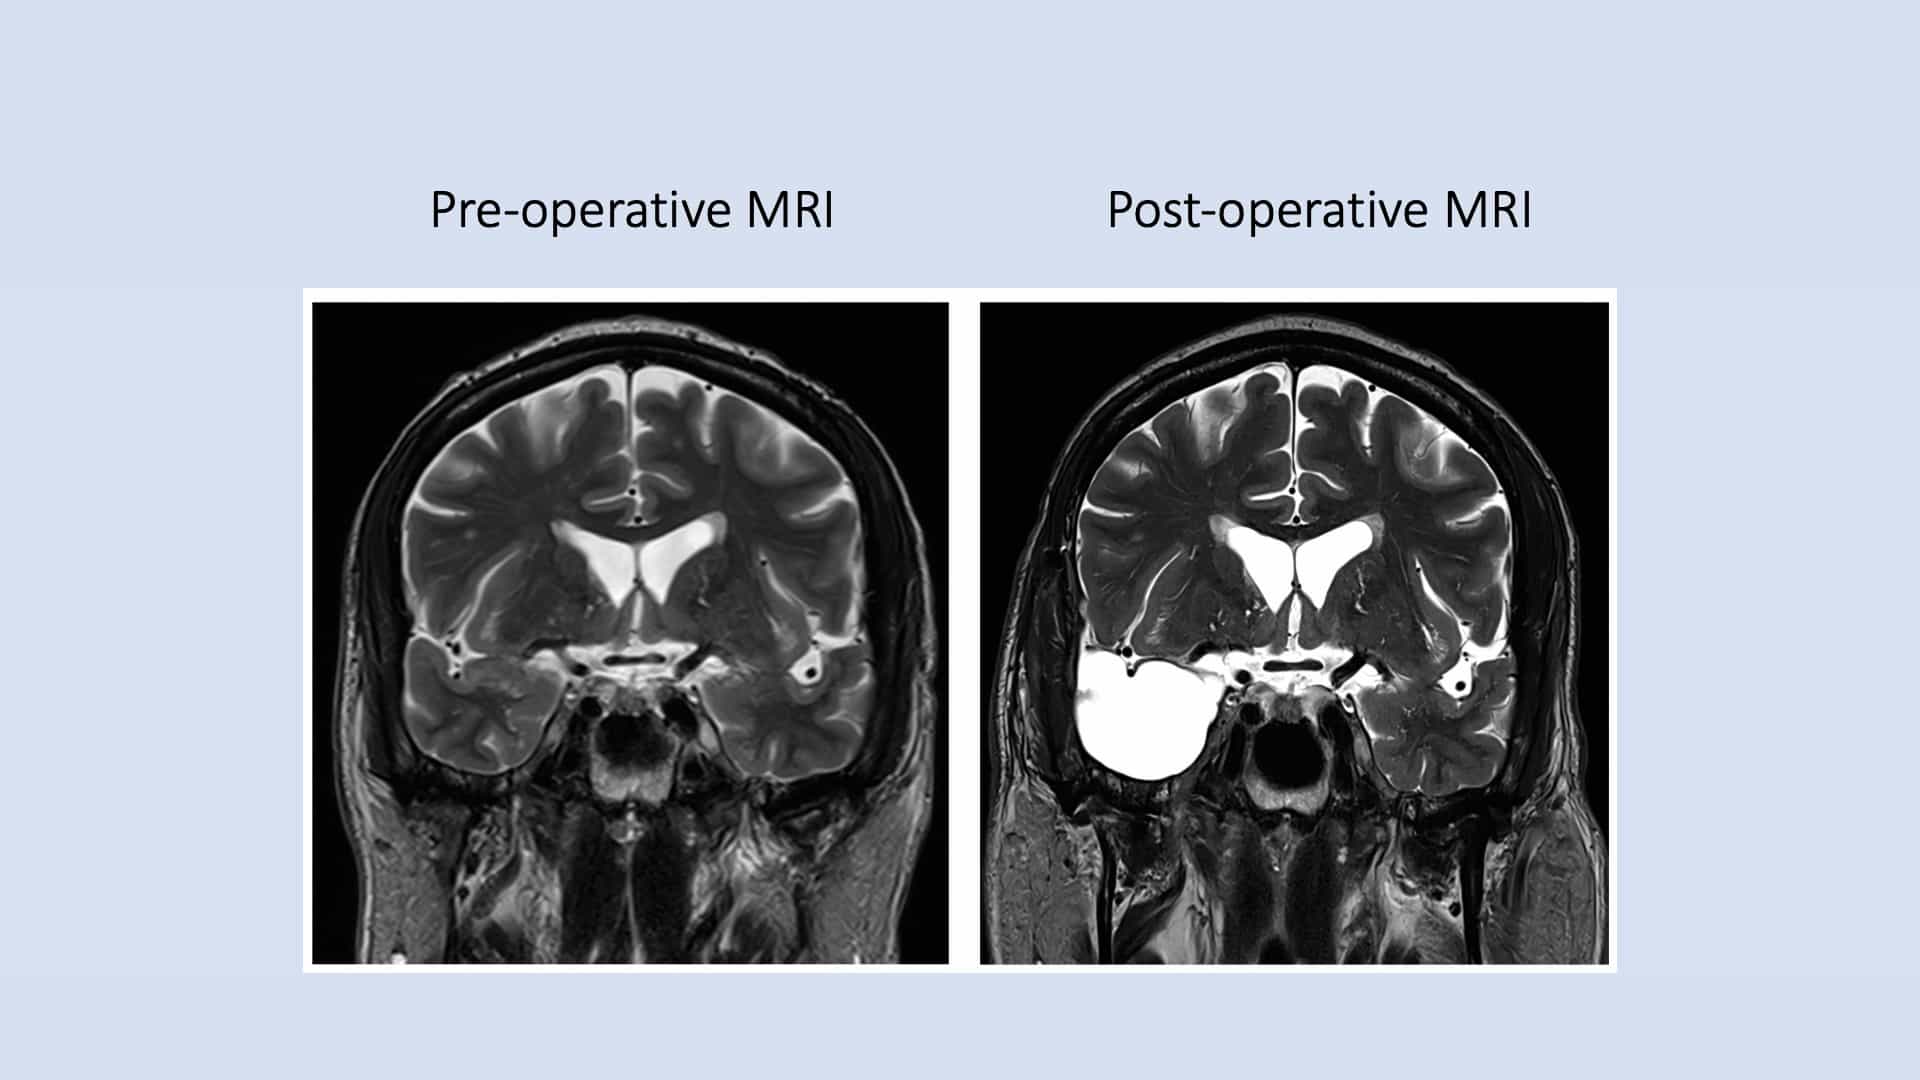
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
 05:54
Stereo-Electro-Encephalo-Graphy SEEG With Robotic Assistance in the Presurgical Evaluation of Medical Refractory Epilepsy: A Technical Note
Published on: June 13, 2016
Related Concept Videos
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types:
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...