Related Experiment Video
Updated: Aug 25, 2025


Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Anatomical variations of the pelvis during abdominal hysterectomy for benign conditions
A Matsas1, T Vavilis2, D Chrysikos3
1Laboratory of Experimental Surgery and Surgical Research N.S. Christeas, Medical School, National and Kapodistrian University of Athens, Greece.

Background:
Anatomical variations are defined as atypical morphologic and positional presentations of anatomical entities. Pelvic anatomical variations encountered during abdominal hysterectomy can be of clinical interest, given that misidentification of certain structures can lead to iatrogenic injuries and postoperative sequelae. The aim of the present study was to detect and highlight the anatomical structures of interest and their variations to the surgeon performing abdominal hysterectomy for benign conditions.
Materials And Methods:
A narrative review of the literature was performed including reports of anatomical variations encountered in cadavers, by surgeons during abdominal hysterectomy and radiologists on computed tomography angiography, searching within a 10-year span on PubMed database. Studies regarding the treatment of malignant conditions requiring lymphadenectomy and different modes of surgical approach were reviewed with regards to the aspects relevant to benign conditions. The search was extended to the reference lists of all retrieved articles.
Results:
Ureters and the uterine arteries, due to anatomical variations, are the anatomical structures most vulnerable during abdominal hysterectomy. Specifically, the ureters can present multiplications, retroiliac positionings and ureteric diverticula, whereas, the uterine arteries can present notable variability in their origins. Such variations can be detected preoperatively or intraoperatively.
Conclusions:
Although rare, the presence of anatomical variations of the uterine arteries and ureters can increase the possibility of complications should they escape detection. Intraoperative misidentification could lead to improper dissection or ligation of the affected structures. Knowledge of these variations, coupled with extensive preoperative investigation and intraoperative vigilance can minimise the risk of complications.
More Related Videos
 03:30
Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
 05:46
Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Related Concept Videos
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...
 01:26
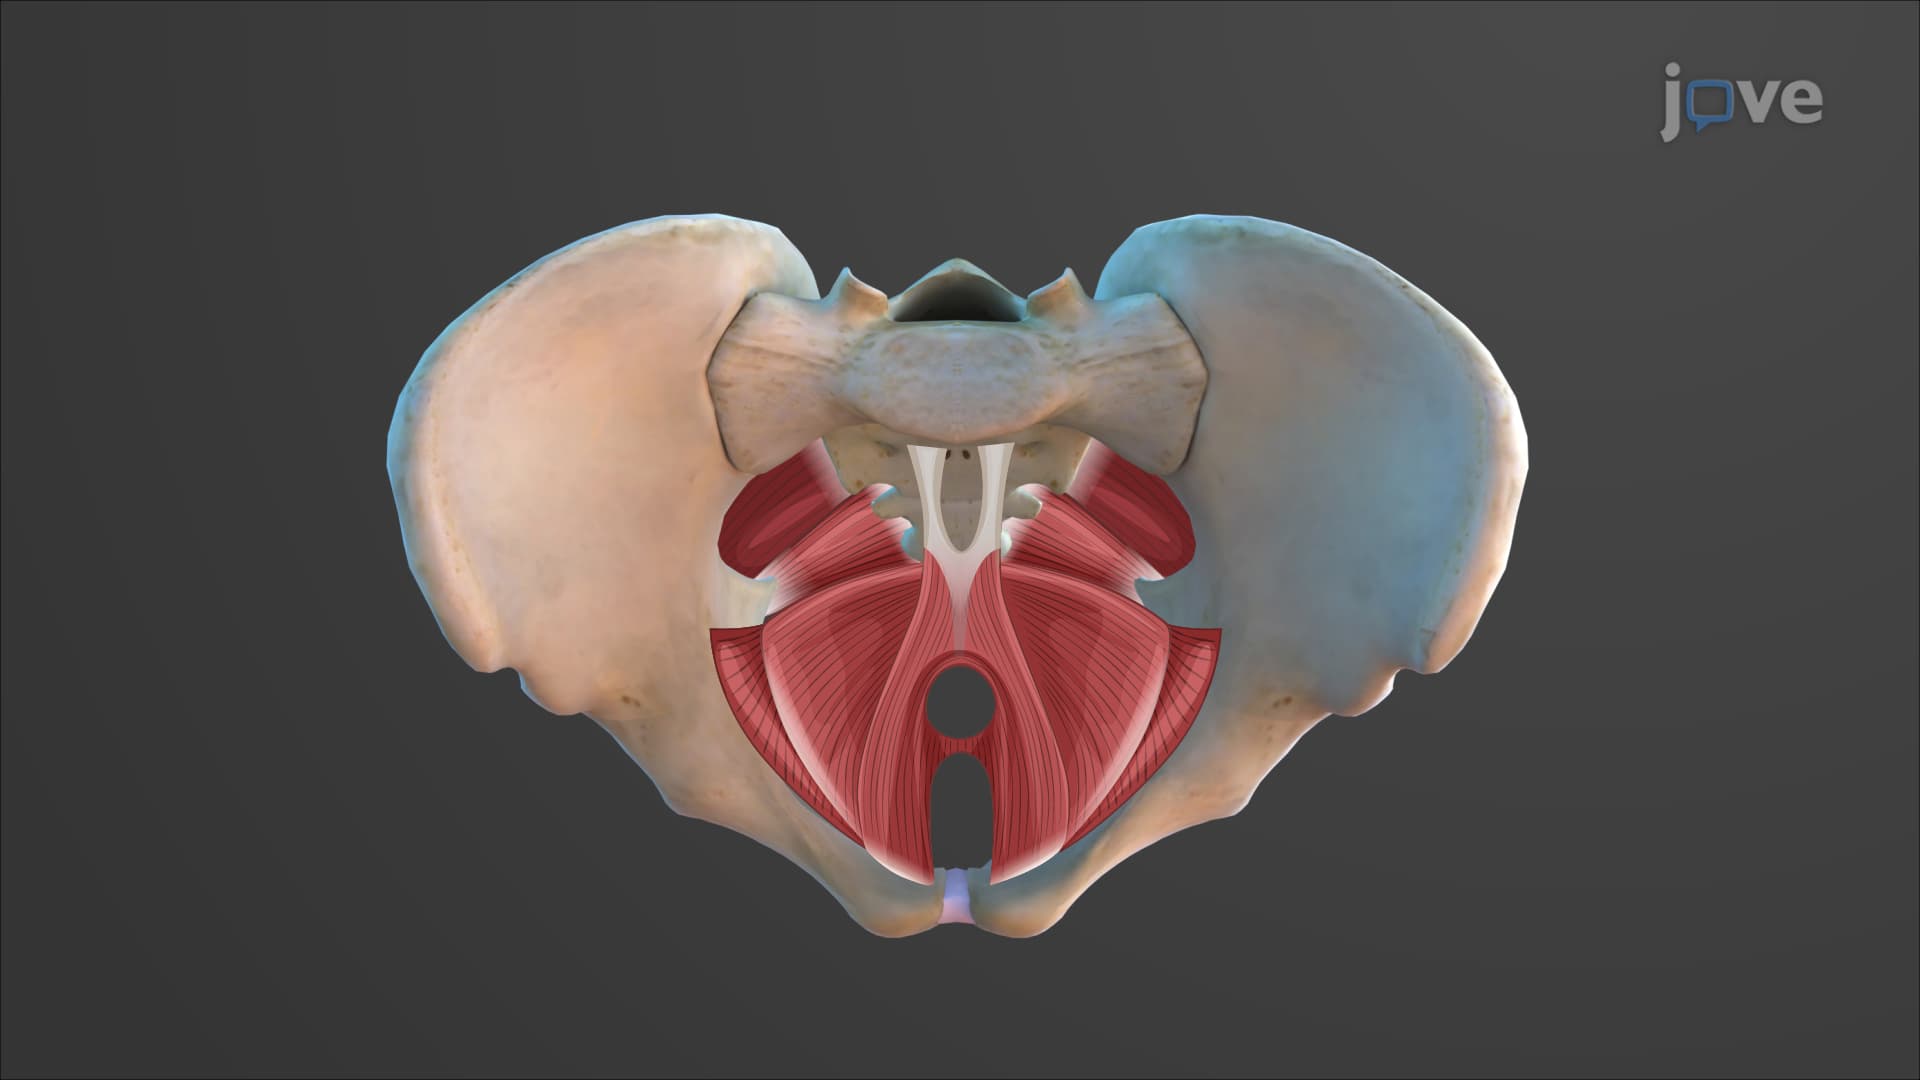
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:18
Uterus and Cervix
The uterus is securely anchored within the pelvic cavity by paired broad ligaments on either side. It is further stabilized by three pairs...
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:21
Muscles of the Abdomen
Anterolateral Region
The anterolateral region comprises five paired muscles classified into the lateral and...