Related Experiment Video
Updated: Aug 24, 2025
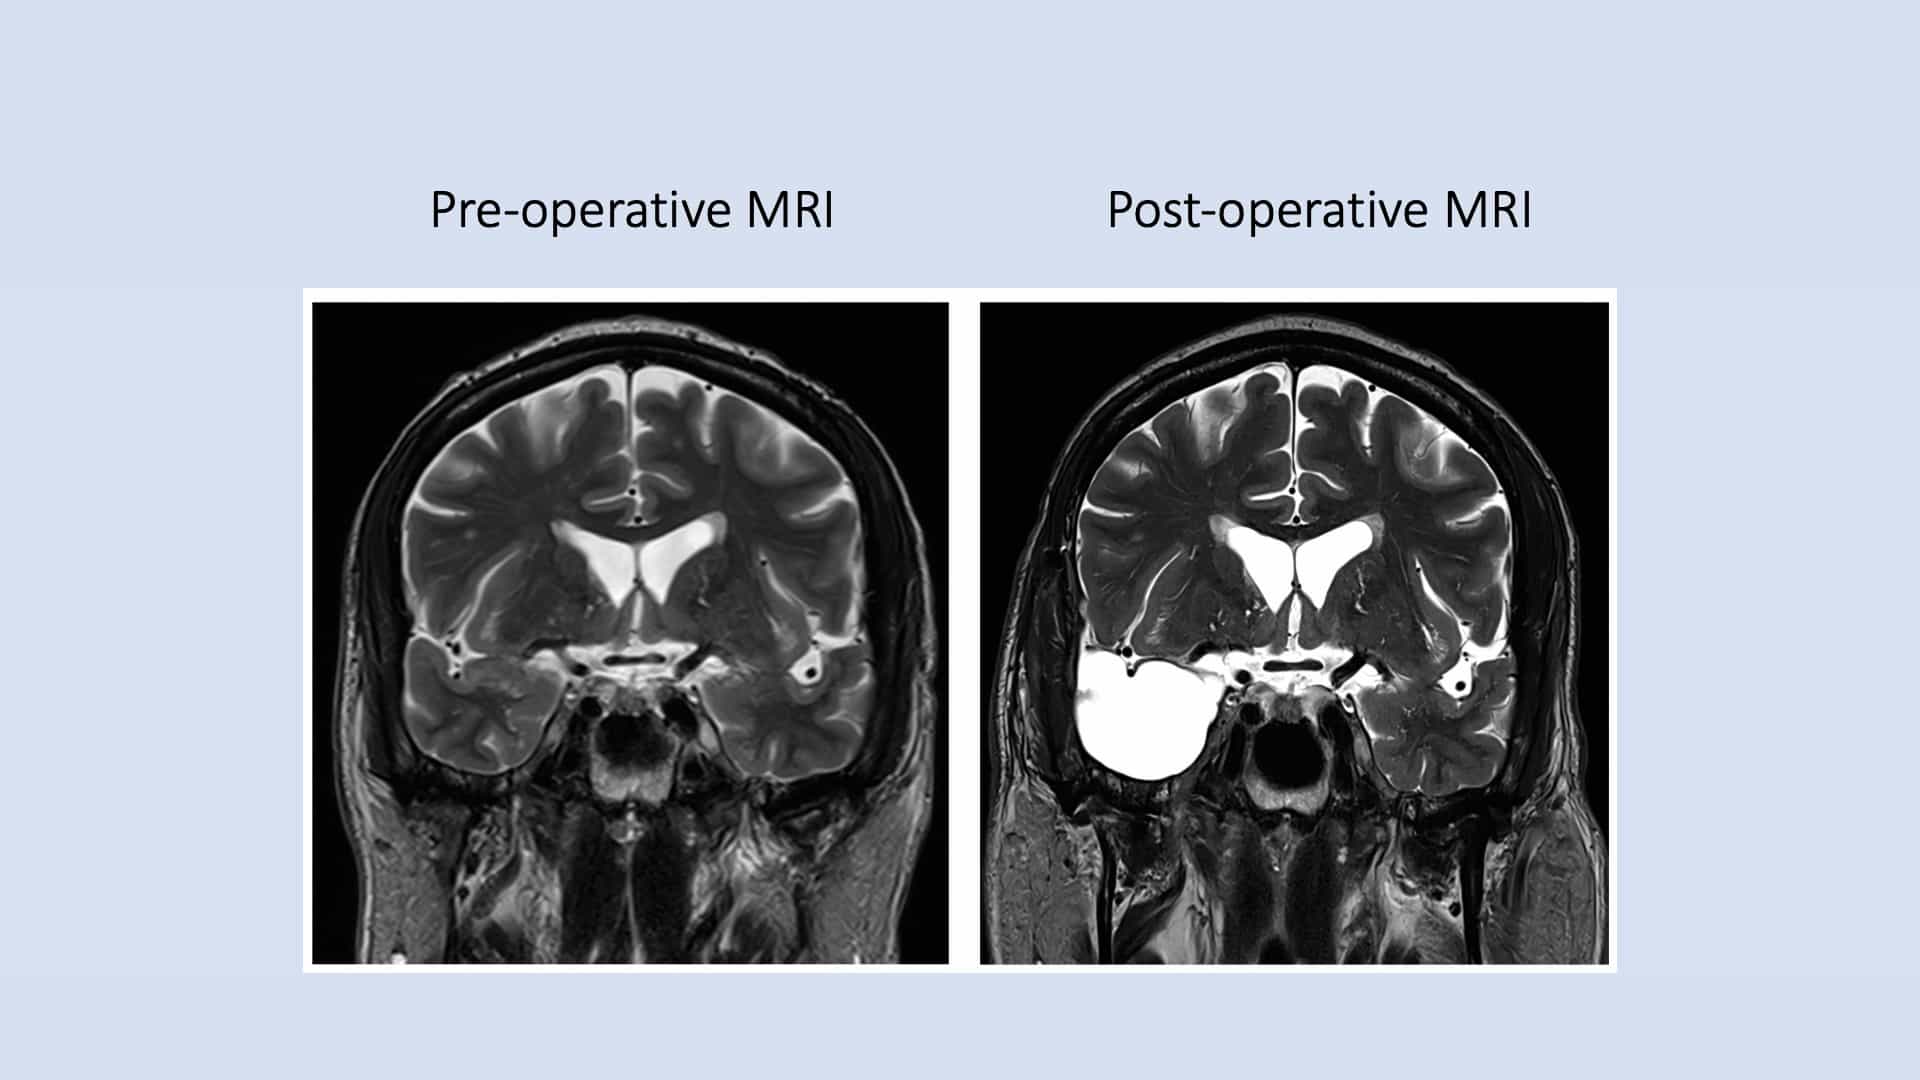

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Predictors of outcomes after surgery for medically intractable insular epilepsy: A systematic review and individual
Sami Obaid1,2, Jia-Shu Chen3, George M Ibrahim4
1Division of Pediatric Neurosurgery, Department of Surgery, Sainte Justine Hospital, University of Montreal, Quebec, Montreal, Canada.

Abstract:
Insular epilepsy (IE) is an increasingly recognized cause of drug-resistant epilepsy amenable to surgery. However, concerns of suboptimal seizure control and permanent neurological morbidity hamper widespread adoption of surgery for IE. We performed a systematic review and individual participant data meta-analysis to determine the efficacy and safety profile of surgery for IE and identify predictors of outcomes. Of 2483 unique citations, 24 retrospective studies reporting on 312 participants were eligible for inclusion. The median follow-up duration was 2.58 years (range, 0-17 years), and 206 (66.7%) patients were seizure-free at last follow-up. Younger age at surgery (≤18 years; HR = 1.70, 95% CI = 1.09-2.66, P = .022) and invasive EEG monitoring (HR = 1.97, 95% CI = 1.04-3.74, P = .039) were significantly associated with shorter time to seizure recurrence. Performing MR-guided laser ablation or radiofrequency ablation instead of open resection (OR = 2.05, 95% CI = 1.08-3.89, P = .028) was independently associated with suboptimal or poor seizure outcome (Engel II-IV) at last follow-up. Postoperative neurological complications occurred in 42.5% of patients, most commonly motor deficits (29.9%). Permanent neurological complications occurred in 7.8% of surgeries, including 5% and 1.4% rate of permanent motor deficits and dysphasia, respectively. Resection of the frontal operculum was independently associated with greater odds of motor deficits (OR = 2.75, 95% CI = 1.46-5.15, P = .002). Dominant-hemisphere resections were independently associated with dysphasia (OR = 13.09, 95% CI = 2.22-77.14, P = .005) albeit none of the observed language deficits were permanent. Surgery for IE is associated with a good efficacy/safety profile. Most patients experience seizure freedom, and neurological deficits are predominantly transient. Pediatric patients and those requiring invasive monitoring or undergoing stereotactic ablation procedures experience lower rates of seizure freedom. Transgression of the frontal operculum should be avoided if it is not deemed part of the epileptogenic zone. Well-selected candidates undergoing dominant-hemisphere resection are more likely to exhibit transient language deficits; however, the risk of permanent deficit is very low.
Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:30
Psychosurgery
Historical Development of Psychosurgery
In the 1930s, Portuguese neurologist Antonio Egas Moniz introduced a surgical procedure designed...