Related Experiment Video
Updated: Aug 23, 2025
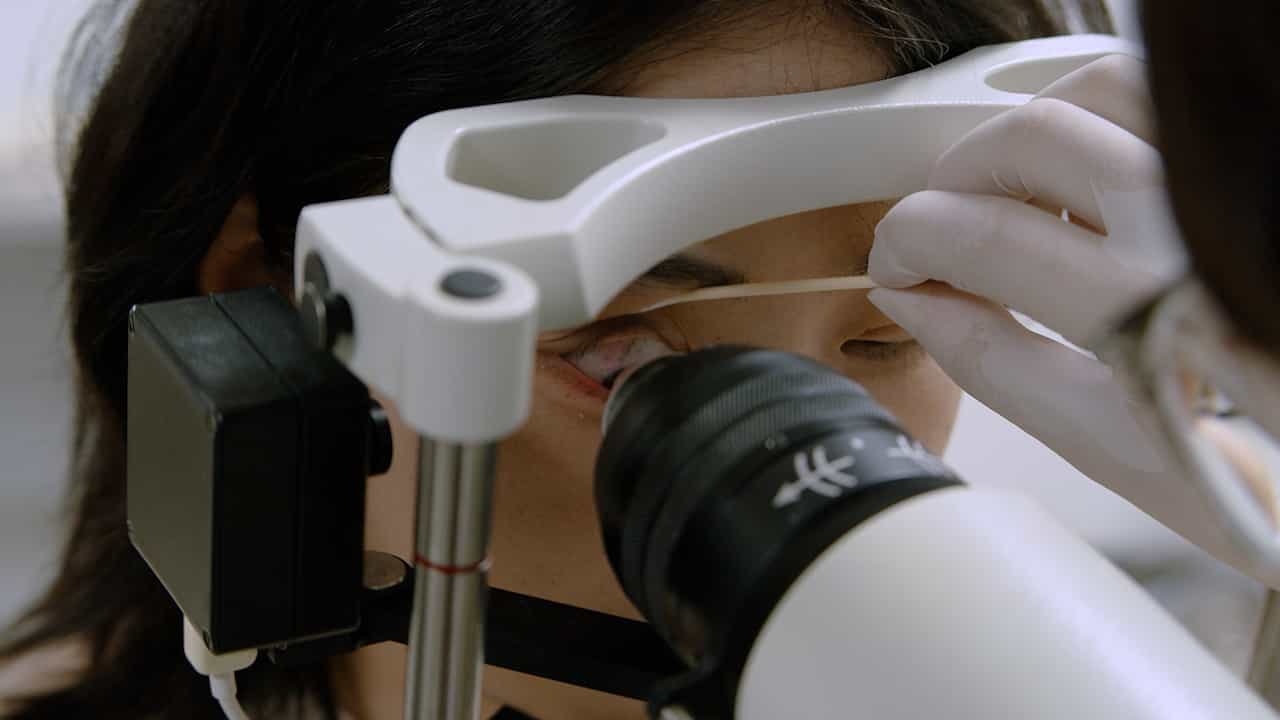

In Vivo Confocal Microscopy: A Standard Operating Procedure for The Detection of Demodex Mites at The Eyelid Margin
Published on: July 3, 2025
Comparison of Different Anti-Demodex Strategies: A Systematic Review and Meta-Analysis
Jiahua Li1, Erdong Wei2, Amin Reisinger2
1Department of Dermatology and Allergy, University Hospital of Munich (LMU), Munich, Germany, jiahuali899@gmail.com.

Background:
Demodex mites are related to some inflammatory diseases such as rosacea and blepharitis and could be harmful in patients with immunodeficiency or immunosuppression, especially notable in patients using biologic like dupilumab. In order to have an objective observation of different anti-Demodex strategies, we conducted this study, based on interventional clinical evidence with quantified Demodex mite data.
Methods:
We used the PubMed, Embase, ClinicalTrials.gov, Medline, and International Clinical Trials Registry Platform (ICTRP) as databases. To assess the risk of bias, the RoB2 and ROBINS-I tools were used. The certainty of evidence was assessed following the GRADE guideline. Furthermore, the effect sizes (ESs) of different strategies were compared in different time periods (0-1, 1-2, 2-3, >3 months), as well as Demodex decrease rates.
Results:
1,618 studies were identified in the databases, with 21 of which included in the final quantitative synthesis. Interventions in these studies included ivermectin, tea tree oil (TTO), permethrin, crotamiton, metronidazole, light therapies, combined therapies, and other therapies. During 0-1 month, the ES varied from 0.07 (cleanser) to 1.95 (systemic ivermectin-metronidazole). During 1-2 months, the ES varied from 0.88 (topical permethrin) to 4.40 (topical ivermectin). During 2-3 months, the ES varied from 0.79 (topical permethrin) to 8.37 (topical ivermectin). During the time of 3 months, the ES varied from 0.59 (topical permethrin) to 2.25 (intense pulsed light [IPL]). In terms of Demodex decrease rates, topical ivermectin, TTO, permethrin, IPL, and baby shampoo had achieved a nearly 100% decrease. The reported adverse events were mostly mild, without severe adverse events reported in any of the studies.
Conclusions:
We found ivermectin (topical and systemic), ivermectin-metronidazole (topical), and TTO (topical) are promising anti-Demodex interventions. In addition to traditional pharmacotherapy, light therapies, especially IPL and skin cleansing, could also be considered as effective methods to control Demodex mite infestation.