Related Experiment Video
Updated: Aug 23, 2025

A Murine Model of Fetal Exposure to Maternal Inflammation to Study the Effects of Acute Chorioamnionitis on Newborn Intestinal Development
Published on: June 24, 2020
Effects of prophylactic indomethacin on morbidity and mortality in infants <25 weeks' gestation: a protocol driven
Ronald I Clyman1,2, Nancy K Hills3,4
1Department of Pediatrics, University of California San Francisco, San Francisco, CA, USA. clymanr@peds.ucsf.edu.

Insights
Prophylactic indomethacin (PINDO) did not reduce death or bronchopulmonary dysplasia in extremely preterm infants. This study found no significant differences in primary or secondary outcomes between PINDO and expectant management for patent ductus arteriosus.
Area of Science:
- Neonatal Medicine
- Pediatric Cardiology
- Perinatal Research
Background:
- Patent ductus arteriosus (PDA) is common in extremely preterm infants (<25 weeks).
- PDA is associated with significant morbidities, including death and bronchopulmonary dysplasia (BPD).
- Prophylactic indomethacin (PINDO) is a potential intervention to manage PDA.
Purpose of the Study:
- To evaluate the efficacy of prophylactic indomethacin (PINDO) in reducing death or severe bronchopulmonary dysplasia (BPD grades 2 and 3) in infants born at <25 weeks gestation.
- To assess the impact of PINDO on secondary outcomes such as BPD, death, necrotizing enterocolitis, and intraventricular hemorrhage.
Main Methods:
- An intention-to-treat, cohort-controlled study involving 106 infants.
- Infants were admitted during alternating epochs of PINDO administration or expectant patent ductus arteriosus (PDA) management.
- Outcomes were compared between infants born during PINDO epochs and those born during expectant management epochs.
Main Results:
- PINDO significantly reduced the incidence of PDA at 7-8 days (24% vs. 85% in expectant management).
- However, there were no significant differences in the primary outcome (death/BPD grades 2-3) between the PINDO and expectant management groups.
- Secondary outcomes, including BPD, death, necrotizing enterocolitis, and intraventricular hemorrhage, also showed no significant differences between the groups.
Conclusions:
- Prophylactic indomethacin (PINDO) did not demonstrate a significant benefit in reducing death or severe bronchopulmonary dysplasia in infants <25 weeks.
- Despite effectively reducing PDA at 7-8 days, PINDO did not alter the rates of key primary and secondary morbidities.
- Further research may be needed to explore alternative strategies for managing PDA in extremely preterm infants.
Objective:
To determine if prophylactic indomethacin (PINDO) decreases death or bronchopulmonary dysplasia-grades 2 and 3 (death/BPD) in newborns <25 weeks.
Study Design:
Intention-to-treat, cohort-controlled study of 106 infants admitted during three alternating epochs of PINDO or Expectant patent ductus arteriosus (PDA) management.
Results:
At 7-8 days 85% of Expectant Management epoch infants had a moderate/large PDA (median exposure was 23 days). Among PINDO epoch infants only 24% still had a PDA at 7-8 days. There were no significant differences in the incidence of death/BPD or of secondary outcomes (BPD, death, necrotizing enterocolitis/spontaneous perforations, or intraventricular hemorrhage (grades 3 or 4)) in either unadjusted or adjusted comparisons between infants born in a PINDO epoch and those born in the Expectant Management epoch.
Conclusion:
Despite being at high risk for PDA-related morbidities, PINDO did not appear to alter the rates of our primary and secondary outcomes in infants <25 weeks.


Related Concept Videos
 01:07
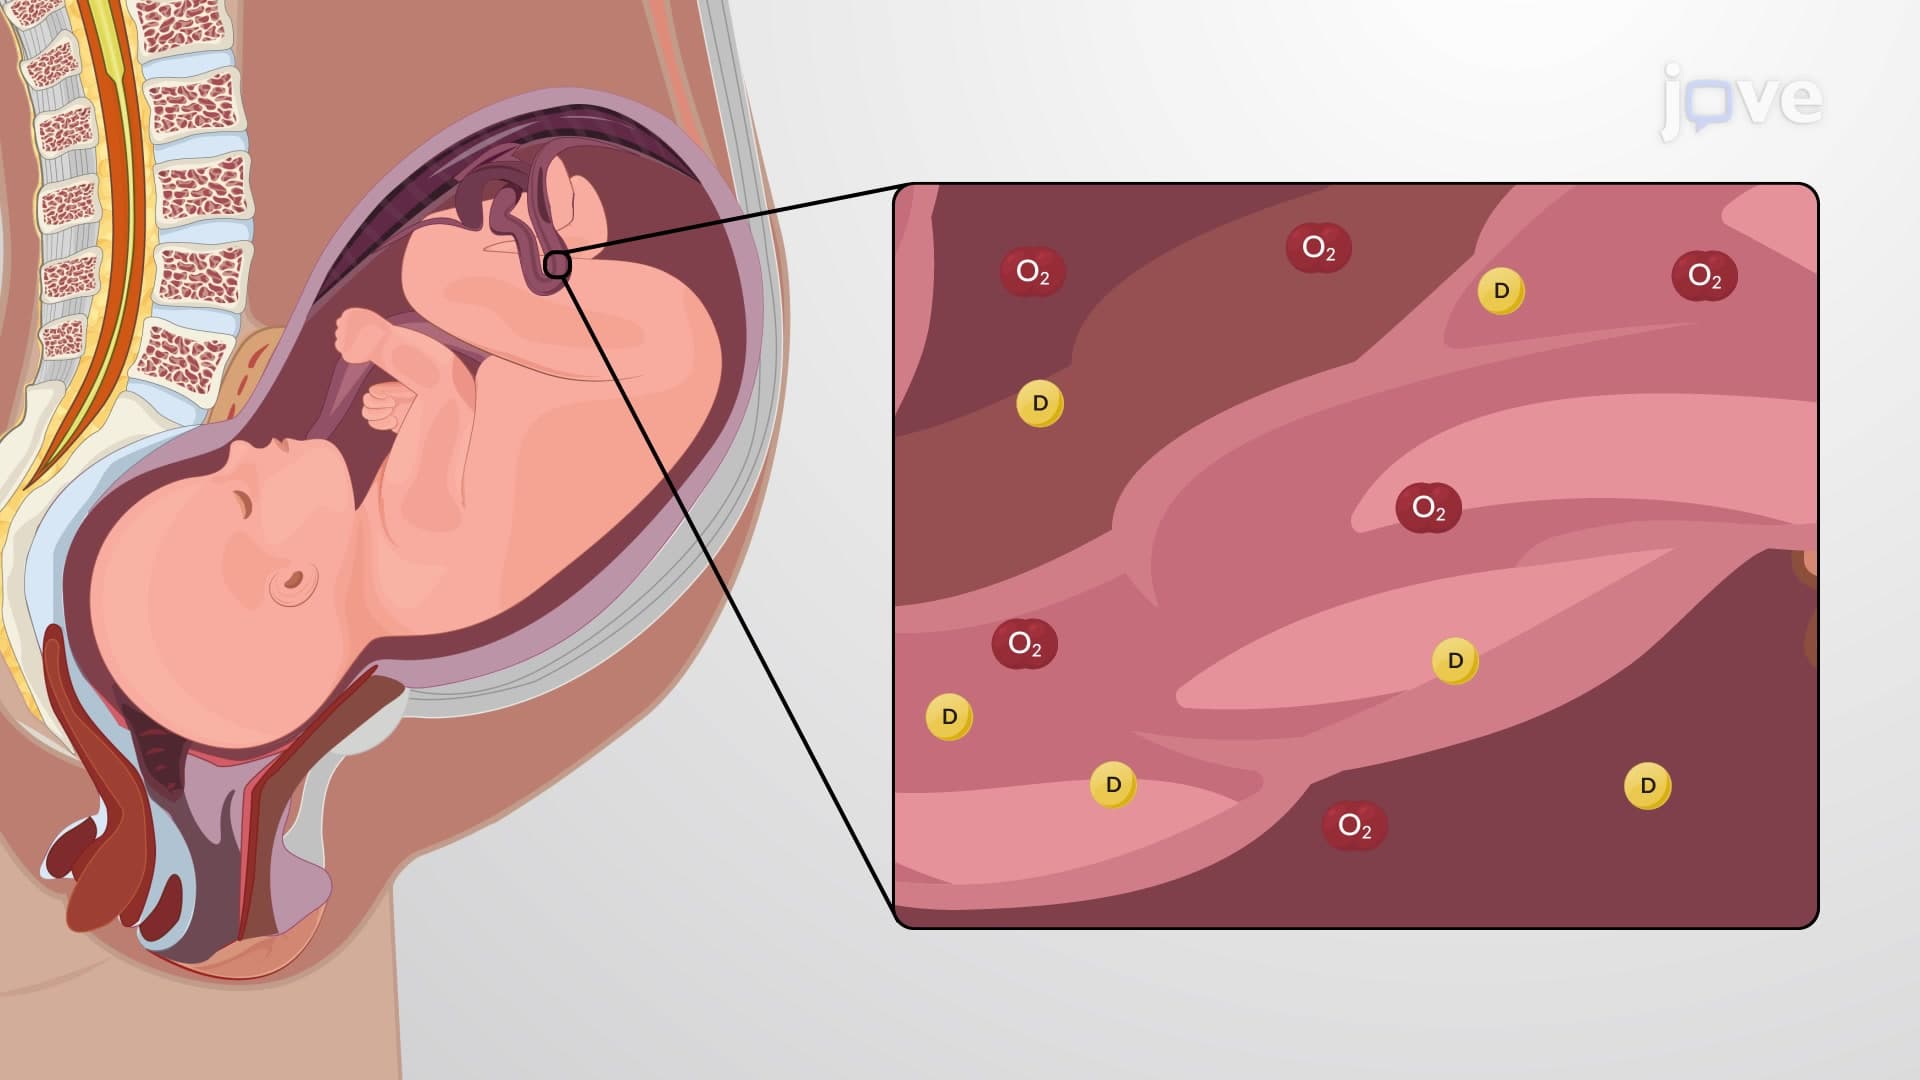
Teratogenicity
 01:21
Factors Affecting Drug Response: Overview
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...