Related Experiment Video
Updated: Aug 23, 2025

Echocardiographic Evaluation of Atrial Communications before Transcatheter Closure
Published on: February 8, 2022
Case report: Conquer a complex variant: Coronary-pulmonary artery fistulas, atrial septal defect and bicuspid
Ting Zhou1, Chaobing Liu2, Songlin Zhang2
1Department of Cardiothoracic Surgery, The First College of Clinical Medical Science, China Three Gorges University, Yichang, China.

Insights
This case report details a rare coronary artery to pulmonary artery fistula (CPAF) detected and repaired using on-pump beating-heart surgery (OPBHS). This innovative approach offers a myocardial protection strategy for patients with complex cardiovascular conditions.
Area of Science:
- Cardiovascular Surgery
- Congenital Heart Disease
- Cardiac Imaging
Background:
- Coronary artery to pulmonary artery fistula (CPAF) is an abnormal connection between the coronary arteries and the pulmonary artery, potentially causing serious cardiac complications.
- Diagnosis typically relies on coronary angiography, but alternative methods are explored for specific patient populations.
- This report focuses on a unique case involving multiple CPAFs and coexisting congenital heart defects.
Observation:
- A 39-year-old male presented with atrial septal defect (ASD), bicuspid pulmonary valve, and moderate tricuspid regurgitation (TR).
- Echocardiography suggested significant CPAF, but the patient declined coronary angiography due to an allergy.
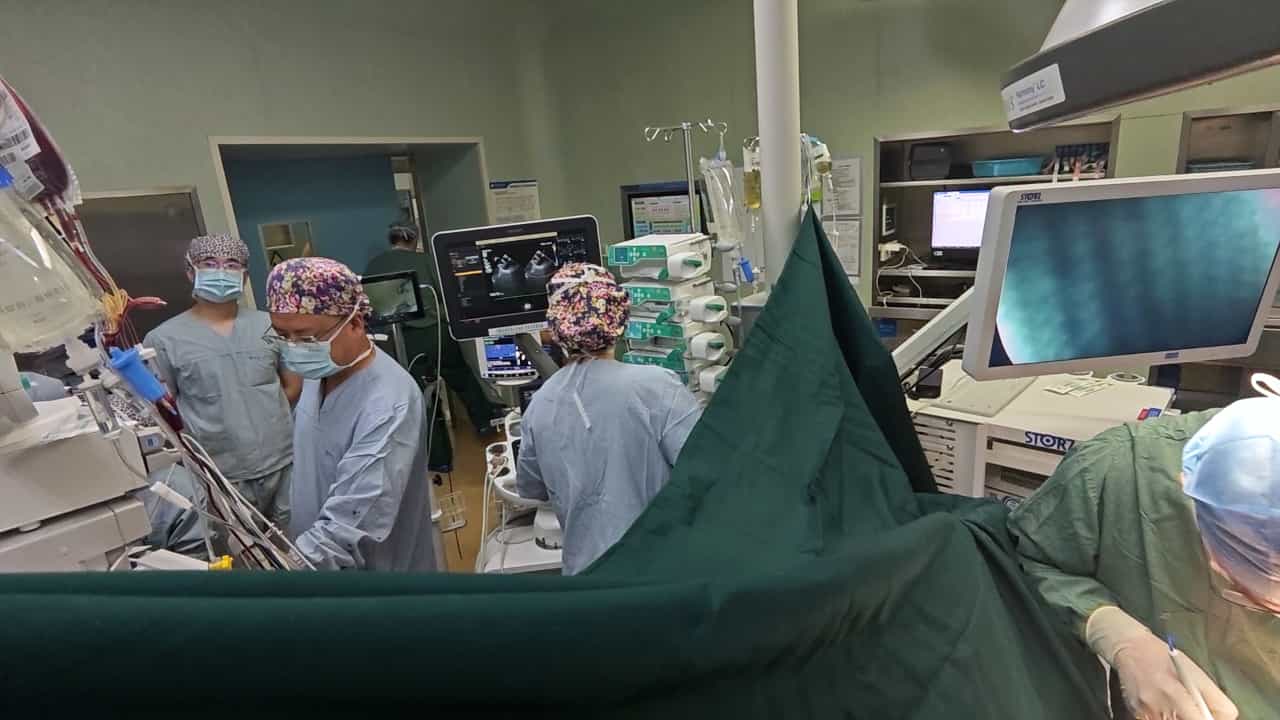
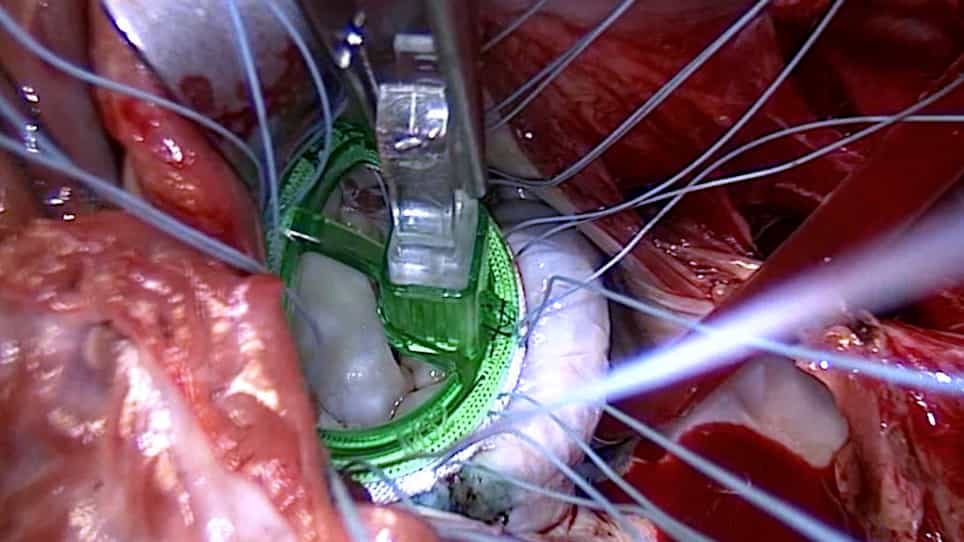
- On-pump beating-heart surgery (OPBHS) was employed for diagnosis and repair due to the patient's low surgical risk and allergy history.
Findings:
- A rare and complex case of CPAFs originating from two branches of the left anterior descending coronary artery (LAD) to the main pulmonary artery (MPA) was successfully identified and managed.
- The surgical intervention also addressed the coexisting ASD, bicuspid pulmonary valve, and moderate TR.
- This represents a novel application of OPBHS for diagnosing and treating complex CPAF.
Implications:
- On-pump beating-heart surgery (OPBHS) can serve as a viable myocardial protection strategy and diagnostic tool for complex CPAF in select patients.
- This case expands the understanding of CPAF management, particularly in patients with contraindications to conventional diagnostic methods.
- Further analysis of the embryological origins of such complex CPAFs is warranted.
Abstract:
Coronary artery to pulmonary artery fistula (CPAF) is a congenital or acquired abnormal channel between arteries, with a left-to-right cardiac shunting, which may lead to myocardial ischemia, arrhythmia, thrombotic complications, and heart failure. CPAF is usually detected by coronary angiography but few reports have used beating-heart surgery as a detection method. The patient in this case report is a 39-year-old male diagnosed with atrial septal defect (ASD), bicuspid pulmonary valve, and moderate tricuspid regurgitation (TR). He is asymptomatic. In preoperative evaluation, significant CPAF was suspected using echocardiography. The patient refused coronary angiography due to allergic history. Therefore, the cardiac team designed and performed on-pump beating-heart surgery (OPBHS) to detect and repair these disorders, and suggested OPBHS as a myocardial protection strategy for the patient at low surgical risk. A rare and complex cardiovascular case with CPAFs from two branches of the left anterior descending coronary (LAD) artery to the main pulmonary artery (MPA) with ASD, bicuspid pulmonary valve, and moderate TR has not yet been reported in the literature, and its embryological hypothesis has been further analyzed in this report.