Related Experiment Video
Updated: Aug 23, 2025
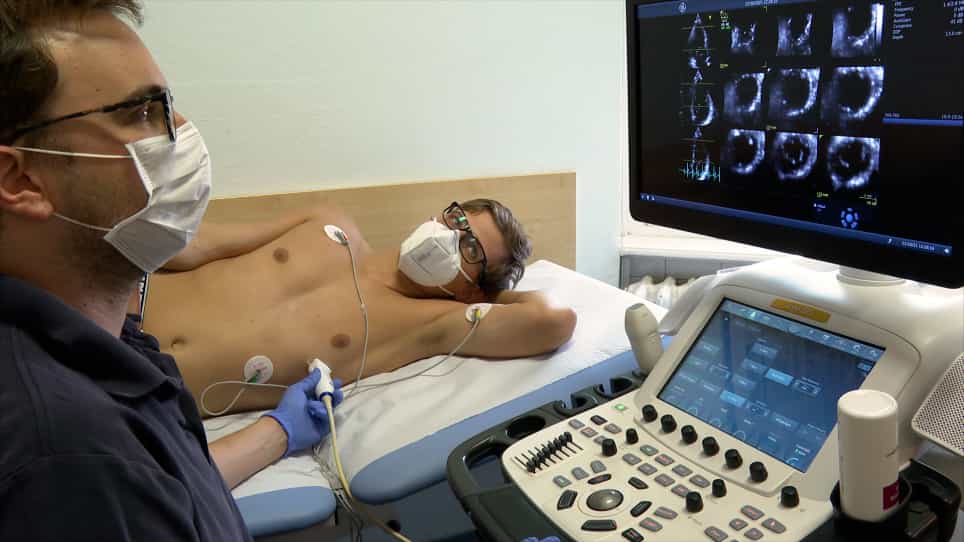

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Cardiac MRI Risk Stratification for Dilated Cardiomyopathy with Left Ventricular Ejection Fraction of 35% or Higher
Shuang Li1, Yining Wang1, Wenjing Yang1
1From the Department of Magnetic Resonance Imaging (S.L., Y.W., W.Y., D.Z., B.Z., J.X., J.H., G.Y., S.Z., M.L.), Cardiac Arrhythmia Center (X.F.), and Department of Echocardiography (W.W.), Fuwai Hospital, State Key Laboratory of Cardiovascular Disease, National Center for Cardiovascular Diseases, Chinese Academy of Medical Sciences and Peking Union Medical College, No. 167 Beilishi Rd, Beijing 100037, China; Department of Medicine, Saint James School of Medicine, Park Ridge, Ill (P.S.); Department of Health and Human Services, Radiology and Imaging Sciences, National Institutes of Health, Bethesda, Md (A.S.); Kensington, Md (A.E.A.); and Key Laboratory of Cardiovascular Imaging (Cultivation), Chinese Academy of Medical Sciences, Beijing, China (G.Y., W.W., M.L.).

Insights
Patients with dilated cardiomyopathy and preserved ejection fraction face risks of sudden cardiac death. Cardiac MRI showing significant myocardial scar (≥7.1% LV mass) predicts these adverse events.
Area of Science:
- Cardiology
- Medical Imaging
- Cardiovascular Disease
Background:
- Dilated cardiomyopathy (DCM) patients with left ventricular ejection fraction (LVEF) ≥35% are at risk for sudden cardiac death (SCD).
- Previous studies indicate a notable number of DCM patients who died from SCD had LVEF ≥35%.
- Identifying risk factors in this specific patient group is crucial for improved management.
Purpose of the Study:
- To determine clinical and cardiac magnetic resonance imaging (MRI) risk factors for adverse events.
- Focus on patients diagnosed with dilated cardiomyopathy and LVEF of 35% or higher.
- Identify predictors for sudden cardiac death (SCD) or aborted SCD, and secondary outcomes.
Main Methods:
- Retrospective analysis of 466 DCM patients with LVEF ≥35% who underwent cardiac MRI.
- Primary endpoint: composite of SCD or aborted SCD.
- Secondary endpoint: composite of all-cause mortality, heart transplant, or hospitalization for heart failure. Multivariable Cox analysis used for risk factor identification.
Main Results:
- During a mean follow-up of 79 months, 40 patients experienced the primary endpoint and 61 the secondary endpoint.
- Adjusted analysis revealed age, family history of SCD, NYHA class III/IV, and myocardial scar (LGE ≥7.1% LV mass) predicted SCD or aborted SCD.
- For the secondary endpoint, LGE ≥7.1% LV mass, left atrial volume index, and reduced global longitudinal strain were independent predictors.
Conclusions:
- Cardiac MRI-detected myocardial scar, specifically ≥7.1% of LV mass, is a significant predictor of SCD or aborted SCD in DCM patients with LVEF ≥35%.
- Clinical factors like age, family history of SCD, and NYHA class also contribute to risk stratification.
- These findings highlight the importance of cardiac MRI for risk assessment in DCM patients with preserved LVEF.
Abstract:
Background Studies over the past 15 years have demonstrated that a considerable number of patients with dilated cardiomyopathy (DCM) who died from sudden cardiac death (SCD) had a left ventricular (LV) ejection fraction (LVEF) of 35% or higher. Purpose To identify clinical and cardiac MRI risk factors for adverse events in patients with DCM and LVEF of 35% or higher. Materials and Methods In this retrospective study, consecutive patients with DCM and LVEF of 35% or higher who underwent cardiac MRI between January 2010 and December 2017 were included. The primary end point was a composite of SCD or aborted SCD. The secondary end point was a composite of all-cause mortality, heart transplant, or hospitalization for heart failure. The risk factors for the primary and secondary end points were identified with multivariable Cox analysis. Results A total of 466 patients with DCM and LVEF of 35% or higher (mean age, 44 years ± 14 [SD]; 358 men) were included. During a mean follow-up of 79 months ± 30 (SD) (range, 7-143 months), 40 patients reached the primary end point and 61 reached the secondary end point. In the adjusted analysis, age (hazard ratio [HR], 1.03 per year [95% CI: 1.00, 1.05]; P = .04), family history of SCD (HR, 3.4 [95% CI: 1.3, 8.8]; P = .01), New York Heart Association (NYHA) class III or IV (HR vs NYHA class I or II, 2.1 [95% CI: 1.1, 3.9]; P = .02), and myocardial scar at late gadolinium enhancement (LGE) MRI greater than or equal to 7.1% of the LV mass (HR, 4.4 [95% CI: 2.4, 8.3]; P < .001) were associated with SCD or aborted SCD. For the composite secondary end point, LGE greater than or equal to 7.1% of the LV mass (HR vs LGE <7.1%, 2.0 [95% CI: 1.2, 3.4]; P = .01), left atrial maximum volume index, and reduced global longitudinal strain were independent predictors. Conclusion For patients with dilated cardiomyopathy and left ventricular (LV) ejection fraction of 35% or higher, cardiac MRI-defined myocardial scar greater than or equal to 7.1% of the LV mass was associated with sudden cardiac death (SCD) or aborted SCD. © RSNA, 2022 Online supplemental material is available for this article.
More Related Videos
 11:13
Quantification of Mouse Heart Left Ventricular Function, Myocardial Strain, and Hemodynamic Forces by Cardiovascular Magnetic Resonance Imaging
Published on: May 24, 2021
 08:13
In Vivo Quantitative Assessment of Myocardial Structure, Function, Perfusion and Viability Using Cardiac Micro-computed Tomography
Published on: February 16, 2016
Related Concept Videos
 01:21
Imaging Studies for Cardiovascular System IV: CMRI
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy