Related Experiment Video
Updated: Aug 23, 2025

Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment RMCA in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
Agreement between two methods for assessment of maximal inspiratory pressure in patients weaning from mechanical
Emanuelle Olympia Silva Ribeiro1, Rik Gosselink2, Lizandra Eveline da Silva Moura3
1Postgraduate Program in Physiotherapy, Federal University of Pernambuco, Recife, Brazil.

Background:
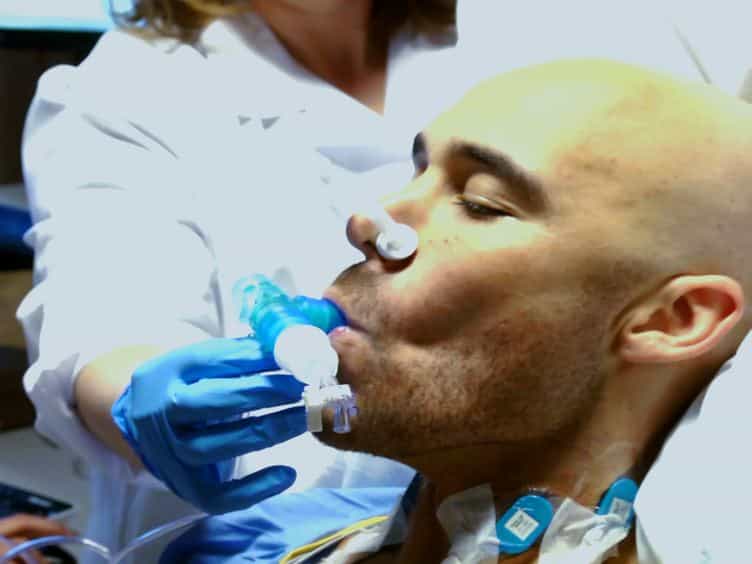
Respiratory muscle strength in patients with an artificial airway is commonly assessed as the maximal inspiratory pressure (MIP) and is measured using analogue or digital manometers. Recently, new electronic loading devices have been proposed to measure respiratory muscle strength. This study evaluates the agreement between the MIPs measured by a digital manometer and those according to an electronic loading device in patients being weaned from mechanical ventilation.
Methods:
In this prospective study, the standard MIP was obtained using a protocol adapted from Marini, in which repetitive inspiratory efforts were performed against an occluded airway with a one-way valve and were recorded with a digital manometer for 40 seconds (MIPDM). The MIP measured using the electronic loading device (MIPELD) was obtained from repetitively tapered flow resistive inspirations sustained for at least 2 seconds during a 40-second test. The agreement between the results was verified by a Bland-Altman analysis.
Results:
A total of 39 subjects (17 men, 55.4±17.7 years) was enrolled. Although a strong correlation between MIPDM and MIPELD (R=0.73, P<0.001) was observed, the Bland-Altman analysis showed a high bias of -47.4 (standard deviation, 22.3 cm H2O; 95% confidence interval, -54.7 to -40.2 cm H2O).
Conclusions:
The protocol of repetitively tapering flow resistive inspirations to measure the MIP with the electronic loading device is not in agreement with the standard protocol using one-way valve inspiratory occlusion when applied in poorly cooperative patients being weaned from mechanical ventilation.


Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: