The past, present, and future of chemotherapy with a focus on individualization of drug dosing
Louis DeRidder1, Douglas A Rubinson2, Robert Langer3
1Harvard-MIT Division of Health Science Technology, Massachusetts Institute of Technology, Cambridge, MA, USA; David H. Koch Institute for Integrative Cancer Research, Massachusetts Institute of Technology, Cambridge, MA, USA; Department of Mechanical Engineering, Massachusetts Institute of Technology, Cambridge, MA, USA.

Abstract:
While there have been rapid advances in developing new and more targeted drugs to treat cancer, much less progress has been made in individualizing dosing. Even though the introduction of immunotherapies such as CAR T-cells and checkpoint inhibitors, as well as personalized therapies that target specific mutations, have transformed clinical treatment of cancers, chemotherapy remains a mainstay in oncology. Chemotherapies are typically dosed on either a body surface area (BSA) or weight basis, which fails to account for pharmacokinetic differences between patients. Drug absorption, distribution, metabolism, and excretion rates can vary between patients, resulting in considerable differences in exposure to the active drugs. These differences result in suboptimal dosing, which can reduce efficacy and increase side-effects. Therapeutic drug monitoring (TDM), genotype guided dosing, and chronomodulation have been developed to address this challenge; however, despite improving clinical outcomes, they are rarely implemented in clinical practice for chemotherapies. Thus, there is a need to develop interventions that allow for individualized drug dosing of chemotherapies, which can help maximize the number of patients that reach the most efficacious level of drug in the blood while mitigating the risks of underdosing or overdosing. In this review, we discuss the history of the development of chemotherapies, their mechanisms of action and how they are dosed. We discuss substantial intraindividual and interindividual variability in chemotherapy pharmacokinetics. We then propose potential engineering solutions that could enable individualized dosing of chemotherapies, such as closed-loop drug delivery systems and bioresponsive biomaterials.

Related Concept Videos
 02:50
Combination Therapies and Personalized Medicine
The combination of the drug acetazolamide and sulforaphane is a good example of combination therapy to treat cancer. The cells in the interior of a large tumor often die due to the hypoxic and...
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against...
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
 01:19
Nonlinear Pharmacokinetics: Overview
Nonlinearity can arise due to the saturation of plasma protein-binding or...
 01:15
Drug Dosage Regimen: Overview
Typically, the starting dose and dosing interval are guided by the manufacturer's recommendations based on clinical trials conducted during and after drug...
 01:20
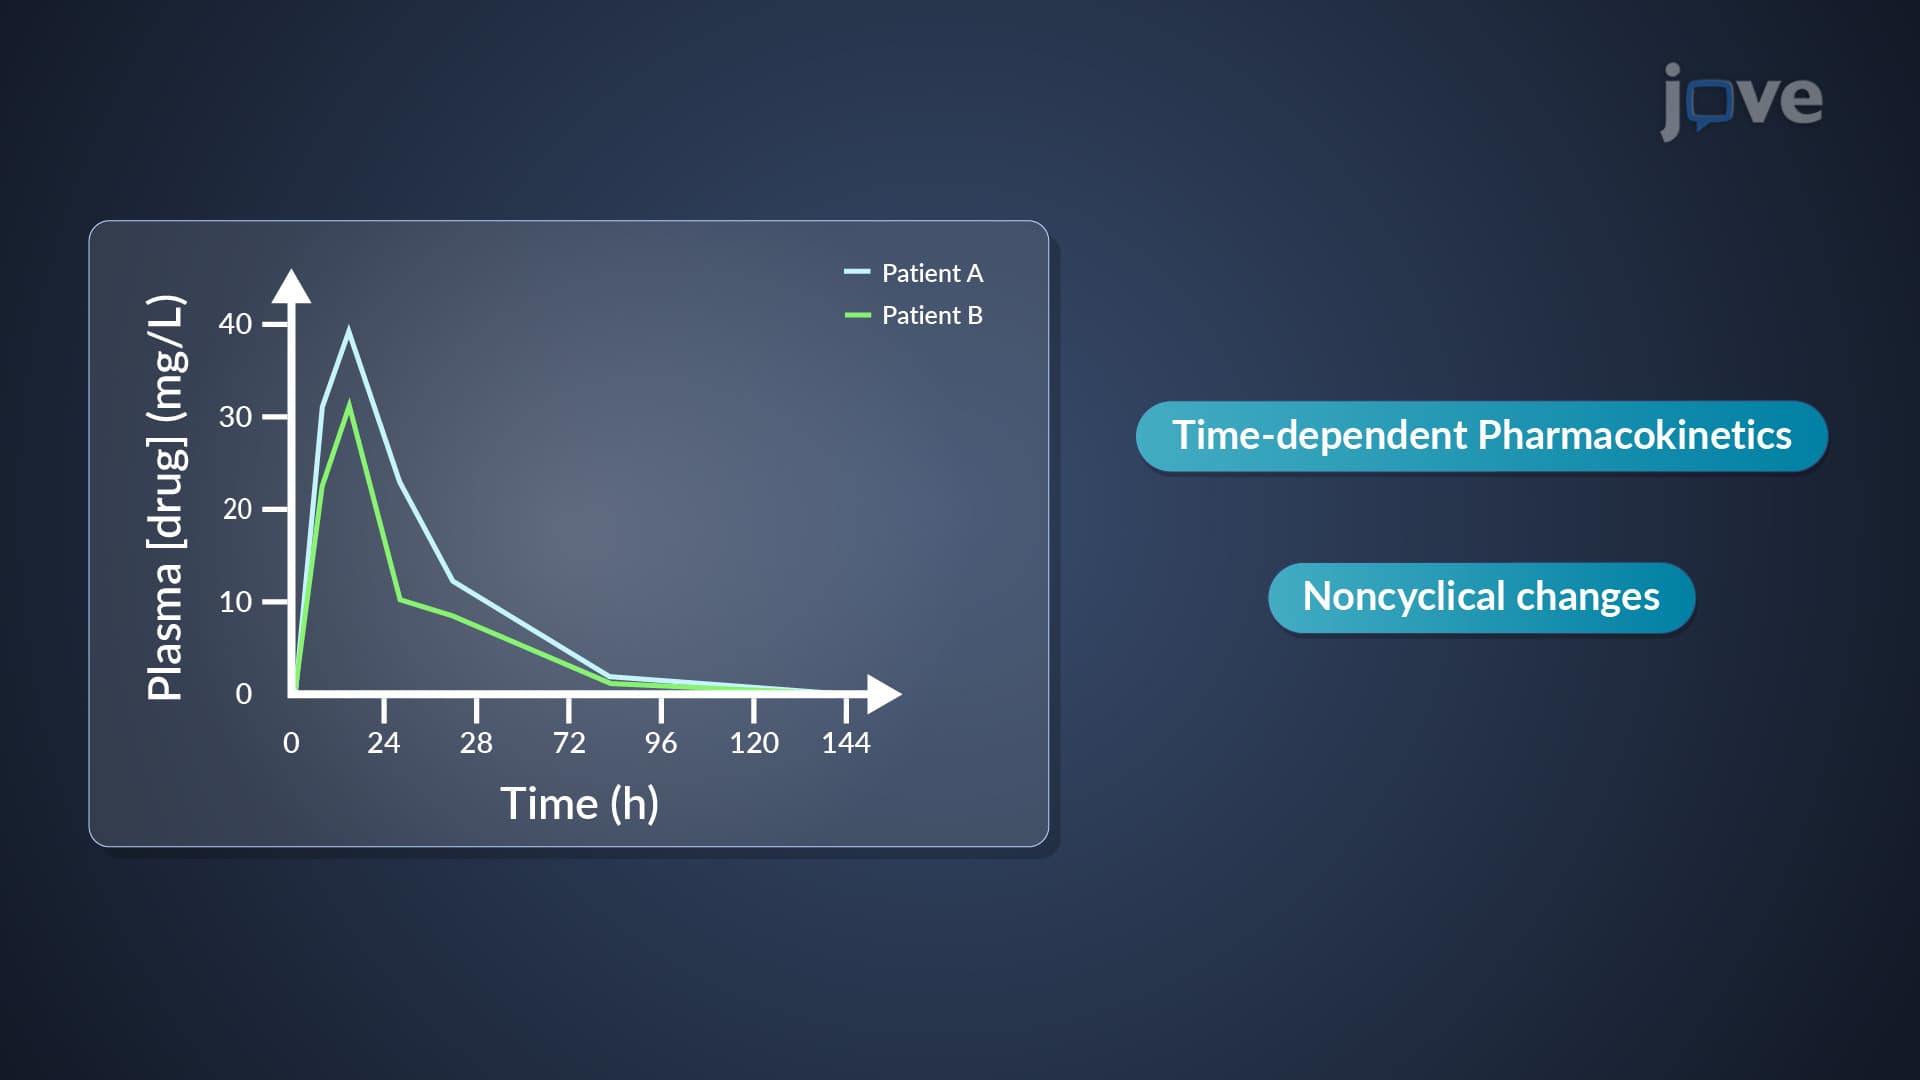
Chronopharmacokinetics: Time-Dependent Pharmacokinetics
Time-dependent pharmacokinetics refers to non-cyclical changes in drug rate processes over a period of time. It can lead to nonlinear pharmacokinetics, where the relationship between drug concentration and time is not proportional. Non-cyclical...