Related Experiment Video
Updated: Aug 22, 2025
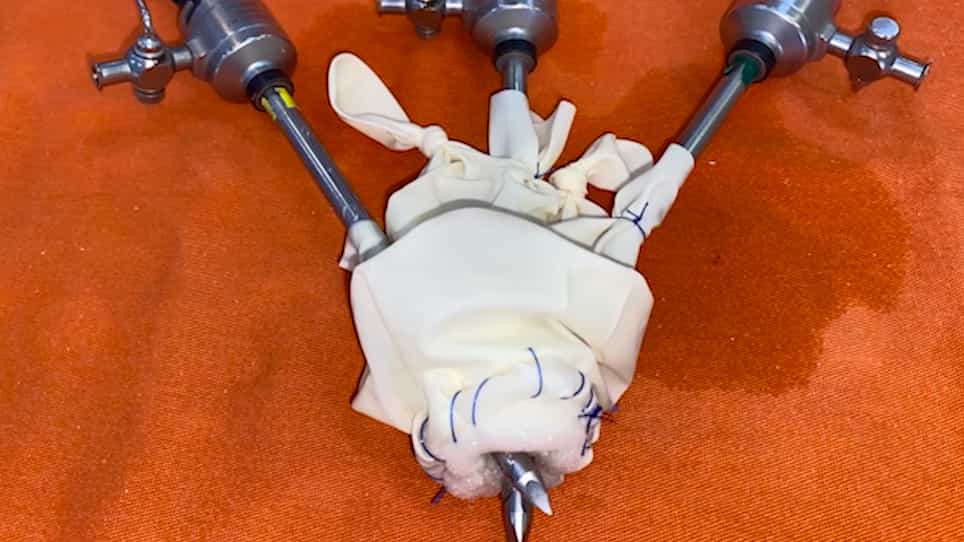
Low-Cost Single-Port LoCoSP Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
A modified tracheal transection approach for cervical esophageal lesion treatment: A report of 13 cases
Yang Liu1, Nan Huang1, Wei Xu2
1Department of Head and Neck Surgical Oncology, National Cancer Center/National Clinical Research Center for Cancer/Cancer Hospital, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing, China.

Background:
Surgical interventions for tumors in the cervical esophageal region are complicated and laryngeal function is frequently sacrificed. Therefore, we attempted the tracheal transection approach to resect the tumor while preserving laryngeal function.
Methods:
Three patients with papillary thyroid cancer (PTC), six with cervical esophageal cancer (CEC), and four with CEC mixed with thoracic esophageal cancer (TEC) were enrolled. The esophagus was exposed after the trachea was transected between the second and third tracheal rings. CEC/TEC: Resection of the esophagus or/and a portion of the hypopharynx with acceptable safety margins and repair with free jejunum or tubular stomach. PTC: Suture the small esophageal incision immediately after removing the tumor. The tracheal dissection was repaired with interrupted sutures throughout the entire layer after the esophageal lesion was resected. The status of the recurrent laryngeal nerve (RLN) determined whether a tracheotomy was necessary.
Results:
All 13 patients had effective esophageal lesion excision, with six of them requiring intraoperative tracheotomy. Postoperative complications included a tracheoesophageal fistula (one case, 7.7%), postoperative RLN paralysis (two cases, 15.4%), and aspiration (three cases, 23.1%). Except for two patients with distant metastases, there was no recurrence in the remaining patients after 5-92 months of follow-up.
Conclusion:
The tracheal transection approach, as a new surgical technique, can retain laryngeal function while ensuring appropriate exposure and satisfactory surgical resection. Before surgery, the feasibility of this approach must be carefully assessed. The RLN should be protected during the procedure. The operation is both safe and effective, with a wide range of applications.


Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...