Related Experiment Video
Updated: Aug 22, 2025
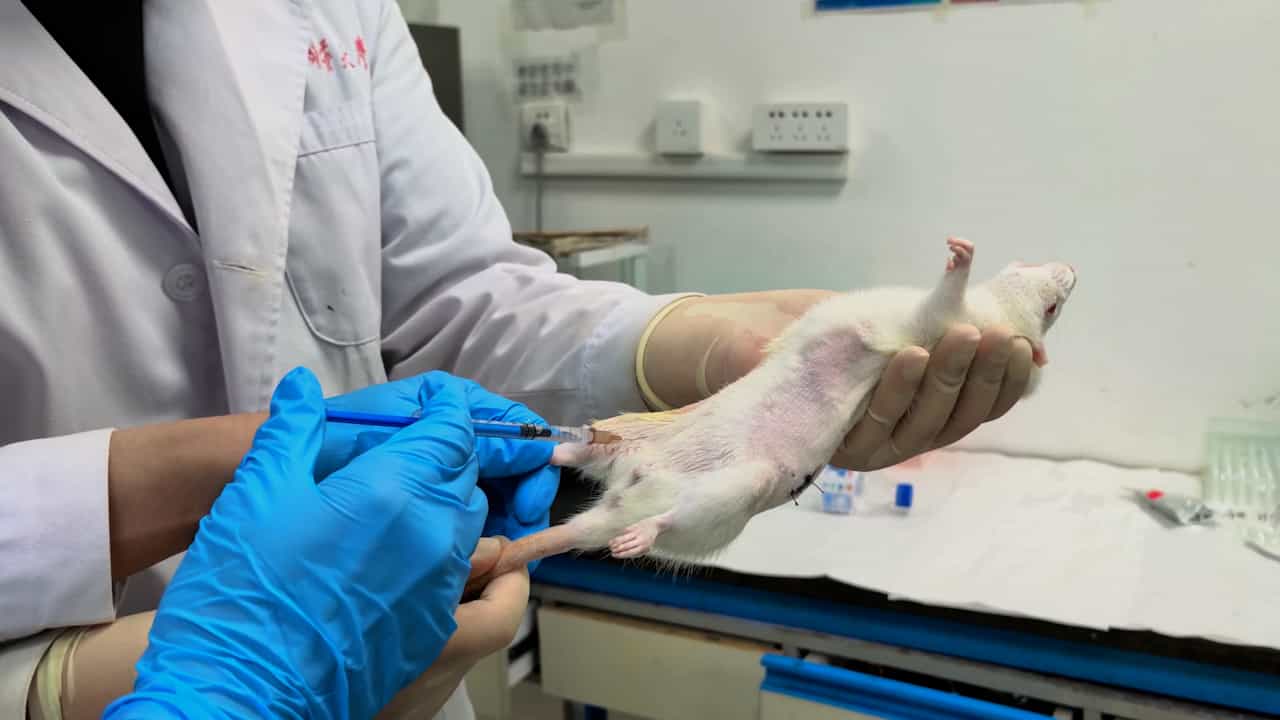

The Creation of a Rat Model for Osteosarcopenia via Ovariectomy
Published on: February 21, 2025
Clinical Outcomes and Prevalence of Sarcopenia in Patients with Moderate to Severe COVID-19
Shuhei Yamamoto1, Yasunari Sakai1, Keiji Matsumori1
1Department of Rehabilitation, Shinshu University Hospital, Nagano 390-8621, Japan.

Abstract:
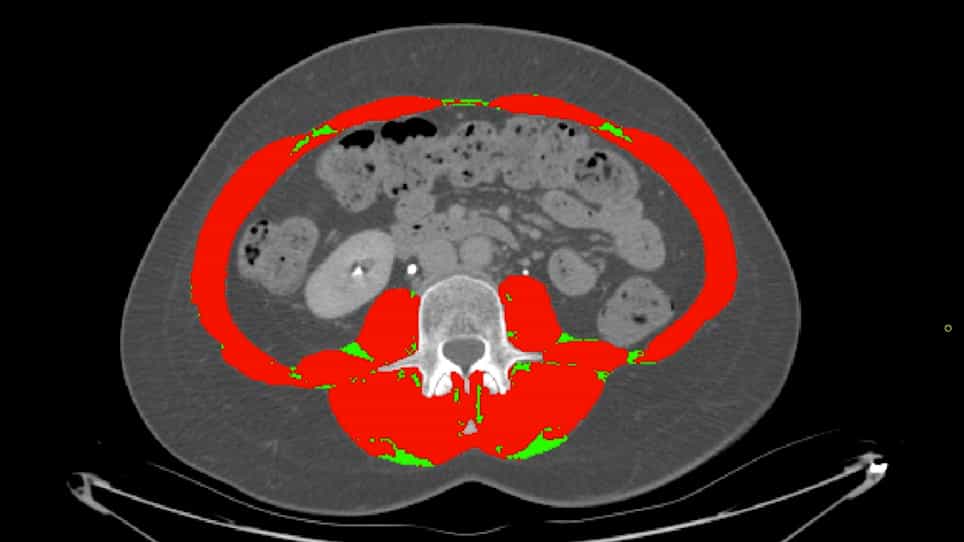
Background: The purpose of this study was to investigate the effectiveness and clinical outcomes of inpatient rehabilitation for patients with severe COVID-19 in Japan. Methods: Patients with severe COVID-19 who underwent rehabilitation during hospitalization were included. The Medical Research Council (MRC) score and short physical performance battery (SPPB), such as physical function assessment and the intensive care unit (ICU) mobility scale, the functional status score for the ICU, and Barthel index as activities of daily living (ADLs) were evaluated at admission and discharge or transfer from the hospital. The correlation between SPPB at discharge and each factor at admission were also analyzed. Furthermore, the prevalence of sarcopenia was evaluated by defining SPPB of <9 points at discharge as sarcopenia. Results: The median age of the total of 23 patients was 59 years (interquartile range (IQR): 47−67), 73.9% were male, and the median PaO2/FiO2 at admission was 172.0 (IQR: 123.0−209.0). All physical function and ADL parameters were significantly improved from the time of admission to discharge (p = 0.014 for the MRC score and p < 0.001 for all others). Moreover, SPPB at discharge significantly correlated with WBC (Spearman’s rho = −0.473, p = 0.041), C-reactive protein (Spearman’s rho = −0.468, p = 0.044), and exhibited a significant trend with PaO2/FiO2 (Spearman’s rho = 0.429, p = 0.067) and age (Spearman’s rho = 0.409, p = 0.083). Although the median Barthel index at discharge was 90 points, 47% of patients had sarcopenia as defined by an SPPB of <9 points. Conclusions: Early rehabilitation for patients with severe COVID-19 improved physical function and ADLs during hospitalization. However, 47% of patients had the same level of sarcopenia at discharge.

Related Concept Videos
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:28
Disorders of the Skeletal Muscle
Musculoskeletal disorders
Musculoskeletal disorders involve injuries and conditions affecting the skeletal muscles and associated connective tissues. These disorders can arise from acute biomechanical stresses or chronic overuse and can occur across different age groups. Common injuries include sprains, fractures, and muscular strains, often resulting from...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: