Related Experiment Video
Updated: Jun 5, 2026


Osmotic Minipump Implantation for Increasing Glucose Concentration in Mouse Cerebrospinal Fluid
Published on: April 7, 2023
Fingolimod Alleviates Cognitive Deficit in Type 2 Diabetes by Promoting Microglial M2 Polarization via the
Anika Sood1, Valencia Fernandes1, Kumari Preeti1
1Molecular & Cellular Neuroscience Lab, Department of Pharmacology and Toxicology, National Institute of Pharmaceutical Education and Research (NIPER)-Hyderabad, Telangana, 500037, Hyderabad, India.

Abstract:
Sphingosine receptors (S1PRs) are implicated in the progression of neurodegenerative diseases and metabolic disorders like obesity and type 2 diabetes (T2D). The link between S1PRs and cognition in type 2 diabetes, as well as the mechanisms that underpin it, are yet unknown. Neuroinflammation is the common pathology shared among T2D and cognitive impairment. However, the interplay between the M1 and M2 polarization state of microglia, a primary driver of neuroinflammation, could be the driving factor for impaired learning and memory in diabetes. In the present study, we investigated the effects of fingolimod (S1PR1 modulator) on cognition in high-fat diet and streptozotocin-induced diabetic mice. We further assessed the potential pathways linking microglial polarization and cognition in T2D. Fingolimod (0.5 mg/kg and 1 mg/kg) improved M2 polarization and synaptic plasticity while ameliorating cognitive decline and neuroinflammation. Sphingolipid dysregulation was mimicked in vitro using palmitate in BV2 cells, followed by conditioned media exposure to Neuro2A cells. Mechanistically, type 2 diabetes induced microglial activation, priming microglia towards the M1 phenotype. In the hippocampus and cortex of type 2 diabetic mice, there was a substantial drop in pSTAT3, which was reversed by fingolimod. This protective effect of fingolimod on microglial M2 polarization was primarily suppressed by selective jmjd3 blockade in vitro using GSK-J4, revealing that jmjd3 was involved downstream of STAT3 in the fingolimod-enabled shift of microglia from M1 to M2 polarization state. This study suggested that fingolimod might effectively improve cognition in type 2 diabetes by promoting M2 polarization.
More Related Videos
 08:34
Assessing Microglial Phagocytosis of Myelin Debris in vitro Under Repeated Magnetic Stimulation
Published on: June 17, 2025
 08:15
Network Pharmacology and Validation of the Antidepressant Mechanisms of Qiangzhifang in a Chronic Restraint Stress-induced Depression Rat Model
Published on: June 6, 2025
Related Concept Videos
 01:22
Alzheimer's Disease: Treatment
 01:26
Type I Diabetes II: Pathophysiology
 01:19
Type I Diabetes III: Clinical Manifestations
 01:24
Type II Diabetes II: Pathophysiology
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis
 01:23
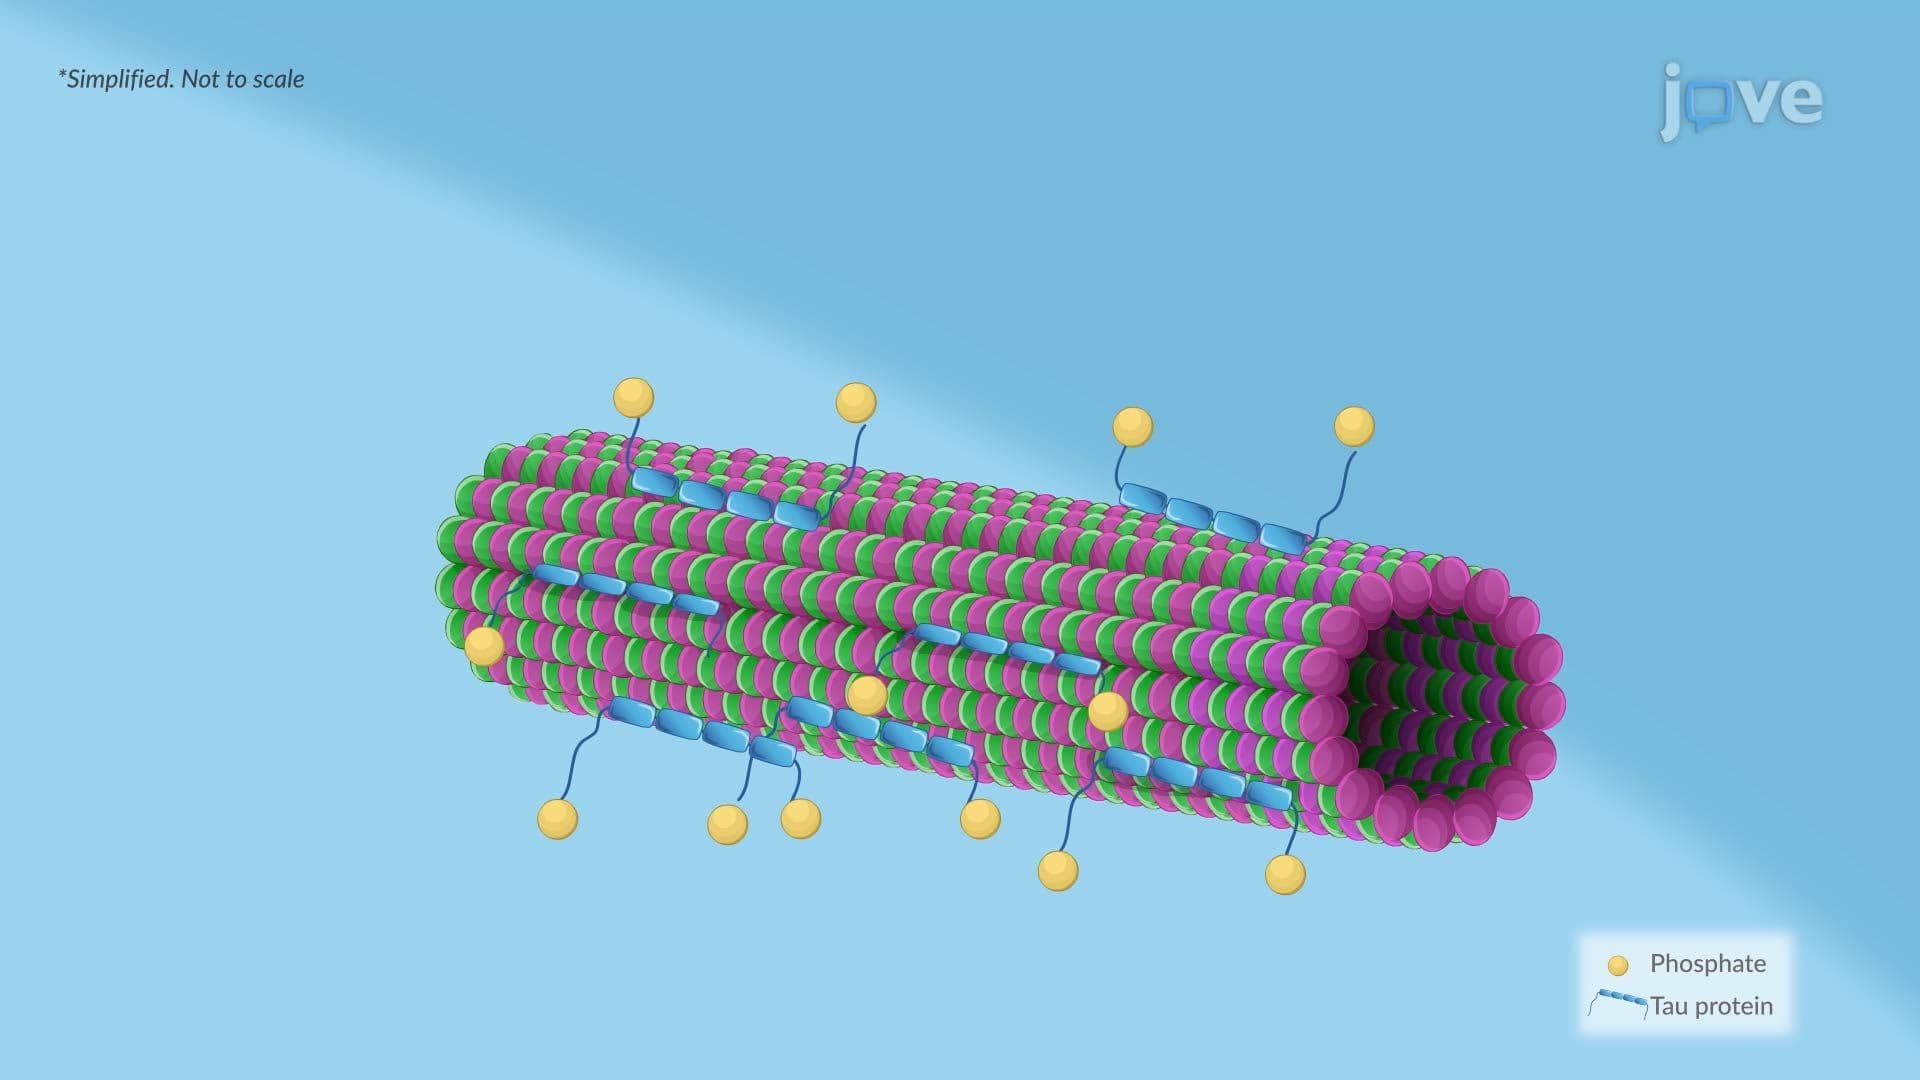
Alzheimer Disease ll: Pathophysiology