Related Experiment Video
Updated: Aug 20, 2025
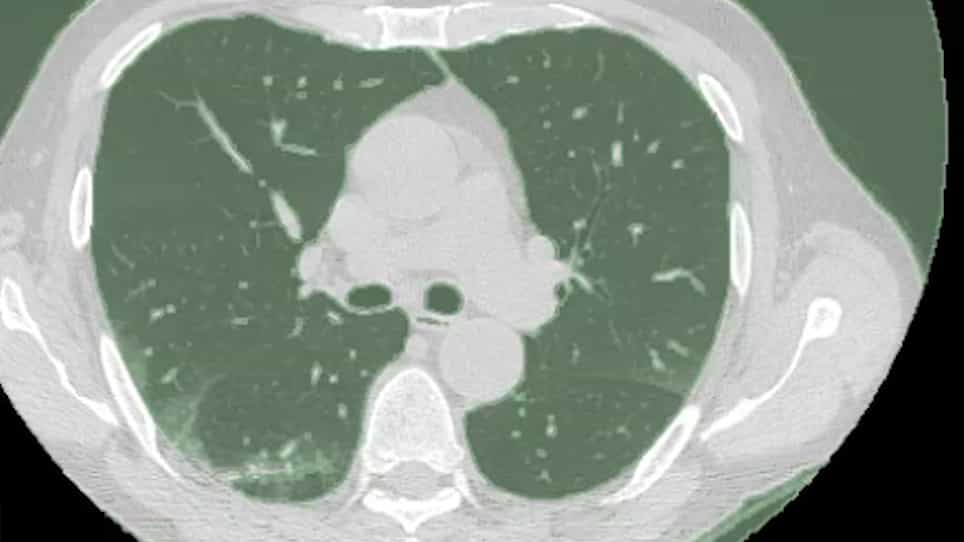

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Pulmonary sequelae of SARS-CoV-2 infection and factors associated with persistent abnormal lung function at six
Bashour Yazji1, Nha Voduc2, Sunita Mulpuru1,2
1The Ottawa Hospital Research Institute, Ottawa, Ontario, Canada.

Background:
Information on the long-term pulmonary sequelae following SARS-CoV-2 infection is limited.
Methods:
Prospective cohort study of hospitalized and non-hospitalized adult patients age >18 with documented SARS-CoV-2 infection by RT-PCR three months prior to enrolment between June and December 2020. Participants underwent full pulmonary function test (PFT), cardiopulmonary exercise testing at 3 months and 6 months. Primary outcome was mean differences of forced vital capacity (FVC), diffuse capacity of lung for carbon monoxide (DLCO), and oxygen consumption (VO2) at 6 vs. 3 months. Secondary outcomes were respiratory outcomes classified into 5 clinical groups-no lung disease, resolved lung disease, persistent lung disease, PFT abnormalities attributable to pre-existing lung disease or other factors, and mild PFT abnormalities of uncertain clinical significance.
Results:
Fifty-one, 30 hospitalized and 21 non-hospitalized, participants were included. Median age was 51 years; 20 (39.2%) were female. Mean (±SD) percent predicted values of FVC, DLCO and VO2 at 3 vs 6-month-visits were 96.2 ± 15.6 vs. 97.6 ± 15.5, 73.74 ±18 vs. 78.5 ± 15.5, and 75.5 ± 18.9 vs. 76.1 ± 21.5, respectively. Nineteen (37%) patients had physiologic and/or radiographic evidence of lung disease at 3 months with eight (15.7%) continuing to have persistent disease at 6 months. History of diabetes, hypertension, ICU admission and elevated D-Dimer levels were associated with persistent lung disease at 6 months.
Interpretation:
Persistent lung disease at 6 months post SARS-CoV-2 infection exists. Changes of lung function between 3- and 6-months are not significant. A longer follow-up is required to determine long-term prognosis.


Related Concept Videos
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:17
Pulmonary Cycle: Exhalation
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:29
Pneumonia II: Pathophysiology
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...