Related Experiment Video
Updated: Aug 20, 2025

Fertility Preservation Through Oocyte Vitrification: Clinical and Laboratory Perspectives
Published on: September 16, 2021
Luteal phase support with progesterone does not improve pregnancy rates in patients undergoing ovarian stimulation
Elizabeth Dilday1, Marisa Gigg1, Luis Hoyos2
1UCLA Department of Obstetrics and Gynecology, Division of Reproductive Endocrinology and Infertility, David Geffen School of Medicine, Los Angeles CA, USA.

Research Question:
Does luteal phase support with vaginal progesterone improve clinical pregnancy rates in patients undergoing ovarian stimulation with letrozole?
Design:
This was a retrospective cohort study of patients undergoing ovarian stimulation with letrozole paired with intrauterine insemination (IUI) or timed intercourse (TIC) from January 2018 to October 2021. The primary outcome of clinical pregnancy rate (CPR) was calculated for cycles with and without luteal phase progesterone support. Univariate logistic regressions were done to evaluate predictor variables for CPR. Clinically important covariates including age, body mass index, anti-Müllerian hormone concentration, diagnosis of ovulatory dysfunction and multifollicular development were included in a multivariate analysis evaluating the relationship between luteal progesterone use and odds of clinical pregnancy. Secondary outcomes including spontaneous abortion, biochemical pregnancy and ectopic pregnancy were calculated. Live birth rates were calculated for cycles in a secondary analysis.
Results:
A total of 492 letrozole ovarian stimulation cycles in 273 patients were included. Of these cycles, 387 (78.7%) used vaginal progesterone for luteal support and 105 (21.3%) did not. The unadjusted CPR per cycle was 11.6% (45/387) with progesterone and 13.3% (14/105) without progesterone (P = 0.645). After adjusting for significant covariates including age, BMI, diagnosis of ovulatory dysfunction and multifollicular development, the odds for clinical pregnancy were not significantly improved in cycles with exogenous progesterone (odds ratio [OR] 1.15, 95% confidence interval [CI] 0.48-2.75, P = 0.762). A follow-up analysis demonstrated that live birth rate was 10.7% (41/384) with and 12.5% (13/104) without luteal progesterone, respectively (P = 0.599).
Conclusions:
Luteal support with vaginal progesterone does not significantly improve CPR in ovarian stimulation cycles using letrozole.

Related Concept Videos
 01:27
Ovarian Cycle
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...
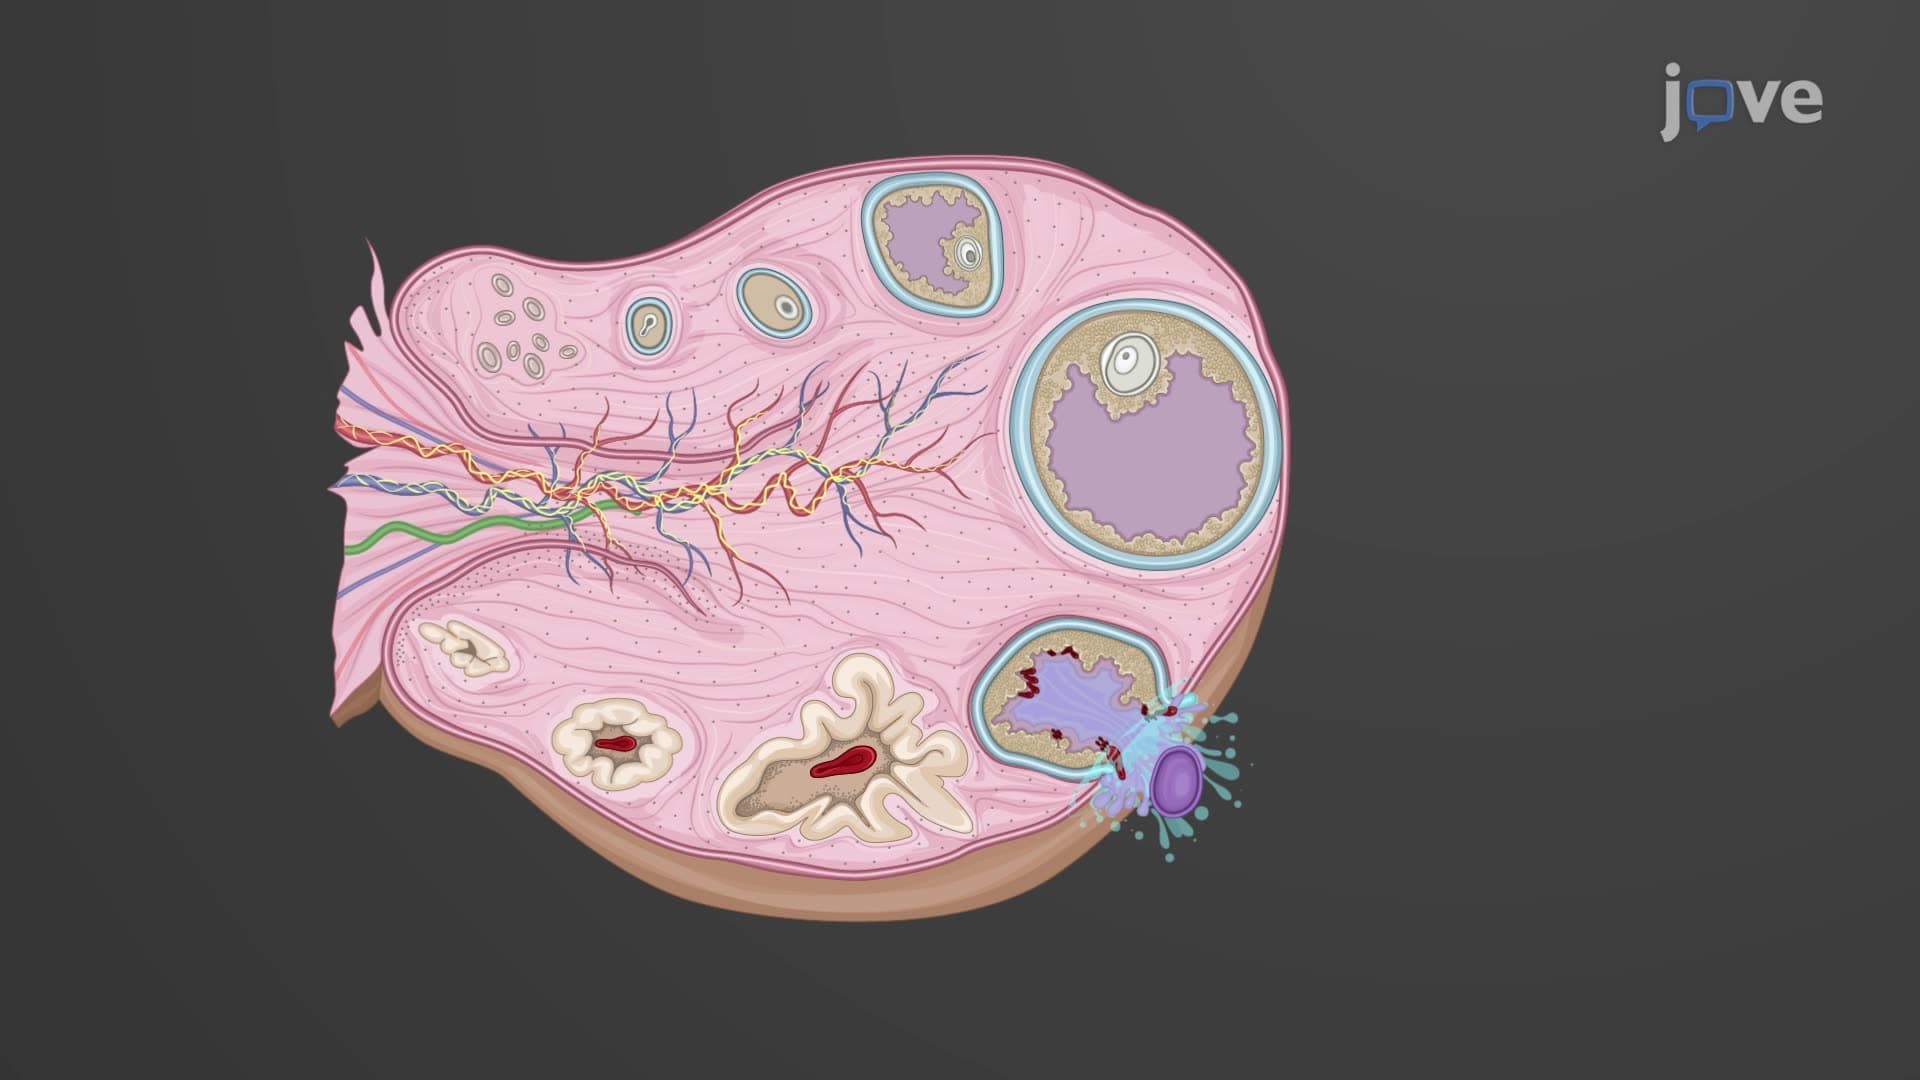 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 02:07
Oogenesis
 01:19
Secretory Phase
Following ovulation, the corpus luteum, a temporary endocrine structure, produces progesterone and estrogens. These hormones stimulate the growth and coiling of endometrial...