Related Experiment Video
Updated: Oct 8, 2026

Dissection of Adult Mouse Utricle and Adenovirus-mediated Supporting-cell Infection
Published on: March 28, 2012
Platinum-induced ototoxicity in pediatric cancer survivors: GSTP1 c.313A>G variant association
Laila M Sherief1, Elhamy Rifky1, Mohamed Attia2
1Department of Pediatrics and Pediatric Hematology/Oncology, Faculty of Medicine, Zagazig University, Zagazig, Egypt.

Abstract:
Hearing damage is one of the main toxic effects of platinum compounds, it derives from the irreversible degeneration of hair cells of the ear. Genetic association studies have suggested an association between GSTP1 c.313A>G variant and platinum-induced ototoxicity in childhood cancer survivors. We aimed to detect the frequency of ototoxicity and associated risk factors in survivors of childhood cancer receiving platinum-based chemotherapy and to detect the relation between GSTP1 c.313A>G (rs1695) polymorphisms and ototoxicity. We conducted a cross-sectional study on 64 cancer survivors who received platinum agents (cisplatin and/or carboplatin) at least 2 years after the end of chemotherapy. The patients underwent comprehensive audiological evaluations and genotyping to detect the presence of the GSTP1 c.313A>G polymorphisms. Hearing loss (HL) was identified in 16/64 patients (25%), including 62.5% treated with cisplatin and 37.5% treated with carboplatin. The greater incidence of ototoxicity was found in children treated for osteosarcoma (28.1%) followed by patients with germ cell tumors (25%) and neuroblastoma (21.9%). The AA, AG, and GG types of GSTP1 c.313A>G variant were detected in 84.4%, 9.4%, and 6.3%, respectively, of patients with HL with a significant association between mutant genotype of GSTP1 rs1695 and platinum-induced ototoxicity (P = .035). HL was not significantly associated with the total cumulative dose of cisplatin and carboplatin. GSTP1 c.313A>G variant may increase the risk of HL in pediatric oncology patients treated with cisplatin or carboplatin chemotherapy.
Insights
Platinum-based chemotherapy can cause hearing loss in childhood cancer survivors. The GSTP1 c.313A>G genetic variant is associated with an increased risk of this platinum-induced ototoxicity.
Area of Science:
- Oncology
- Genetics
- Audiology
Background:
- Platinum compounds, like cisplatin and carboplatin, are vital in pediatric cancer treatment.
- Hearing damage (ototoxicity) is a significant toxic side effect of platinum-based chemotherapy, stemming from irreversible hair cell degeneration.
- Genetic factors may influence susceptibility to platinum-induced ototoxicity.
Purpose of the Study:
- To determine the frequency of ototoxicity in childhood cancer survivors treated with platinum agents.
- To identify risk factors associated with platinum-induced ototoxicity.
- To investigate the relationship between the GSTP1 c.313A>G (rs1695) polymorphism and ototoxicity in these survivors.
Main Methods:
- A cross-sectional study involving 64 childhood cancer survivors who completed platinum-based chemotherapy at least two years prior.
- Comprehensive audiological evaluations were performed to assess hearing loss.
- Genotyping was conducted to identify the presence of GSTP1 c.313A>G polymorphisms (rs1695).
Main Results:
- Hearing loss (HL) was identified in 25% of the survivors (16/64).
- A significant association was found between the mutant GSTP1 rs1695 genotype and platinum-induced ototoxicity (P = .035).
- Ototoxicity incidence varied by cancer type, with osteosarcoma patients showing the highest rate (28.1%).
Conclusions:
- The GSTP1 c.313A>G variant may increase the risk of hearing loss in pediatric oncology patients receiving cisplatin or carboplatin chemotherapy.
- Genetic predisposition, specifically the GSTP1 rs1695 polymorphism, is a crucial factor in platinum-induced ototoxicity.
- Further research is warranted to explore genetic markers for predicting and mitigating ototoxicity in cancer survivors.

Related Concept Videos
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase
 01:16
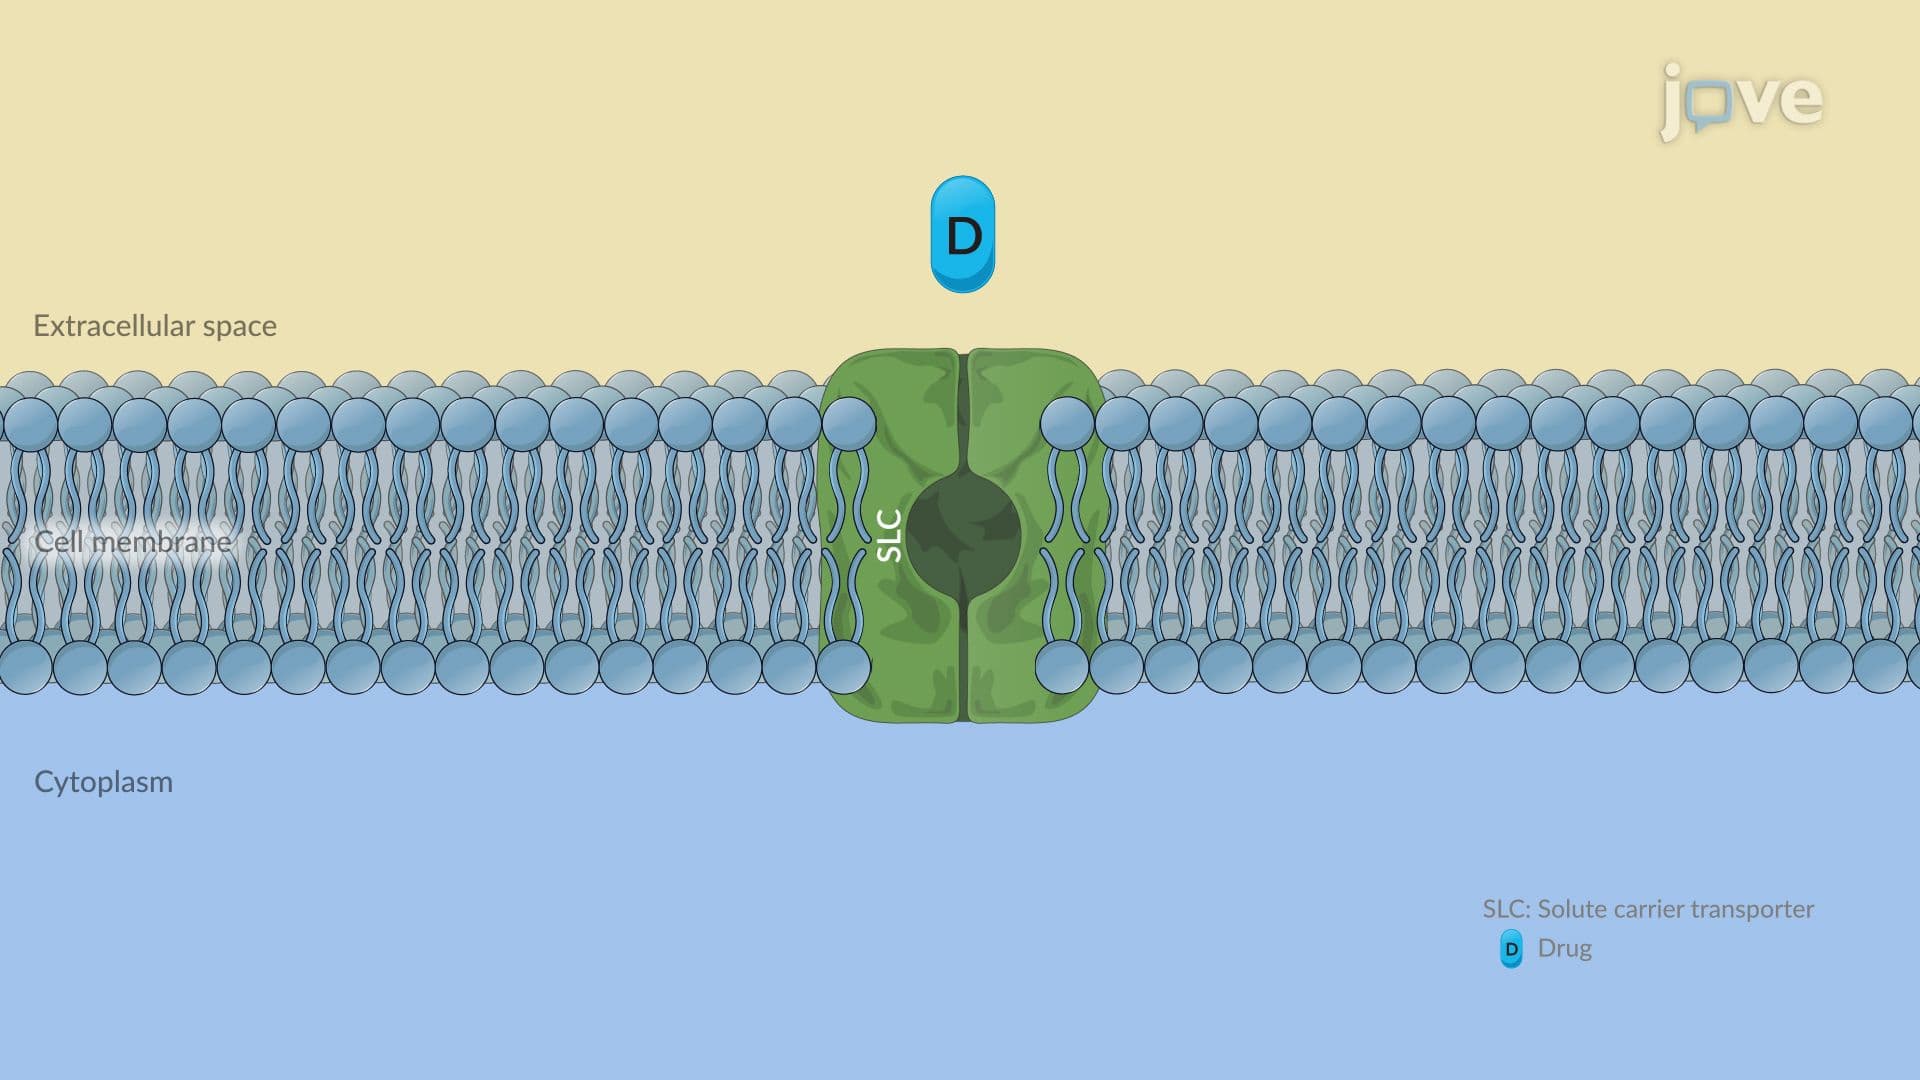
Pharmacogenetics of Drug Transporters: P-Glycoprotein and Solute Carrier Transporters
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase