Related Experiment Video
Updated: Aug 20, 2025

Estimation of Urinary Nanocrystals in Humans using Calcium Fluorophore Labeling and Nanoparticle Tracking Analysis
Published on: February 9, 2021
Clinical and molecular characterization of a large primary hyperoxaluria cohort from Saudi Arabia: a retrospective
Majid Alfadhel1,2, Muhammad Umair3, Malak A Alghamdi4
1Genetics and Precision Medicine Department (GPM), King Abdullah Specialized Children's Hospital, King Abdulaziz Medical City, Ministry of National Guard Health Affairs (MNG-HA), Riyadh, Saudi Arabia. dralfadhelm@gmail.com.

Background:
Primary hyperoxalurias (PHs) constitute rare disorders resulting in abnormal glyoxalate metabolism. PH-associated phenotypes range from progressive nephrocalcinosis and/or recurrent urolithiasis to early kidney failure.
Methods:
A retrospective study was conducted for patients with confirmed PH diagnoses from three tertiary centers in Saudi Arabia. Detailed clinical molecular diagnosis was performed for 25 affected individuals. Whole exome sequencing (WES)-based molecular diagnosis was performed for all affected individuals.
Results:
The male:female ratio was 52% male (n = 13) and 48% female (n = 12), and consanguinity was present in 88%. Nephrolithiasis and/or nephrocalcinosis were present in all patients. Kidney stones were present in 72%, nephrocalcinosis in 60%, hematuria in 32%, proteinuria in 16%, abdominal pain in 36%, developmental delay in 8%, and chronic kidney disease stage 5 (CKD stage 5) was observed in 28% of the patients. The most common PH disorder was type I caused by variants in the AGXT gene, accounting for 56%. The GRHPR gene variants were identified in 4 patients, 16% of the total cases. Seven patients did not reveal any associated variants. Missense variants were the most commonly observed variants (48%), followed by frame-shift duplication variants (28%).
Conclusions:
Characterization of the genetic and clinical aspects of PH in this unique population provides direction for improved patient management and further research. A higher resolution version of the Graphical abstract is available as Supplementary information.
More Related Videos
 09:40
Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
 10:31
Comparative Proteomic Analysis of Whole Kidney, Medulla, and Cortical Tubules in Diabetic Pathogenesis of Kidney Injury in Mice
Published on: May 2, 2025
Related Concept Videos
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:25
Chronic Kidney Disease I: Introduction
 01:29
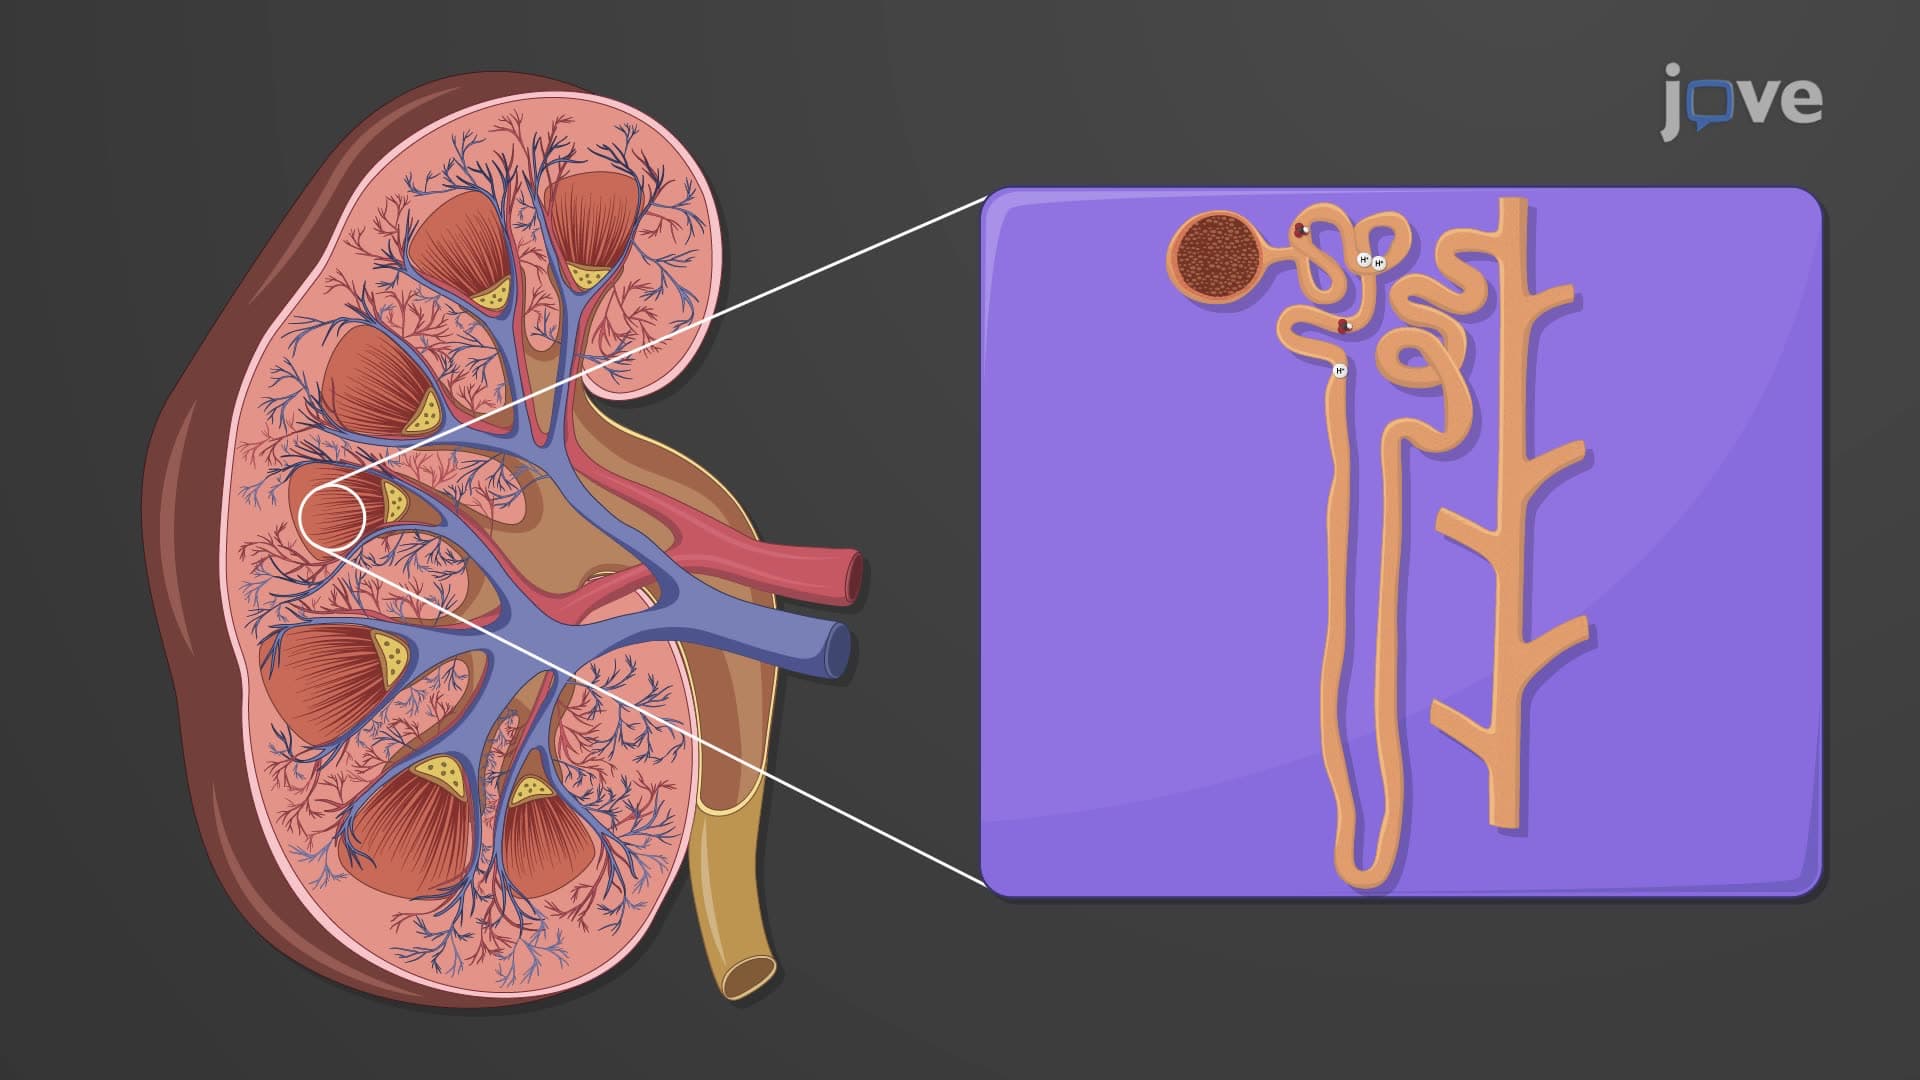
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous...
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies